Gout in Ankle Symptoms: Signs, Causes and When to Act
Gout in ankle symptoms typically appear suddenly, often overnight, as intense throbbing pain, marked swelling, redness so vivid the skin may appear bruised or burned, and warmth so pronounced the joint is hot to the touch. These symptoms are produced by an acute inflammatory cascade triggered when needle-shaped monosodium urate (MSU) crystals shed into the fluid-filled space of the ankle joint, activating a rapid and overwhelming innate immune response.
According to the Centers for Disease Control and Prevention (CDC), gout affects an estimated 8.3 million adults in the United States, making it the most common inflammatory arthritis in adults. The ankle is the second most frequently affected joint after the first metatarsophalangeal joint (the base of the big toe), and ankle gout is among the most misdiagnosed joint conditions because its presentation closely mimics ankle sprain, cellulitis, and, in the most dangerous cases, septic arthritis.
This article covers every clinically recognized symptom of gout in the ankle with the physiological mechanism behind each one, the full staging picture from first attack to chronic tophaceous disease, the differential diagnosis most likely to trip you up, and exactly when ankle symptoms cross the threshold from “call your doctor” to “go to the emergency room now.”
Gout in Ankle Symptoms: What Your Joint Is Telling You
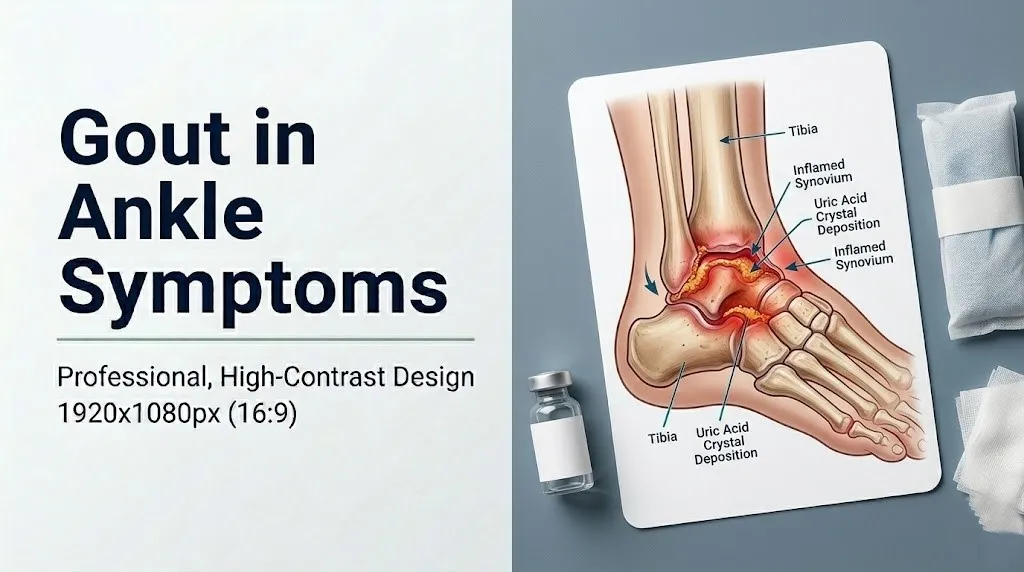
Gout in ankle symptoms include sudden severe joint pain, marked swelling of the ankle and surrounding tissue, intense redness, radiating warmth, and exquisite tenderness to the lightest touch, all produced by an acute crystal-induced inflammatory event inside the talocrural joint or subtalar joint.
These symptoms tend to peak within 12 to 24 hours of onset and, without treatment, typically resolve within 7 to 14 days in a first attack. The rapidity of onset is one of the most diagnostically useful features of ankle gout. Very few joint conditions produce maximal inflammation within hours of the first symptom.
The full symptom constellation in an acute ankle gout attack includes:
- Severe throbbing or crushing pain localized to the ankle, often rated 8 to 10 on the Visual Analog Scale for pain by patients during peak inflammation
- Visible swelling that may extend from the ankle to the lower leg and dorsum of the foot
- Erythema (redness) of the skin overlying the lateral or medial ankle, sometimes extending to the lower calf
- Palpable warmth across the joint surface, measurable above the contralateral ankle by clinical thermometry
- Exquisite tenderness to touch, including sensitivity to the weight of a bedsheet
- Limited range of motion in dorsiflexion and plantarflexion due to intra-articular pressure from synovial effusion
- Systemic symptoms in moderate-to-severe attacks: low-grade fever (37.5 to 38.5 degrees Celsius), malaise, and fatigue
Men between the ages of 40 and 60 experience the highest frequency of ankle gout attacks, but postmenopausal women face rapidly increasing risk after age 60, a pattern explained in detail in the population variation section below.
| Symptom | Onset Timing | Clinical Significance |
|---|---|---|
| Severe joint pain | 0 to 6 hours from onset | Cardinal symptom; rate 8-10/10 at peak |
| Visible ankle swelling | 2 to 12 hours | Reflects synovial effusion and periarticular edema |
| Skin redness (erythema) | 4 to 24 hours | Vascular dilation from prostaglandin E2 and bradykinin |
| Joint warmth | 4 to 24 hours | Hyperemia from inflammatory vasodilation |
| Touch sensitivity | 6 to 24 hours | Peripheral nociceptor sensitization |
| Low-grade fever | 12 to 48 hours | Systemic IL-6 release from inflamed synovium |
| Skin peeling (desquamation) | 7 to 14 days (resolving phase) | Inflammation subsiding; epidermis shedding |
What Is Gout in the Ankle and Why Does It Happen There
Gout in the ankle occurs when hyperuricemia (a serum uric acid level above 6.8 mg/dL, the physiological supersaturation threshold) causes monosodium urate crystals to form and accumulate within the synovial lining and cartilage of the ankle joint complex.
The ankle is a preferential site for urate crystal deposition for a reason that most gout articles never explain: temperature. The talocrural and subtalar joints, located distally in the lower extremity and exposed to ambient temperature fluctuations, maintain an intra-articular temperature of approximately 32 to 34 degrees Celsius, compared to 37 degrees Celsius in core body joints. Monosodium urate’s solubility decreases as temperature drops. At lower temperatures, urate precipitates from solution at lower serum concentrations than it would at core body temperature.
Think of it like dissolving sugar in water. Hot water holds more sugar in solution. As the water cools, the sugar crystallizes out. The ankle, being cooler and peripheral, is precisely where urate crystals form first and most readily at borderline-elevated serum levels.
Once crystals form within the synovial membrane or are shed from existing deposits, they are recognized by resident macrophages as foreign particles. Phagocytosis activates the NLRP3 inflammasome, a molecular platform inside macrophages and neutrophils. The NLRP3 inflammasome cleaves pro-IL-1 beta via caspase-1, releasing active interleukin-1 beta (IL-1 beta), the master inflammatory cytokine driving the acute gout attack.
According to the National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIAMS), gout is caused by a combination of genetic predisposition to hyperuricemia and environmental factors including diet, alcohol consumption, dehydration, and medication use. Ankle involvement is particularly common in individuals with a longer duration of hyperuricemia, where crystal burden has accumulated beyond the first metatarsophalangeal joint.
What Does Gout in the Ankle Feel Like
Gout in the ankle feels like a combination of crushing pressure, burning heat, and electric shock pain concentrated at the joint, with skin so sensitive that any contact, including a bedsheet or gentle breeze, produces intense pain disproportionate to the stimulus.
This extreme touch sensitivity is called allodynia in clinical terms, and it occurs because the prostaglandin E2 and bradykinin released during the inflammatory cascade sensitize peripheral nociceptors (pain-sensing nerve endings) in and around the joint capsule. Nerve endings that normally require a painful stimulus to fire begin firing in response to light touch, warmth, or movement. The ankle, which has rich nociceptive innervation from the deep peroneal nerve, superficial peroneal nerve, and branches of the tibial nerve, is exquisitely responsive to this sensitization.
Patients consistently describe the pain character in several specific ways:
- A deep, throbbing pain that pulses with each heartbeat, reflecting the vascular pressure wave propagating through the inflamed, engorged joint tissue
- A burning quality on the skin surface, generated by vasodilatory hyperemia in the superficial dermal capillaries
- A pressure sensation inside the ankle, produced by synovial effusion expanding the joint capsule against its ligamentous constraints
- Pain that worsens dramatically with any attempt to bear weight, move the ankle, or even allow the foot to hang dependent from the bed
The Mayo Clinic notes that gout pain is often described by patients as the worst pain they have ever experienced in that joint, a characterization consistent with the intensity of the NLRP3-mediated inflammatory response, which recruits neutrophils en masse into the joint space within hours of crystal recognition.
Older adults with peripheral neuropathy from diabetes or cardiovascular disease may experience a blunted pain response despite active joint inflammation, making the swelling and redness more prominent relative to pain as the presenting complaint.
Key Takeaway: The extreme touch sensitivity of ankle gout, where even a bedsheet causes pain, is a specific physiological feature produced by prostaglandin E2 sensitizing peripheral nociceptors in the joint capsule, not simply “bad pain.”
Gout Ankle Swelling Symptoms
Ankle swelling from gout reflects two simultaneous physiological processes: synovial effusion inside the joint capsule itself, and periarticular edema in the surrounding soft tissues driven by inflammatory vascular leakage.
Inside the talocrural joint, IL-1 beta and TNF-alpha act on synovial fibroblasts and vascular endothelial cells, upregulating adhesion molecules that allow neutrophils to migrate out of capillaries and into the joint space. This neutrophil influx, combined with the protein-rich inflammatory exudate flooding the synovial cavity, produces intra-articular effusion. The joint capsule distends against the surrounding ligaments, producing the taut, bowed appearance visible at the ankle.
Simultaneously, the inflammatory cytokines increase vascular permeability in the periarticular tissues. Plasma fluid leaks from capillaries into the interstitial space surrounding the ankle. This periarticular edema extends the visible swelling beyond the joint itself, often spreading to the dorsum of the foot, the distal lower leg, and the area just above the medial or lateral malleolus.
The swelling in ankle gout is typically non-pitting in the acute phase, unlike the pitting edema of cardiac or renal fluid retention. Pressing a finger into the swollen ankle during an active gout attack leaves little or no pit because the swelling is primarily inflammatory infiltrate rather than simple fluid. This distinction can help differentiate gout swelling from systemic edema at the bedside, though it is not definitive without further evaluation.
According to a 2019 observational study published in Arthritis and Rheumatology, ankle involvement in acute gout is associated with a larger total joint effusion volume on ultrasound than great toe attacks, likely because of the greater synovial surface area of the talocrural joint compared to the first metatarsophalangeal joint.
Patients taking diuretics for hypertension or heart failure should note that thiazide and loop diuretics reduce renal urate excretion by competing with urate at the organic anion transporter in the proximal renal tubule, increasing serum uric acid and swelling severity during attacks.
Gout Ankle Redness and Warmth
The redness and warmth of an ankle gout attack are produced by inflammatory vasodilation in the dermal and subdermal capillary networks overlying the joint, driven by prostaglandin E2 acting on vascular smooth muscle through EP2 and EP4 receptor activation.
Prostaglandin E2, synthesized from arachidonic acid via the cyclooxygenase-2 (COX-2) enzyme in inflamed synovial tissue, relaxes vascular smooth muscle in the small arteries and arterioles supplying the ankle skin and periarticular tissue. This vasodilation increases blood flow dramatically. The increased perfusion produces erythema (redness) as more oxygenated blood fills superficial capillaries, and warmth as the thermal energy of that blood reaches the skin surface.
The redness of acute ankle gout can be strikingly vivid. The skin may appear crimson or deep red, and in pale-skinned individuals it can genuinely resemble a severe sunburn or infection. In darker-skinned individuals, the redness may appear as a deepening of skin tone, a brownish-purple discoloration, or increased skin sheen rather than true red erythema, a presentation difference that matters for accurate recognition.
The warmth is measurable. During active ankle gout, the skin overlying the inflamed joint is typically 2 to 4 degrees Celsius warmer than the same area on the unaffected contralateral ankle, a difference detectable by hand palpation and quantifiable with an infrared skin thermometer.
The Arthritis Foundation notes that the cardinal signs of acute gout (pain, swelling, redness, warmth) collectively reflect the four classical signs of inflammation described by Celsus: dolor, tumor, rubor, and calor. Ankle gout consistently produces all four in their most pronounced clinical form.
Individuals with darker skin tones are at higher risk of having their gout redness underrecognized or misattributed to bruising, particularly in emergency settings. Requesting joint aspiration rather than relying solely on visual assessment is the appropriate clinical standard when diagnosis is uncertain regardless of skin tone.
Gout Ankle Pain at Night
Ankle gout attacks most frequently begin at night or in the early morning hours, a timing pattern with a specific physiological explanation rooted in the temperature-solubility relationship of monosodium urate and the changes in cortisol secretion during sleep.
During sleep, core body temperature drops slightly as part of the normal circadian rhythm, and peripheral joint temperatures fall accordingly. Lower intra-articular temperature reduces urate solubility further below the threshold already established during waking hours, accelerating crystal nucleation and shedding within the joint. The ankle, already operating at a cooler baseline temperature than core joints, is particularly vulnerable to this overnight temperature dip.
Simultaneously, cortisol secretion follows a circadian nadir during the early hours of sleep (approximately midnight to 3 a.m.) before rising again toward morning. Cortisol has anti-inflammatory properties, partly by suppressing COX-2 expression and inhibiting neutrophil migration. When cortisol levels are at their overnight nadir, the inflammatory brake is partially released, allowing the crystal-triggered inflammatory cascade to escalate more rapidly and reach painful intensity faster than it would during waking hours.
A 2015 study published in Arthritis and Rheumatology found that the risk of an acute gout attack was approximately 2.4 times higher during the overnight and early-morning hours compared to daytime periods, consistent with both the temperature-crystallization and cortisol-nadir mechanisms.
The practical implication is that a person who goes to bed feeling fine and wakes at 2 or 3 a.m. with severe ankle pain, swelling, and redness should treat this specific temporal pattern as a strong clinical indicator pointing toward gout rather than an ankle sprain or other mechanical injury.
Individuals who take their gout prevention medications at night should note that consistency of dosing timing matters because of this circadian vulnerability window. Patients prescribed colchicine or allopurinol should discuss optimal dosing timing with their prescribing physician.
Key Takeaway: Ankle gout attacks peak overnight because falling peripheral joint temperature accelerates urate crystallization precisely when cortisol’s overnight nadir removes a key anti-inflammatory brake on the NLRP3 inflammasome cascade.
Early Stage Gout Ankle Symptoms
Early-stage gout in the ankle often presents with one or two distinct attacks that resolve completely within 7 to 14 days, with the ankle returning fully to normal between episodes, a period called intercritical gout that can last months to years before the next attack.
The first ankle gout attack typically affects one ankle at a time. Bilateral simultaneous presentation, while possible in polyarticular gout, is unusual in the first episode. The pain reaches maximum intensity within 12 to 24 hours of onset, often before the person has recognized what is happening or sought medical attention.
A frequently missed early feature is a prodromal period in the hours before the full attack. Some patients report mild ankle discomfort, itching, or warmth in the 4 to 12 hours preceding peak pain. This prodrome occurs because the crystal shedding and early macrophage recognition begin before the full neutrophil recruitment wave arrives. Recognizing this prodrome and initiating medical treatment (if already prescribed) during this window is associated with faster attack resolution.
Early features that distinguish a first ankle gout attack from other causes of acute ankle pain:
- No preceding trauma, unusual physical activity, or ankle movement that would explain a sprain
- Pain reaching peak intensity within 12 to 24 hours, faster than most soft tissue injuries
- Redness and warmth out of proportion to the degree of swelling
- Resolution over 7 to 14 days without specific treatment (self-limiting nature of first attacks)
- Complete return to normal function between attacks
According to the American College of Rheumatology (ACR) 2020 gout management guidelines, patients experiencing their first confirmed gout attack should have a serum uric acid level measured at least two weeks after the acute attack has fully resolved, since uric acid levels can be artificially lowered during acute inflammation due to cytokine-mediated changes in renal urate handling.
Young adults, particularly men aged 20 to 35 presenting with a first ankle attack, should be evaluated for an underlying cause of early-onset hyperuricemia, including genetic variants in renal urate transporters (URAT1, GLUT9, ABCG2), lead nephropathy, or rare enzyme deficiencies (Lesch-Nyhan syndrome, glucose-6-phosphatase deficiency).
Chronic Gout Ankle Symptoms
Chronic gout in the ankle develops when repeated attacks have not been managed with urate-lowering therapy, producing a pattern of increasingly frequent flares, persistent between-attack ankle discomfort, and eventually continuous low-grade joint inflammation that never fully resolves.
The transition from episodic to chronic disease is gradual. In the intercritical period of early gout, the ankle is completely asymptomatic between attacks. As crystal burden accumulates in the synovial tissue and cartilage over years, the inflammatory threshold drops. Attacks become more frequent, often occurring every few weeks rather than every few months. The pain during attacks may be slightly less severe per episode but the cumulative joint exposure to inflammatory mediators increases.
Persistent low-grade inflammation in chronic ankle gout produces several symptoms distinct from the acute attack:
- Ongoing morning stiffness lasting more than 30 minutes after waking, similar to the stiffness pattern of rheumatoid arthritis
- Mild to moderate ankle aching throughout the day that worsens with prolonged standing or walking
- Gradual reduction in ankle range of motion, particularly in dorsiflexion, from synovial thickening and early cartilage damage
- Visible joint line tenderness on palpation that persists between acute attacks
- Fatigue and mood changes from chronic pain and sleep disruption
Chronic ankle gout without treatment also produces radiographic changes visible on plain X-ray: juxta-articular bony erosions with overhanging edges (the “rat bite” erosion pattern characteristic of chronic tophaceous gout), joint space narrowing from cartilage loss, and periarticular soft tissue density changes from tophus formation.
Research published in Annals of the Rheumatic Diseases in 2021 found that patients with uncontrolled hyperuricemia and recurrent gout attacks showed measurable ankle cartilage thinning on MRI within five years of symptom onset, reinforcing the importance of urate-lowering therapy in preventing structural joint damage.
Elderly patients with chronic ankle gout may present atypically with insidious onset joint deformity and reduced pain sensitivity from coexisting peripheral neuropathy, making their chronic disease more advanced by the time it is recognized than in younger patients.
Tophaceous Gout Ankle Signs
Tophaceous gout at the ankle occurs when chronically elevated uric acid levels cause MSU crystals to aggregate into firm, palpable white or cream-colored masses called tophi within the subcutaneous tissue, tendons, and joint capsule of the ankle region.
Tophi are not painful in themselves, unlike the acute attack. They are firm to hard on palpation and have a characteristic chalky white color when overlying skin is thin enough to allow visualization through the tissue. They form preferentially at the medial and lateral ankle, the Achilles tendon, the retrocalcaneal bursa, and occasionally within the peroneal tendon sheaths. An Achilles tendon tophus presents as a fusiform (spindle-shaped) swelling along the tendon’s length, firm to touch, and distinctly different from the typical soft swelling of Achilles tendinopathy.
Think of tophi like calcified chalk deposits slowly accumulating in the joint’s soft tissue. The body cannot dissolve them faster than they accumulate when serum uric acid remains persistently above 6.8 mg/dL. Over years, they grow large enough to restrict movement, damage surrounding bone, and occasionally ulcerate through the overlying skin, producing a white chalky discharge that is essentially pure monosodium urate.
Signs of tophaceous gout at the ankle:
- Firm, non-tender subcutaneous nodules at the medial or lateral malleolus
- Fusiform swelling along the Achilles tendon posterior to the calcaneus
- Visible yellowish-white material through thin overlying skin (tophus seen through the dermis)
- Skin ulceration with white chalky discharge at the tophus site
- Restricted ankle range of motion from periarticular tophus bulk
- Chronic bony erosion visible on plain radiograph with characteristic overhanging edges
The ACR 2020 gout management guidelines state that the presence of any visible or palpable tophus is an indication to initiate urate-lowering therapy regardless of attack frequency, because tophi represent a body urate burden that cannot be managed by dietary modification alone and will continue to cause structural joint damage without pharmacological intervention.
Patients with rheumatoid arthritis may develop rheumatoid nodules at the ankle that can superficially resemble tophi; the distinction requires joint aspiration or tissue biopsy in ambiguous cases.
Key Takeaway: A firm, non-tender lump at the ankle or along the Achilles tendon in a patient with a history of gout attacks is a tophus until proven otherwise, and its presence means urate-lowering therapy is indicated regardless of how infrequent recent attacks have been.
Gout in Ankle vs Ankle Sprain
Gout in the ankle and an ankle sprain share swelling, pain, and limited mobility, but they differ in onset pattern, pain character, skin appearance, and the clinical context in which they occur, and telling them apart has direct consequences for management.
An ankle sprain results from mechanical injury to one or more of the lateral ankle ligaments, most commonly the anterior talofibular ligament (ATFL), from inversion force applied to the ankle during physical activity. The pain of a sprain begins immediately at the moment of injury and reflects tissue damage: torn ligament fibers producing bleeding into the periarticular tissue, releasing bradykinin and substance P from damaged cells.
Gout pain, by contrast, begins without any initiating trauma. It starts hours before reaching maximum intensity, typically during sleep or rest. The skin in ankle gout turns dramatically red, resembling sunburn or infection. Ankle sprains produce localized bruising (ecchymosis) in the 24 to 48 hours after injury, spreading from the damaged ligament site, but do not typically produce the uniform, bright erythema of acute gout.
| Feature | Ankle Gout | Ankle Sprain |
|---|---|---|
| Onset trigger | Spontaneous; no trauma | Inversion injury during activity |
| Time to maximum pain | 12 to 24 hours | Immediate at time of injury |
| Skin redness (erythema) | Diffuse, bright red, warm | Localized bruising; absent early redness |
| Skin warmth | Pronounced, measurable | Mild, localized to bruised area |
| Touch sensitivity | Extreme allodynia; sheet sensitivity | Localized to injured ligament area |
| Onset during sleep | Common (nocturnal pattern) | Does not occur without prior trauma |
| History of similar episodes | Often present | Depends on activity history |
| Prior uric acid elevation | May be documented | Not relevant |
Athletic individuals and those who sustain an ankle injury during exercise present the most diagnostic challenge, because a sprain and a gout attack can theoretically coexist. Physical trauma can trigger a gout attack by disrupting MSU crystal deposits in the joint, releasing crystals into the synovial fluid and initiating an inflammatory response. If a patient reports both a twisting injury and subsequent symptoms that seem out of proportion to the mechanical injury, evaluation for coexisting gout is warranted.
Ankle Gout vs Cellulitis and Septic Arthritis
The most clinically consequential differential diagnosis for ankle gout is septic arthritis (bacterial infection of the joint space), because both conditions share severe pain, marked swelling, prominent redness, and joint warmth, but septic arthritis is a same-day medical emergency requiring joint aspiration and intravenous antibiotics.
Cellulitis (bacterial infection of the skin and subcutaneous tissue) is a closer surface mimic of ankle gout. Both produce redness, warmth, and swelling. The distinguishing feature is location. Cellulitis is a skin and soft tissue infection; it produces diffuse, poorly marginated redness that spreads across the skin surface. Gout erythema follows the joint contour and is concentrated over the inflamed joint space. Cellulitis is typically accompanied by a skin breach or entry wound, though this is not always visible.
Septic arthritis is the more dangerous diagnostic error. Missing it costs lives. The joint destruction from bacterial infection progresses within 24 to 48 hours, and delayed diagnosis is associated with permanent joint destruction and systemic sepsis.
Clinical features that push toward septic arthritis rather than gout:
- Fever above 38.5 degrees Celsius (gout can cause low-grade fever but rarely exceeds this threshold)
- Rigors (shaking chills), suggesting bacteremia
- Inability to flex or extend the ankle at all, beyond what pain alone would explain
- Recent skin infection, wound, or surgical procedure near the ankle
- Immunocompromised state (organ transplant recipient, HIV, active chemotherapy, long-term corticosteroid use)
- No prior history of gout and no documented hyperuricemia
- Joint aspiration producing turbid (cloudy), purulent-appearing fluid with white cell count above 50,000 cells/mL on synovial fluid analysis
According to Cleveland Clinic clinical guidance, the only way to reliably differentiate septic arthritis from acute gout at the ankle is joint aspiration with synovial fluid analysis, including Gram stain, bacterial culture, and polarized light microscopy for urate crystals. These tests can be performed simultaneously, because gout and septic arthritis can coexist in the same joint.
If you have ankle swelling, severe pain, and a fever above 38.5 degrees Celsius, go to the emergency room immediately. Do not wait for a scheduled appointment. Septic arthritis is a joint-destroying emergency.
Gout Ankle Risk Factors
Gout in the ankle is more likely to occur in individuals with a combination of factors that raise serum uric acid, impair renal urate excretion, or create conditions for crystal nucleation in the peripheral joint environment.
The primary risk factors supported by clinical evidence are:
- Serum uric acid above 6.8 mg/dL (the physiological supersaturation threshold): the higher and more sustained the level, the greater the crystal deposition risk
- Male sex between ages 40 and 60 (highest risk demographic)
- Postmenopausal status in women (estrogen’s uricosuric protection lost after menopause)
- Obesity (body mass index above 30 kg/m squared): adipose tissue increases purine synthesis and reduces renal urate clearance
- Chronic kidney disease (reduced renal urate filtration and tubular secretion)
- Hypertension treated with thiazide diuretics (hydrochlorothiazide, chlorthalidone) or loop diuretics (furosemide), which raise serum uric acid by 1 to 2 mg/dL
- Low-dose aspirin therapy (75 to 150 mg daily): competes with urate at the renal proximal tubular organic anion transporter
- Cyclosporine use in transplant recipients: profoundly reduces renal urate excretion
- High dietary purine intake (red meat, organ meats, shellfish) and high fructose consumption (soft drinks, processed foods)
- Alcohol consumption, particularly beer (contains guanosine, a purine precursor) and distilled spirits
- Dehydration: reduces urinary volume and urate dilution, raising urine urate concentration and serum levels
- Genetic variants in urate transporter genes: URAT1 (SLC22A12), GLUT9 (SLC2A9), ABCG2
The National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIAMS) reports that gout prevalence has nearly doubled over the past two decades in the United States, a trend linked to rising rates of obesity, hypertension, chronic kidney disease, and diuretic use across the adult population.
Patients taking low-dose aspirin for cardiovascular prevention should not stop the medication because of gout risk without discussing this specifically with the prescribing cardiologist or primary care physician, as the cardiovascular benefit of aspirin in indicated patients outweighs the uric acid effect.
Key Takeaway: Diuretics for blood pressure and low-dose aspirin for heart disease are two of the most common medications that raise serum uric acid, and patients taking these medications face an elevated gout-in-ankle risk that their prescribing physician should know about when evaluating new joint symptoms.
Gout in Ankle Symptoms in Women vs Men
Gout in ankle symptoms affects men and women differently in timing, presentation pattern, comorbidity profile, and the ease with which the diagnosis is made, with women frequently misdiagnosed because their presentation does not match the culturally dominant image of gout as a disease of middle-aged men.
Men develop gout on average one to two decades earlier than women because estrogen has a uricosuric effect: it upregulates the renal expression of the urate transporter URAT1 in the proximal convoluted tubule, increasing urinary urate excretion and keeping serum uric acid lower throughout reproductive years. After menopause, estrogen levels drop, URAT1 activity decreases, renal urate excretion falls, and serum uric acid rises toward male-equivalent levels. This is why gout in women clusters in the postmenopausal period, typically after age 60.
Women with ankle gout also present more frequently with polyarticular attacks (multiple joints affected simultaneously) compared to men, who more often present with classic monoarticular attacks starting at the first metatarsophalangeal joint before involving the ankle. This polyarticular pattern in women increases the likelihood of misdiagnosis as rheumatoid arthritis or reactive arthritis.
A 2018 study published in JAMA found that women with gout waited an average of 4.5 years longer than men to receive a confirmed gout diagnosis, despite equivalent clinical presentation severity at the time of diagnosis. The study attributed this gap to physician anchoring on gout as a male disease and to women’s higher rate of polyarticular presentation, which less commonly triggers the gout diagnosis pathway.
Men between ages 40 and 60 with hypertension, obesity, and heavy alcohol use represent the stereotypical gout patient. However, postmenopausal women with hypertension (particularly those on thiazide diuretics), chronic kidney disease, or heart failure requiring diuretic therapy represent an equally high-risk group whose symptoms deserve the same diagnostic rigor.
Hormone replacement therapy (HRT) after menopause may partially restore estrogen’s uricosuric effect and has been associated in observational studies with lower gout risk, but this should not be used as a rationale for initiating HRT; the decision involves multiple clinical considerations beyond uric acid management.
Gout Ankle and Kidney Disease Connection
The relationship between gout, ankle symptoms, and kidney disease is bidirectional: chronic kidney disease (CKD) is one of the strongest risk factors for developing gout, and persistent hyperuricemia from inadequately treated gout is associated with accelerated kidney function decline.
The kidney is the primary organ responsible for urate excretion. Under normal conditions, the proximal convoluted tubule of the kidney filters serum uric acid and reabsorbs approximately 90 percent of it via urate transporters (primarily URAT1 and OAT4) before secreting a net 8 to 10 percent into the urine as the final excreted fraction. In CKD, reduced nephron mass and impaired tubular function reduce this net secretion, causing urate to accumulate in the blood.
A serum creatinine elevation indicating CKD stage 3 or above (estimated glomerular filtration rate below 60 mL/min/1.73 m squared) reduces renal urate clearance enough to raise serum uric acid by 1 to 3 mg/dL above baseline, pushing many patients who were previously below the crystallization threshold into the symptomatic range.
Conversely, persistent hyperuricemia may directly contribute to kidney damage through several mechanisms: MSU crystal deposition in renal tubular cells (urate nephropathy), precipitation of uric acid crystals in the renal collecting system (uric acid nephrolithiasis), and putative direct effects of soluble urate on renal vascular endothelium promoting interstitial fibrosis. The evidence strength for the last mechanism is at the preliminary rather than well-established level.
Patients with both ankle gout and CKD face specific clinical challenges. Many first-line gout medications (NSAIDs) are relatively or absolutely contraindicated in CKD because of their nephrotoxic potential. Colchicine requires dose adjustment in moderate CKD and should be avoided in severe CKD. Allopurinol dose must be adjusted based on estimated glomerular filtration rate. These patients should be managed collaboratively by their primary care physician and a board-certified rheumatologist, with nephrology input when kidney function is severely impaired.
How to Diagnose Gout in the Ankle
Diagnosing gout in the ankle requires a combination of clinical history, physical examination, laboratory testing, and ideally direct examination of synovial fluid, because no blood test alone confirms the diagnosis with certainty.
The diagnostic process a physician follows in sequence:
- Clinical history: ask about the onset pattern (spontaneous vs. post-trauma), timing (nocturnal onset), character of pain (severe, throbbing, crushing), prior similar episodes, family history of gout, dietary habits (alcohol, red meat, shellfish, sugary beverages), medication list (diuretics, aspirin, cyclosporine), and known kidney disease or hypertension.
- Physical examination: assess ankle swelling distribution, erythema pattern, skin warmth (measured against contralateral ankle), range of motion limitation, tenderness localization, and presence of tophi at classic sites (Achilles tendon, medial malleolus, ear helix).
- Serum uric acid: measured in the non-acute state (ideally two to four weeks after an attack fully resolves). A level above 6.8 mg/dL supports the diagnosis but does not confirm it; serum uric acid can be normal during an acute attack.
- Complete blood count (CBC) and inflammatory markers: white blood cell count, C-reactive protein (CRP), and erythrocyte sedimentation rate (ESR) are typically elevated during an acute attack and help establish the presence of systemic inflammation.
- Synovial fluid aspiration (joint aspiration): the gold standard. Fluid from the inflamed ankle joint is analyzed under compensated polarized light microscopy. MSU crystals appear as needle-shaped, negatively birefringent crystals, bright yellow when aligned parallel to the slow axis of the compensator. This finding confirms gout with near-certainty.
- Imaging: plain ankle radiograph may show tophus-related erosions in chronic disease. Musculoskeletal ultrasound can detect the “double contour sign” (urate crystal deposition on articular cartilage surface) even between attacks. Dual-energy computed tomography (DECT) can visualize urate crystal deposits in color-coded format with high specificity.
The ACR/EULAR 2015 gout classification criteria are used in research settings and can assist clinicians; they include joint aspiration findings, imaging features, clinical presentation scores, and serum uric acid levels in a weighted scoring framework. A primary care physician can initiate the diagnostic workup; a board-certified rheumatologist should be involved when the diagnosis is uncertain or when management decisions regarding urate-lowering therapy are complex.
When to See a Doctor for Gout in Ankle
Any first-time episode of sudden severe ankle pain, swelling, and redness without a clear traumatic cause warrants evaluation by a primary care physician within 24 to 48 hours, because the diagnostic confirmation and acute management of a gout attack requires clinical assessment and, ideally, joint aspiration.
The clinical circumstances that determine urgency differ based on specific features of the presentation:
| Clinical Situation | Recommended Action | Provider Type |
|---|---|---|
| First episode of ankle pain, swelling, redness; no fever; no trauma | Primary care physician within 24 to 48 hours | Primary care physician |
| Recurrent ankle attacks; no prior diagnosis | Primary care physician within one week; request serum uric acid | Primary care physician |
| Known gout; ankle attack not resolving after 10 to 14 days | Same-week evaluation; medication review | Primary care physician or rheumatologist |
| Known gout; visible tophi at ankle | Scheduled rheumatology appointment; ULT assessment | Board-certified rheumatologist |
| Ankle pain with fever above 38.5 degrees Celsius | Emergency room, same day | Emergency medicine physician |
| Ankle pain with rigors, unable to bear any weight, immunocompromised | Emergency room immediately | Emergency medicine physician |
| Recurrent gout attacks despite medication | Rheumatology referral for ULT optimization | Board-certified rheumatologist |
What to bring to your appointment:
- A list of all current medications, including over-the-counter NSAIDs, aspirin, and any diuretics
- Documentation of prior similar episodes, including how long each lasted and how it resolved
- Any prior serum uric acid results if available
- A description of dietary and alcohol patterns in the week preceding the attack
- Any blood test results from the past 12 months including kidney function and complete blood count
According to the ACR 2020 gout management guidelines, patients who have experienced two or more gout attacks per year, have any tophi, or have gout with chronic kidney disease stage 3 or above should be offered urate-lowering therapy regardless of serum uric acid level at time of evaluation. This decision requires a physician prescription and ongoing monitoring.
Emergency Symptoms: When to Call 911 or Go to the ER
Certain presentations involving ankle pain, swelling, and redness require immediate emergency evaluation. Do not wait to see if these resolve on their own.
Go to the nearest emergency room immediately if you experience:
- Ankle pain and swelling with a fever above 38.5 degrees Celsius (101.3 degrees Fahrenheit), because this combination can indicate septic arthritis, a bacterial joint infection that destroys cartilage within 24 to 48 hours
- Shaking chills (rigors) accompanying ankle pain, suggesting bacteremia that may accompany septic arthritis
- Complete inability to bear any weight on the ankle combined with severe pain and redness, particularly in an immunocompromised individual (transplant recipient, patient on long-term corticosteroids, person with HIV, person undergoing chemotherapy)
- Rapid spread of redness from the ankle toward the lower leg over hours, combined with fever, suggesting necrotizing fasciitis or rapidly spreading cellulitis
- Sudden severe ankle pain in a person with no prior joint disease, a recent surgical procedure, or a current skin infection near the ankle
- Ankle symptoms in a person with known prosthetic joint hardware in the ankle or lower extremity, because prosthetic joint infection is a surgical emergency
These presentations can indicate septic arthritis, bacteremia, or necrotizing fasciitis and require emergency medical assessment, joint aspiration under controlled conditions, and intravenous treatment, not an urgent care appointment or a phone call to your primary care office.
Frequently Asked Questions About Gout in Ankle Symptoms
What does gout in the ankle feel like?
Gout in the ankle feels like intense throbbing or crushing pain combined with burning skin sensitivity so extreme that even a bedsheet causes pain.
The pain is produced by prostaglandin E2 and bradykinin sensitizing the nociceptive nerve endings (from the deep peroneal, superficial peroneal, and tibial nerve branches) surrounding the inflamed talocrural and subtalar joints.
Most patients rate ankle gout pain at 8 to 10 on the Visual Analog Scale during peak inflammation, with swelling, skin redness, and pronounced joint warmth accompanying the pain.
How long does an ankle gout attack last?
An untreated first ankle gout attack typically lasts 7 to 14 days before resolving spontaneously as the acute inflammatory response exhausts itself.
With appropriate medical treatment initiated early in the attack, the acute phase can often be shortened to 3 to 5 days.
Attacks in patients with chronic tophaceous gout or inadequately controlled hyperuricemia may last longer, from 2 to 4 weeks, and may not fully resolve between episodes.
Can you walk with gout in your ankle?
Walking with active ankle gout is typically extremely painful and inadvisable during peak inflammation, because weight-bearing increases intra-articular pressure on an already-distended joint capsule and worsens pain acutely.
The talocrural joint bears the full body weight with each step, making ankle gout more functionally disabling during an attack than gout in other joints such as the knee or wrist.
Rest with the ankle elevated above heart level reduces intra-articular fluid pressure and can decrease swelling and pain within hours; weight-bearing is usually possible again as the attack begins to resolve, typically by day 4 to 7.
How do I know if my ankle pain is gout or a sprain?
Ankle gout begins spontaneously without any twisting injury or trauma, reaches maximum pain within 12 to 24 hours, produces bright red skin erythema, and is often nocturnal in onset.
Ankle sprains begin at the exact moment of an inversion injury during activity, produce pain immediately, and cause localized bruising (ecchymosis) in the 24 to 48 hours after injury rather than diffuse skin redness.
If ankle pain begins during sleep or at rest with no history of injury and the skin is significantly red, an evaluation by a primary care physician for gout is warranted rather than assuming a musculoskeletal injury.
What triggers a gout flare in the ankle?
Common triggers for an ankle gout flare include alcohol consumption (particularly beer and spirits), a high-purine meal (red meat, organ meats, shellfish), dehydration, sudden changes in uric acid level (either rapid increase or rapid decrease from starting urate-lowering medication), illness or surgery, and trauma to the joint.
The mechanism behind each trigger is either a rapid rise in serum uric acid that pushes levels above the crystallization threshold or a change in joint conditions (dehydration, trauma-induced crystal shedding) that destabilizes existing MSU crystal deposits.
Patients with known gout should maintain consistent hydration, consistent medication adherence, and awareness of dietary purine load, particularly in the 24 to 48 hours before high-risk situations like travel, celebrations, or illness.
Can women get gout in the ankle?
Yes, women can and do develop gout in the ankle, though this typically occurs after menopause when estrogen’s uricosuric effect on the renal URAT1 urate transporter is lost.
A 2018 study published in JAMA found that women with gout waited an average of 4.5 years longer than men to receive a confirmed diagnosis, a gap attributed partly to the incorrect assumption that gout is primarily a male condition.
Postmenopausal women, particularly those with hypertension taking diuretics, chronic kidney disease, or heart failure, face a gout risk that approaches that of men in the same age group and should receive the same diagnostic evaluation when presenting with acute ankle inflammation.
Closing
Gout in the ankle is one of the most recognizable inflammatory joint conditions when you know what to look for: sudden nocturnal onset, crushing pain peaking within 24 hours, dramatic redness and warmth, skin so sensitive that a bedsheet becomes an instrument of pain. The mechanism behind every one of those symptoms traces directly to the NLRP3 inflammasome activation and the IL-1 beta cascade that MSU crystal phagocytosis triggers in the talocrural and subtalar joints.
The most actionable step from this article is knowing when ankle symptoms cross from “call your doctor this week” to “go to the emergency room today.” If there is fever above 38.5 degrees Celsius with ankle joint swelling, treat it as septic arthritis until a physician with a needle and a polarized light microscope proves otherwise.
If you suspect ankle gout and have no prior diagnosis, bring a medication list (especially diuretics and aspirin), a description of your dietary and alcohol patterns in the preceding 48 hours, and a note of any prior similar episodes to your primary care physician. Ask specifically for a serum uric acid level, measured after the attack fully resolves, and ask whether you should be referred to a board-certified rheumatologist for urate-lowering therapy assessment.