Silent Reflux Symptoms: Full 2026 Clinical Guide
Silent reflux symptoms often have nothing to do with heartburn. Instead, they show up as a chronic cough, a raw throat, a persistent hoarse voice, or the unsettling feeling that something is stuck in your throat, sometimes for months before anyone connects the dots to acid.
The condition behind these symptoms is laryngopharyngeal reflux (LPR), a form of reflux in which gastric contents travel not just into the esophagus but past the upper throat and into the larynx and pharynx. According to the American Academy of Otolaryngology-Head and Neck Surgery (AAO-HNS), LPR is estimated to account for approximately 10 percent of all otolaryngology (ear, nose, and throat) office visits, and many cases go undiagnosed for years because the classic symptom of heartburn is absent.
This guide covers every clinically recognized LPR symptom with the physiological mechanism behind each one, explains why silent reflux behaves so differently from typical GERD, addresses how symptoms vary by age group and individual health status, identifies the red flags that need prompt professional evaluation, and explains exactly how LPR is assessed clinically. The goal is to give you a specific, accurate clinical picture, not vague reassurance.
Silent Reflux Symptoms: What You Need to Know First
Silent reflux symptoms are upper airway and throat symptoms produced when stomach contents reach the larynx and pharynx, typically without causing the esophageal burning sensation most people associate with acid reflux.
The term “silent” refers specifically to the absence of classic heartburn, not to the absence of symptoms. In practice, LPR is anything but silent. Most people with the condition notice a cluster of throat, voice, and respiratory symptoms that can be disruptive and persistent.
The most commonly reported symptoms, according to clinical surveys using the validated Reflux Symptom Index (RSI) developed by Dr. Peter Belafsky and published in the Journal of Voice, include: hoarseness or voice changes, a lump-in-the-throat sensation (globus pharyngeus), troublesome or annoying cough, throat clearing, post-nasal drip sensation, difficulty swallowing, and chronic throat soreness or irritation.
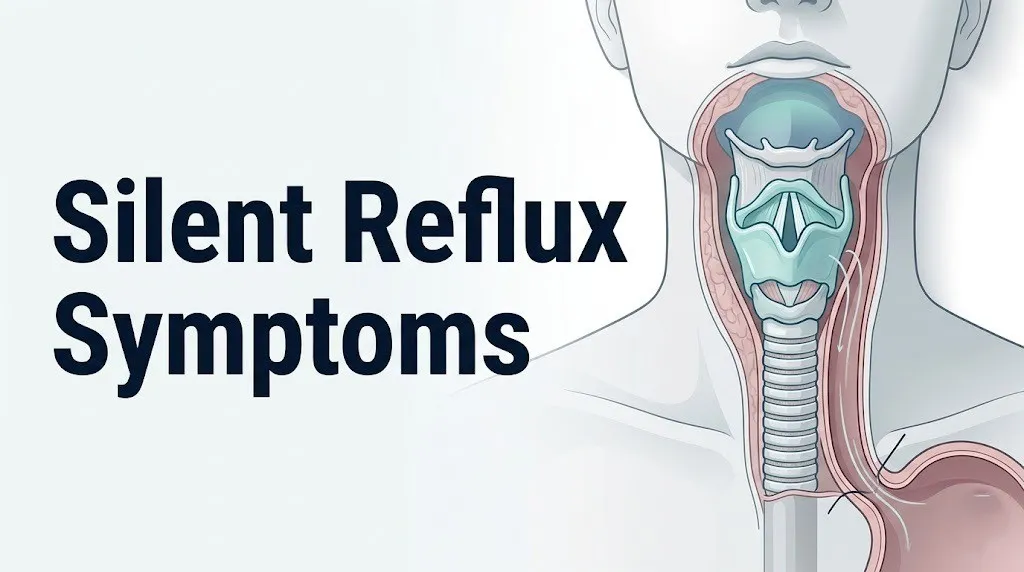
What sets LPR apart is that the esophageal lining, which has some tolerance for occasional acid exposure, is not the primary tissue under attack. The laryngeal mucosa, the vocal fold epithelium, and the posterior glottic region have essentially no protective buffering against even brief acid and pepsin contact. Even ten seconds of exposure to refluxate can trigger measurable mucosal inflammation in these structures.
Key symptoms overview:
- Chronic throat clearing (the most frequently reported first symptom)
- Persistent hoarseness or voice fatigue
- Sensation of something stuck in the throat (globus sensation)
- Chronic cough, especially after meals or at night
- Post-nasal drip sensation without confirmed nasal pathology
- Throat soreness, rawness, or burning unrelated to infection
- Breathing difficulties or mild stridor in severe cases
- Difficulty swallowing, especially with solid foods
Older adults, who have higher rates of hiatal hernia and decreased LES tone, often present with more prominent dysphagia. Children and infants present with an entirely different picture covered later in this article.
What Is Silent Reflux and How Does It Differ from GERD
Silent reflux, or laryngopharyngeal reflux, is distinct from gastroesophageal reflux disease (GERD) primarily because of where in the body the refluxate causes damage and which anatomical sphincter fails to contain it.
In classic GERD, the primary failure point is the lower esophageal sphincter (LES), a tonically contracted ring of smooth muscle at the gastroesophageal junction. When the LES relaxes transiently or loses baseline tone, gastric acid pools in the distal esophagus, producing the burning sensation of heartburn and, over time, esophageal mucosal injury (erosive esophagitis or Barrett’s esophagus).
In LPR, the critical additional failure involves the upper esophageal sphincter (UES), formed primarily by the cricopharyngeus muscle. This U-shaped striated muscle normally maintains a resting pressure of approximately 40 to 80 mm Hg and acts as the final barrier protecting the larynx and pharynx from refluxate. When UES tone is reduced or UES relaxation is poorly coordinated with peristalsis, gastric contents that have already passed the LES can travel through the UES and contact the laryngopharynx.
Think of it like a two-lock security system. GERD breaks through the bottom lock (LES) and damages the hallway (esophagus). LPR breaks through both locks and reaches the top floor, meaning the larynx, pharynx, and airway, where the tissue is far more vulnerable to damage.
The clinical consequence is that LPR and GERD can co-exist, but they can also occur independently. Research published in the Laryngoscope has documented patients with confirmed LPR on dual-probe pH monitoring who had normal esophageal acid exposure, meaning the esophagus was not being injured while the larynx was.
| Feature | GERD | LPR (Silent Reflux) |
|---|---|---|
| Primary symptom | Heartburn, regurgitation | Throat symptoms, cough, hoarseness |
| Heartburn present | Almost always | Absent in most cases |
| Primary failure point | Lower esophageal sphincter | Upper esophageal sphincter |
| Primary tissue injured | Esophageal mucosa | Laryngeal and pharyngeal mucosa |
| Acid dwell time | High (pooling in esophagus) | Low (brief laryngeal contact) |
| Nighttime predominance | Common | Very common (nocturnal aspiration) |
| Response to PPI therapy | Usually good | Variable, often incomplete |
Older adults and individuals with hiatal hernia are more likely to have both conditions simultaneously, which complicates diagnosis and treatment planning.
Laryngopharyngeal Reflux Symptoms: The Full Clinical Picture
Laryngopharyngeal reflux symptoms span the larynx, pharynx, and in some cases the tracheobronchial tree, producing a clinical picture that is often mistaken for chronic allergies, asthma, or a lingering post-viral infection.
The full clinical picture of LPR is best understood through the Reflux Symptom Index (RSI), a nine-item validated questionnaire used in otolaryngology practice. An RSI score of 13 or above is considered clinically abnormal and consistent with LPR. The nine domains assessed are: hoarseness or voice problems, throat clearing, excess throat mucus or post-nasal drip, difficulty swallowing, coughing after meals or lying down, breathing difficulties or choking episodes, troublesome or annoying cough, sensing something stuck in the throat, and heartburn, chest pain, or indigestion.
The Reflux Finding Score (RFS), used by otolaryngologists during flexible fiberoptic laryngoscopy, correlates the laryngoscopic appearance of the larynx with LPR severity. Features scored include subglottic edema, ventricular obliteration, erythema and hyperemia, vocal fold edema, diffuse laryngeal edema, posterior commissure hypertrophy, granuloma or granulation tissue, and thick endolaryngeal mucus. An RFS above 7 is considered abnormal.
According to the Annals of Otology, Rhinology and Laryngology, the most endoscopically common findings in confirmed LPR include posterior glottic erythema and interarytenoid pachydermia (thickening and cobblestoning of the mucosal tissue between the arytenoid cartilages). These changes are produced by direct contact injury from refluxate.
Women may present with more pronounced mucosal edema of the true vocal folds relative to men, potentially because estrogen-related tissue differences affect edema formation in vocal fold epithelium. This distinction has clinical relevance for voice-related symptoms in female patients.
LPR Symptoms in Adults: What Patients Most Often Report
LPR symptoms in adults are most frequently reported as a cluster of throat and voice complaints that develop gradually and are often attributed to other causes for months or years before LPR is identified.
The most commonly reported first symptom is throat clearing. Most patients describe an irresistible urge to clear the throat multiple times per day, particularly in the morning and after meals. This is not productive of phlegm. It is a reflex response triggered by the vagus nerve (cranial nerve X), which innervates both the laryngeal mucosa and the esophagus. Pepsin and acid deposited on the posterior glottic mucosa activate vagal afferent sensory fibers, producing the clearing reflex.
Voice-related symptoms are the second most reported cluster. Adults describe the voice as feeling tired after minimal use, cracking, dropping in pitch range, or sounding rougher than usual in the morning. These symptoms reflect edema and inflammatory changes in the true vocal folds (true vocal cords), which are highly sensitive to pH changes. Even a single episode of refluxate contact can produce mucosal edema sufficient to alter vocal fold vibration.
Research published in the Journal of Voice found that professional voice users including singers and teachers are disproportionately affected by LPR, not because they are biologically more prone to reflux but because even minor vocal fold mucosal changes are functionally significant in people whose voice is their occupational tool.
What makes adult LPR particularly difficult to recognize is the symptom chronicity. The National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) notes that LPR symptoms often persist for months without worsening in a way that triggers alarm. People attribute the chronic cough to allergies, the hoarseness to overuse, and the throat clearing to post-nasal drip.
Most commonly reported adult LPR symptoms by frequency:
- Throat clearing (most frequent, affecting the majority of LPR patients)
- Hoarseness or voice fatigue
- Post-nasal drip sensation
- Chronic cough
- Globus sensation (lump in throat)
- Throat soreness not associated with infection
- Dysphagia (difficulty swallowing), more common in moderate to severe cases
Adults over 60 are more likely to report dysphagia as a prominent feature because of age-related changes in esophageal peristaltic strength and UES tone. This population warrants earlier evaluation by an otolaryngologist.
Silent Acid Reflux Symptoms and Why Heartburn Is Often Absent
Silent acid reflux symptoms exist on a spectrum where the esophageal burning sensation of heartburn is absent or minimal, even though gastric acid is actively causing tissue damage higher up in the airway.
The reason heartburn is absent in LPR is physiologically specific. Heartburn is produced when acid remains in contact with the esophageal mucosa long enough to stimulate the nociceptive pain fibers in the esophageal wall, a process that requires sustained acid dwell time. In LPR, the refluxate clears the esophagus quickly and transiently contacts the laryngopharynx during proximal reflux events. The contact time in the esophagus is brief, meaning the esophageal mucosa does not accumulate sufficient injury to signal pain.
Meanwhile, the laryngeal and pharyngeal mucosa, even with brief contact lasting seconds, sustains measurable damage because it lacks the bicarbonate-rich mucus layer and the acid-buffering epithelial cell junctions that protect the esophagus to a degree.
The second reason heartburn is absent involves the pepsin mechanism. Research led by Dr. Jamie Koufman at the Voice Institute of New York, published in the Annals of Otology, Rhinology and Laryngology, established that pepsin, the proteolytic enzyme secreted by gastric chief cells as the precursor pepsinogen and activated by hydrochloric acid at pH below 3.5, is deposited in laryngeal mucosal cells during reflux events. Once inside the cell, pepsin can remain stable and active at pH levels up to 6.0, and it can be reactivated by subsequent acid exposure. This means laryngeal tissue damage can continue even when gastric acid is well-controlled, which is one reason many patients with LPR experience incomplete symptom resolution on proton pump inhibitor therapy alone.
According to the American College of Gastroenterology (ACG), distinguishing LPR from typical GERD requires attention to this proximal reflux mechanism and cannot rely on heartburn frequency as a reliable indicator of reflux severity.
People with diabetes who have gastroparesis (delayed gastric emptying due to vagal neuropathy) have increased LPR risk because prolonged gastric retention increases the frequency and volume of reflux events, even without elevated gastric acid levels.
Key Takeaway: Silent reflux can cause months of throat and voice symptoms with no heartburn because the laryngeal mucosa is injured by brief pepsin and acid contact that never lingers long enough in the esophagus to produce burning.
Silent Reflux Throat Symptoms: Soreness, Irritation, and Rawness
Silent reflux throat symptoms include a chronic raw or burning sensation in the posterior throat, intermittent sore throat unrelated to infection, and a feeling of heat or irritation that tends to worsen after meals, coffee, or alcohol.
The anatomical target in throat-specific LPR symptoms is the posterior cricoid region and the posterior pharyngeal wall, the mucosal surfaces that lie immediately adjacent to the esophageal inlet and are among the first laryngopharyngeal tissues contacted by proximal refluxate. Repeated chemical irritation from acid and pepsin produces submucosal edema, mucosal hyperemia (increased blood flow and redness), and over time, thickening and cobblestoning of the mucosa in a pattern called pachydermia laryngis.
Patients frequently describe the throat discomfort as “scratchy,” “raw,” or “feels like something is always mildly sore,” distinct from the acute stabbing pain of a bacterial pharyngitis. The soreness in LPR is typically worst in the morning, reflecting overnight accumulation of reflux events when the horizontal body position removes gravity as a barrier to proximal reflux.
The cough reflex triggered by laryngeal irritation produces its own cycle of throat injury. Each forceful cough creates a high-velocity airflow event that further traumatizes the already inflamed posterior glottic mucosa. This is why untreated LPR can progressively worsen throat symptoms even when gastric acid output remains stable.
To describe throat symptoms accurately to a clinician:
- Note whether soreness is constant or intermittent, and what time of day it is worst
- Identify whether soreness follows eating, drinking caffeine or alcohol, or lying down
- Note whether the soreness has ever been accompanied by visible swelling, difficulty swallowing, or fever (these combinations require different evaluation)
- Track whether voice quality changes alongside the throat soreness
- Note whether over-the-counter antacids provide temporary relief, which supports a reflux-related mechanism
Immunocompromised individuals, including those on long-term corticosteroid therapy or chemotherapy, should not assume throat soreness is LPR without excluding infectious laryngopharyngitis (including fungal infection such as oropharyngeal candidiasis), as these conditions can be clinically similar in appearance.
Silent Reflux Chronic Cough: Why It Happens and How to Recognize It
Silent reflux chronic cough is a persistent, dry, or minimally productive cough driven by laryngeal and vagal nerve hypersensitivity rather than by a lower respiratory tract pathology.
Chronic cough is defined clinically as a cough lasting more than eight weeks in adults. According to a clinical review published in JAMA, LPR (along with upper airway cough syndrome and asthma) accounts for the majority of chronic cough cases in non-smoking adults with a normal chest X-ray. LPR is estimated to be a contributing or primary cause in a substantial proportion of these cases, though exact percentages vary across studies because of diagnostic inconsistencies in LPR classification.
The mechanism is a sensitized cough reflex arc. The vagus nerve carries sensory fibers from the laryngeal mucosa, trachea, and bronchial tree. When the laryngeal mucosa is repeatedly irritated by refluxate, the afferent sensory threshold for the cough reflex drops. The result is a hypersensitive cough reflex that fires in response to stimuli that would not normally trigger coughing: cold air, laughing, speaking, perfume, and changes in air temperature.
Think of the cough reflex in LPR like a home alarm system that has been recalibrated after a break-in. It fires more easily, more frequently, and for weaker stimuli than before the tissue was sensitized. Fixing the alarm (treating the reflux) does not always immediately reset the threshold. Cough hypersensitivity can persist for months after reflux is controlled.
LPR cough characteristics that help distinguish it from cough caused by asthma or postnasal drip:
- Dry or minimally productive (not mucoid or purulent)
- Worsens after meals and in the evening or at night
- Often triggered by speaking, laughing, or changes in ambient temperature
- Accompanied by throat clearing and globus sensation
- Does not respond to antihistamines or nasal corticosteroids
- Partially or temporarily relieved by antacids or alkaline water in some patients
Women appear to have a lower cough reflex threshold than men at baseline, which is thought to involve differences in substance P signaling in vagal sensory pathways. This may explain the higher rates of chronic cough attributed to LPR in female patients.
LPR Hoarseness: When Your Voice Changes and What It Means
LPR hoarseness is a change in voice quality, pitch range, or vocal endurance caused by edema and inflammation of the true vocal folds (true vocal cords) and surrounding laryngeal structures.
The vocal folds are paired mucosa-covered bands of muscle and connective tissue within the larynx. They vibrate at frequencies between approximately 100 and 300 Hz in typical adult speech, with the vibratory pattern producing the fundamental frequency and overtones of the voice. When the epithelial surface of the true vocal folds becomes edematous (swollen with fluid) due to LPR-related mucosal inflammation, the vibratory pattern becomes irregular and the vocal folds no longer approximate (close) cleanly during phonation.
The audible result is a voice that sounds rough, breathy, low in pitch, or fatigued after minimal use. Patients often report that their voice is “better” mid-afternoon after morning fluid intake helps clear mucosal secretions, and “worse” first thing in the morning after overnight reflux events. This morning-predominant pattern is a reliable clinical feature of LPR-related hoarseness.
The Mayo Clinic identifies persistent hoarseness lasting more than two to four weeks as a symptom warranting evaluation by a board-certified otolaryngologist. This threshold is not arbitrary: hoarseness of this duration can also indicate vocal fold polyps, vocal fold paralysis, or in rare cases laryngeal carcinoma. LPR-related hoarseness and early laryngeal malignancy can appear similarly to the patient but are entirely different on laryngoscopy.
Specific laryngoscopic changes seen in LPR-related hoarseness include vocal fold erythema (redness), vocal fold edema, and in more severe or longstanding cases, Reinke’s edema (fluid accumulation in the superficial lamina propria of the vocal fold). Reinke’s edema is most common in smokers with concurrent LPR but can occur in non-smokers with severe LPR.
Singers, public speakers, and professional voice users who notice LPR-related hoarseness should consult a laryngologist (an otolaryngologist with subspecialty training in voice disorders) rather than waiting for symptoms to self-resolve, because continued vocal fold use in the presence of mucosal edema accelerates tissue injury.
Key Takeaway: LPR hoarseness is morning-predominant, worsens with voice use, and reflects true vocal fold edema from direct pepsin and acid contact. Hoarseness lasting more than four weeks requires laryngoscopic evaluation to rule out non-reflux causes including vocal fold lesions.
Silent Reflux Lump in Throat Feeling: Understanding Globus Sensation
The silent reflux lump in throat feeling, known clinically as globus pharyngeus or globus sensation, is the persistent feeling that something is stuck in the throat, typically without any difficulty swallowing food or liquids.
The key clinical distinction that makes globus a specific diagnostic entity is that swallowing is typically normal or even temporarily improved by swallowing, while the sensation returns between swallows. This differentiates it from true dysphagia (difficulty swallowing), where the act of swallowing itself is the problem.
The mechanism behind LPR-associated globus involves two pathways. The first is direct: edema and inflammation in the interarytenoid region (the mucosal tissue between the two arytenoid cartilages at the posterior glottis) and the posterior cricoid region produce a sensation of tissue fullness or a foreign body. The second is neurological: repeated acid and pepsin contact sensitizes vagal afferent sensory neurons in the laryngopharyngeal mucosa, creating a persistent abnormal sensory perception that the nervous system registers as a lump even when mucosal edema is mild.
According to a clinical analysis published in the Laryngoscope, LPR is identified as a contributing factor in a substantial proportion of patients presenting with globus sensation, though psychological factors including anxiety and stress also elevate globus reports through mechanisms involving the autonomic nervous system and altered pharyngeal muscle tone.
Globus associated with LPR typically:
- Is located in the mid-throat or just above the clavicle
- Persists between meals but may temporarily improve when eating or drinking
- Worsens during periods of stress or after acidic foods and beverages
- Is accompanied by throat clearing and voice changes
- Does not cause weight loss on its own
Globus sensation that worsens with swallowing rather than improving, or that is associated with unintentional weight loss, should be evaluated by a gastroenterologist with upper endoscopy (esophagogastroduodenoscopy, EGD) to exclude structural esophageal pathology. A board-certified gastroenterologist should be consulted when globus does not respond to a structured LPR treatment trial.
Silent Reflux and Post-Nasal Drip: Sorting Out What Is Actually Happening
Silent reflux and post-nasal drip frequently co-exist and are routinely confused because they share several overlapping throat symptoms including throat clearing, a sensation of mucus in the back of the throat, and chronic cough.
True post-nasal drip (now more precisely termed upper airway cough syndrome) is produced by increased mucus secretion from the nasal mucosa and sinuses, which drains posteriorly down the nasopharynx and triggers the cough and throat-clearing reflexes. LPR-associated mucus sensation, by contrast, is not primarily a mucus overproduction problem. It is a sensation of viscous secretions in the pharynx produced by submucosal gland hypersecretion in the laryngeal and pharyngeal mucosa in response to acid and pepsin irritation, combined with mucosal edema that alters the feel of normal secretions.
The practical clinical challenge is that both conditions can produce the same symptom pattern: throat clearing, cough, sensation of mucus dripping down the back of the throat, and a scratchy or irritated throat. Many patients have both simultaneously, and treating only one provides partial relief.
According to the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), LPR should be considered in any patient with persistent post-nasal drip that does not respond to antihistamine or nasal corticosteroid therapy, since the underlying driver may be laryngopharyngeal rather than nasal.
To differentiate LPR-related throat mucus from true nasal-origin post-nasal drip:
| Feature | LPR-Related Mucus Sensation | True Post-Nasal Drip |
|---|---|---|
| Source | Laryngeal/pharyngeal submucosal glands | Nasal and sinus mucosa |
| Nasal symptoms present | Usually absent | Usually present (congestion, rhinorrhea) |
| Responds to antihistamines | No | Often yes (if allergic) |
| Responds to nasal corticosteroids | No | Often yes |
| Worse after meals | Often | Rarely |
| Worse when lying down | Often | Variable |
| Throat clearing pattern | Constant, dry | More productive in mornings |
People with seasonal allergies and concurrent LPR represent a clinically challenging population because both conditions are simultaneously active. An allergist or otolaryngologist who evaluates these patients should assess both nasal and laryngeal sources before attributing all symptoms to one cause.
Key Takeaway: The mucus sensation in silent reflux is not excess nasal mucus but rather pharyngeal submucosal gland secretion triggered by acid and pepsin contact. When post-nasal drip does not improve with nasal treatments, LPR should be assessed as the primary driver.
Silent GERD Symptoms at Night: The Nocturnal Reflux Problem
Silent GERD symptoms at night represent one of the most clinically problematic patterns of LPR because the recumbent body position removes gravity as a mechanical barrier to proximal reflux, leading to prolonged laryngeal and pharyngeal contact with refluxate during sleep.
During sleep, three factors converge to amplify LPR. First, swallowing frequency drops from approximately 72 swallows per hour during waking to fewer than 5 per hour during sleep. Swallowing is the primary mechanism for clearing refluxate from the esophagus back to the stomach, so the dramatic reduction in nocturnal swallowing allows refluxate to remain in contact with pharyngeal and laryngeal surfaces longer. Second, the supine position eliminates the gravitational gradient that normally keeps gastric contents below the gastroesophageal junction. Third, nocturnal cough and throat clearing, which would normally expel laryngeal irritants, are suppressed during deep sleep, allowing prolonged mucosal contact.
The result is that patients with nocturnal LPR often wake with more severe morning hoarseness, more pronounced throat soreness, and a stronger globus sensation than they experience during daytime hours. Morning symptoms peaking before improving throughout the day is a reliable clinical pattern pointing to nocturnal reflux as a dominant mechanism.
The Mayo Clinic recommends elevating the head of the bed by 6 to 8 inches (not just using extra pillows, which flex the neck without elevating the torso) as a first-line postural intervention for nocturnal LPR. This elevation maintains a gravitational gradient across the gastroesophageal junction during sleep.
Patients with obstructive sleep apnea (OSA) have an amplified nocturnal LPR risk through a specific pressure mechanism: the repeated cycles of upper airway collapse and forceful inhalation against an obstructed airway create negative intrathoracic pressure that draws gastric contents proximally. Research published in the Laryngoscope has documented a statistically notable association between OSA and LPR, with some evidence suggesting treatment of OSA improves LPR symptoms.
Eating within two to three hours of lying down substantially increases nocturnal reflux frequency because gastric distension from a recent meal increases transient lower esophageal sphincter relaxation events through vagal mechanoreceptor signaling.
Silent Reflux Breathing Problems: When LPR Affects the Airway
Silent reflux breathing problems occur when refluxate or pepsin-mediated inflammation extends below the larynx into the subglottic space, trachea, or bronchial tree, triggering airway hypersensitivity, intermittent bronchoconstriction, or subglottic mucosal edema.
The proximity of the laryngeal inlet to the trachea means that during significant proximal reflux events, microaspiration of small amounts of refluxate into the airway below the vocal folds is physiologically possible. This microaspiration, even without producing overt choking, deposits acid and pepsin on the tracheal and bronchial epithelium, triggering inflammatory responses that manifest as airway symptoms: wheeze, breathlessness, tightness, or a choking sensation.
Patients sometimes describe a sensation of being unable to take a full deep breath, particularly at night or early in the morning. This is not the same as the progressive dyspnea of a pulmonary condition. It is typically intermittent, position-dependent, and often accompanied by the throat symptoms described in earlier sections.
In its most severe form, LPR can produce subglottic edema, swelling of the mucosal tissue beneath the true vocal folds. Because the subglottis is the narrowest part of the adult airway, even moderate edema at this location can produce stridor (a high-pitched, stridulous breath sound indicating partial airway obstruction). This presentation is rare in adult LPR but warrants emergency evaluation.
According to the AAO-HNS, chronic LPR has been proposed as a contributing factor in recurrent laryngospasm (an involuntary closure of the vocal folds triggered by laryngeal sensory hypersensitivity) in some patients, though the evidence base for this association is still developing from observational data.
People with pre-existing chronic obstructive pulmonary disease (COPD) are at greater risk for LPR-triggered respiratory exacerbations because their airway is already in a state of chronic inflammation and hyperreactivity. Unexplained respiratory exacerbations in a COPD patient without an infectious trigger should prompt evaluation for LPR by a pulmonologist and otolaryngologist working collaboratively.
Silent Reflux Symptoms in Infants: A Completely Different Presentation
Silent reflux symptoms in infants look nothing like the adult presentation and are often misattributed to colic, feeding intolerance, or behavioral issues.
In infants, the lower esophageal sphincter is physiologically immature at birth and does not achieve adult-level tone until approximately 12 to 14 months of age. This means that reflux of gastric contents is normal in infants, occurring in the majority of healthy newborns. The clinical problem arises when reflux produces pharyngeal and laryngeal inflammation, respiratory symptoms, or feeding difficulties, at which point it becomes pathological.
Infant silent reflux symptoms are not throat clearing and hoarseness. They are:
- Arching the back during or after feeds (a reflex response to laryngeal and esophageal pain)
- Feeding refusal or pulling off the breast or bottle repeatedly
- Irritability and crying during or after feeding not explained by hunger or gas
- Wet or “gurgly” sounding breathing between feeds
- Recurrent stridor or a hoarse-sounding cry
- Recurrent respiratory infections or episodes of apparent life-threatening events (ALTEs)
- Poor weight gain when reflux is severe enough to interfere with caloric intake
- Nighttime restlessness and arched posturing during sleep
The American Academy of Pediatrics (AAP) distinguishes between typical infant GER (gastroesophageal reflux), which is a developmental norm requiring no treatment, and GERD/LPR in infants, which requires medical evaluation when associated with poor weight gain, respiratory symptoms, or significant behavioral distress.
A pediatric gastroenterologist or a pediatric otolaryngologist should evaluate infants with suspected LPR. Clinical assessment in infants may include pH-impedance monitoring, upper gastrointestinal series, or flexible laryngoscopy in specific presentations involving recurrent stridor or hoarseness. Do not apply adult LPR management strategies to infants without pediatric specialist guidance.
Key Takeaway: Infant silent reflux presents as back-arching, feeding refusal, respiratory symptoms, and irritability, not as throat clearing or hoarseness. The American Academy of Pediatrics recommends specialist evaluation when infant reflux is associated with weight loss or respiratory symptoms.
Silent Reflux and Asthma Connection: Shared Mechanisms and Overlapping Symptoms
The silent reflux and asthma connection is bidirectional, clinically well-documented, and mechanistically explained by shared vagal nerve pathways and airway inflammatory responses that amplify both conditions simultaneously.
LPR can trigger bronchoconstriction through two distinct mechanisms. The first is a neurogenic reflex: acid or pepsin contact with the laryngeal or distal esophageal mucosa activates vagal afferent fibers that carry sensory signals to the brainstem, which in turn generates efferent vagal signals producing bronchial smooth muscle contraction. No acid needs to enter the airway for this reflex to occur. The second mechanism is direct aspiration: microaspirated refluxate reaching the bronchial epithelium activates mast cells and eosinophils, triggering local inflammatory responses that include bronchoconstriction, mucus hypersecretion, and airway edema.
Conversely, asthma promotes LPR. The forceful negative intrathoracic pressure generated during asthmatic breathing episodes creates a pressure gradient that draws gastric contents into the esophagus and proximally toward the larynx. High-dose inhaled corticosteroids used in asthma management may also reduce UES tone through local effects on cricopharyngeal muscle, promoting proximal reflux.
Research published in JAMA has found that patients with asthma have higher rates of LPR confirmed by pH monitoring than the general population, and that some patients with “difficult-to-control asthma” show meaningful improvement in asthma symptom burden when LPR is treated concurrently.
Clinical clues that asthma symptoms may have a concurrent LPR component:
- Asthma that is worse at night and in the morning
- Asthma that worsens after meals
- Asthma that does not respond fully to appropriate inhaled therapy
- Concurrent hoarseness, throat clearing, or globus sensation alongside the breathing symptoms
- A chronic cough that persists between asthma episodes
Patients with asthma and suspected concurrent LPR should be evaluated by both a pulmonologist (for asthma management optimization) and an otolaryngologist (for LPR assessment), with coordinated management addressing both conditions.
Silent Reflux Triggers and Individual Risk Factors
Silent reflux triggers are dietary, behavioral, anatomical, and physiological factors that increase the frequency or volume of reflux events reaching the laryngopharynx, or that reduce the protective mechanisms that normally prevent refluxate from reaching the upper airway.
The primary anatomical risk factor is a hiatal hernia, a structural condition in which a portion of the stomach herniates through the diaphragmatic hiatus into the thoracic cavity. Hiatal hernia mechanically disrupts the normal anti-reflux barrier at the gastroesophageal junction, increasing the frequency of transient lower esophageal sphincter relaxations and reducing the effectiveness of the LES. The American College of Gastroenterology (ACG) identifies hiatal hernia as one of the strongest anatomical predisposors to both GERD and LPR.
Obesity increases intra-abdominal pressure, which mechanically pushes the stomach upward against the LES, promoting reflux. A 2023 clinical analysis summarizing multiple cohort studies found that body mass index (BMI) above 30 kg/m squared was associated with higher rates of both GERD and LPR compared to individuals with BMI in the normal range.
Dietary triggers that reduce LES tone or stimulate gastric acid production:
- Caffeine (coffee, tea, energy drinks): reduces LES pressure via adenosine receptor effects on smooth muscle
- Alcohol: reduces LES tone through direct smooth muscle relaxant effects and increases gastric acid secretion
- High-fat meals: stimulate cholecystokinin release, which mediates TLESR and delays gastric emptying
- Carbonated beverages: increase intragastric pressure through gas volume, promoting TLESR
- Chocolate: contains methylxanthines that relax smooth muscle including the LES
- Peppermint: relaxes LES through calcium channel effects on esophageal smooth muscle
- Acidic foods: tomatoes, citrus fruits, vinegar-based dressings, directly damage sensitized laryngeal mucosa
Hormonal factors matter significantly. Progesterone is a smooth muscle relaxant that reduces LES tone through its effect on cyclic AMP pathways in esophageal smooth muscle. This explains why pregnant women have dramatically elevated rates of reflux, including LPR, as progesterone levels rise throughout pregnancy.
Tight clothing and belts that increase intra-abdominal pressure, large meal volumes, eating rapidly, and being in a recumbent position within two hours of eating all increase reflux event frequency independent of diet composition.
Silent Reflux Red Flags and When to See a Doctor
Silent reflux red flags are symptoms or patterns that require prompt professional evaluation rather than watchful waiting or self-management, because they may indicate a complication of LPR or a separate condition that can mimic LPR.
The most concerning red flag is progressive dysphagia, meaning difficulty swallowing that is worsening over weeks and now involves solid food, or that has progressed from solids to liquids. Progressive dysphagia can indicate esophageal stricture (narrowing caused by chronic acid injury or another structural process), eosinophilic esophagitis (an immune-mediated esophageal inflammatory condition frequently confused with LPR or GERD), or esophageal malignancy. A board-certified gastroenterologist should evaluate progressive dysphagia with upper endoscopy (esophagogastroduodenoscopy, EGD) without delay.
Persistent hoarseness lasting more than four weeks requires evaluation by an otolaryngologist (ENT specialist) for flexible laryngoscopy. The AAO-HNS clinical consensus statement identifies four-week hoarseness duration as the threshold for specialist referral because this presentation overlaps with early-stage laryngeal carcinoma, which shares hoarseness as a primary symptom and is treatable with high cure rates when identified early.
Additional red flags requiring prompt medical evaluation:
- Unintentional weight loss of more than five percent of body weight over one to two months
- Coughing or spitting up blood (hemoptysis or hematemesis), which requires same-day emergency evaluation
- Throat pain severe enough to prevent normal eating or drinking
- A visible neck mass or lymph node enlargement persisting more than two to three weeks
- Voice hoarseness that is rapidly worsening rather than stable or intermittent
- Nighttime choking episodes severe enough to wake from sleep with respiratory distress
When to contact which provider:
| Symptom or Pattern | Provider to Contact | Urgency |
|---|---|---|
| Persistent hoarseness over 4 weeks | Otolaryngologist (ENT) | Within 1 to 2 weeks |
| Progressive dysphagia | Gastroenterologist | Within 1 week |
| Unintentional weight loss | Primary care physician | Within 1 week |
| Hemoptysis or hematemesis | Emergency room | Same day or immediately |
| Symptoms not improving after 8 to 12 weeks of lifestyle modification | Primary care physician | Schedule appointment |
| Breathing difficulty or stridor | Emergency room or 911 | Immediately |
| Visible neck mass | Otolaryngologist or primary care | Within 2 weeks |
Key Takeaway: Hoarseness lasting longer than four weeks, progressive swallowing difficulty, or unexplained weight loss are not symptoms to monitor at home. Each requires evaluation by a named specialist within a defined timeframe, not an open-ended “we’ll watch and see” approach.
How Silent Reflux Is Diagnosed
Silent reflux is diagnosed through a combination of clinical symptom assessment using validated tools, physical laryngoscopic examination, and in selected cases, objective pH and impedance monitoring of the esophagus.
The first clinical step is typically the Reflux Symptom Index (RSI), a nine-question validated questionnaire that takes approximately two minutes to complete. Patients rate the severity of nine symptoms on a scale of 0 to 5, with higher scores reflecting greater symptom burden. An RSI score of 13 or above is considered clinically abnormal and indicative of LPR. The RSI was validated in a study published in the Journal of Voice by Belafsky and colleagues and is widely used in otolaryngology and primary care settings.
The second step in specialist evaluation is flexible fiberoptic laryngoscopy, in which a thin, flexible endoscope is passed through the nostril and positioned above the larynx to directly visualize the laryngeal structures. Findings are scored using the Reflux Finding Score (RFS). An RFS above 7 is considered abnormal. Key findings include posterior glottic erythema, interarytenoid pachydermia, vocal fold edema, and subglottic edema.
The gold standard for objective LPR diagnosis is ambulatory dual-probe pH-impedance monitoring, in which a thin catheter is placed transnasally with two pH sensors positioned at the hypopharyngeal level and the distal esophagus, along with impedance sensors that detect both acid and non-acid reflux events over a 24-hour period. This test is ordered when the clinical picture is ambiguous, when symptoms do not respond to empirical treatment, or when the diagnosis needs objective confirmation before surgical intervention.
Upper endoscopy (EGD) is ordered when dysphagia is present, when there is concern for Barrett’s esophagus (a precancerous change in the distal esophageal lining), or when LPR-related symptoms have been present for more than five to ten years in older adults. High-resolution esophageal manometry assesses UES and LES pressures and esophageal peristaltic function and is ordered when a motility disorder is suspected as a contributing factor.
Patients over 50 who have longstanding GERD or LPR symptoms and who are evaluated for the first time should discuss Barrett’s esophagus screening with their gastroenterologist, since Barrett’s esophagus carries an elevated risk for esophageal adenocarcinoma and is an incidental finding during routine EGD in a meaningful proportion of long-term reflux patients.
Emergency Symptoms: When to Call 911 or Go to the ER
Certain symptoms associated with silent reflux and laryngopharyngeal reflux require immediate emergency evaluation. Do not wait to see if these resolve on their own.
Call 911 or go to the nearest emergency room immediately if you experience:
- Stridor: a high-pitched, harsh breathing sound audible without a stethoscope, indicating partial laryngeal or subglottic airway obstruction. This is an airway emergency regardless of cause.
- Severe or sudden breathing difficulty: any new-onset respiratory distress, inability to take a full breath, or labored breathing associated with throat symptoms.
- Inability to swallow saliva: drooling or pooling of saliva because swallowing is blocked indicates a rapidly progressive process that requires emergency laryngeal evaluation.
- Sudden severe throat pain combined with difficulty breathing or muffled voice in a person with no prior diagnosis, which can indicate epiglottitis (an infectious emergency requiring immediate airway management).
- Coughing or vomiting blood: any hemoptysis (coughing blood) or hematemesis (vomiting blood) requires same-day emergency evaluation.
- Rapid-onset voice loss combined with throat swelling and breathing difficulty, which can indicate an acute allergic or angioedematous reaction at the laryngeal level.
These presentations can indicate laryngeal edema, epiglottitis, subglottic stenosis, or angioedema of the larynx, all of which can progress to complete airway obstruction and require emergency medical assessment, not an urgent care appointment or a phone call to your primary care physician.
Frequently Asked Questions About Silent Reflux Symptoms
What are the most common silent reflux symptoms in adults?
The most common silent reflux symptoms in adults are throat clearing, hoarseness, a lump-in-the-throat sensation (globus pharyngeus), chronic cough, and post-nasal drip sensation, often without any heartburn.
These symptoms are produced when gastric acid and pepsin reach the larynx and pharynx through the upper esophageal sphincter, damaging the laryngeal mucosa without causing the esophageal burning of typical GERD.
According to the validated Reflux Symptom Index (RSI), published in the Journal of Voice, an RSI score of 13 or above is the clinical threshold for suspected LPR.
Can you have silent reflux without any heartburn at all?
Yes. Silent reflux can occur entirely without heartburn because the refluxate contacts the larynx and pharynx briefly, without lingering in the esophagus long enough to produce esophageal mucosal pain.
The laryngeal mucosa is damaged by even seconds of acid and pepsin contact, while the esophageal pain of heartburn requires sustained acid exposure in the distal esophagus.
According to the American College of Gastroenterology, the absence of heartburn does not rule out LPR and should not delay evaluation when throat and voice symptoms are persistent.
How long does silent reflux take to go away?
Silent reflux symptoms typically take several weeks to months to improve even with appropriate treatment, because the laryngeal and pharyngeal mucosal inflammation that drives symptoms resolves slowly.
The American Academy of Otolaryngology-Head and Neck Surgery recommends a minimum trial of eight to twelve weeks of lifestyle modification and dietary change before assessing treatment response.
Patients whose symptoms have not improved after twelve weeks of structured management should be re-evaluated by an otolaryngologist for formal LPR assessment including laryngoscopy.
What does silent reflux feel like in the throat?
Silent reflux typically feels like a persistent raw or scratchy soreness at the back of the throat, a sensation of mucus or thickness, or the feeling that something is stuck just above the collarbone.
The soreness is usually not as acute as a sore throat from infection, tends to be worst in the morning, and is often accompanied by an urge to clear the throat repeatedly.
Throat symptoms from LPR reflect direct mucosal inflammation in the posterior cricoid region and interarytenoid area caused by pepsin and acid contact.
Is silent reflux the same as LPR?
Silent reflux and laryngopharyngeal reflux (LPR) are the same condition, with “silent reflux” being the common name and “laryngopharyngeal reflux” being the clinical diagnostic term.
Both terms refer to reflux of gastric contents, primarily acid and pepsin, reaching the larynx and pharynx and causing throat, voice, and airway symptoms rather than heartburn.
The condition is also sometimes called extraesophageal reflux (EER) in gastroenterology literature, all three terms describing the same underlying pathophysiology.
When should I see a doctor about silent reflux symptoms?
You should see a primary care physician if throat clearing, hoarseness, cough, or other LPR symptoms have persisted for more than two to four weeks without a clear cause.
Referral to an otolaryngologist (ENT specialist) is warranted for hoarseness lasting more than four weeks, any difficulty swallowing, or symptoms that do not improve after eight weeks of dietary and lifestyle modification.
See a doctor the same day or go to the emergency room immediately for any breathing difficulty, stridor, inability to swallow saliva, or coughing blood.
What You Should Do With This Information
Silent reflux can run quietly for months before anyone connects the chronic cough, the morning hoarseness, and the throat discomfort to gastric contents reaching the larynx. The most practical thing to take from this article is that these symptoms are not vague or ambiguous. They follow a recognizable clinical pattern, they have specific physiological causes rooted in the mechanics of the upper and lower esophageal sphincters, and they respond to structured assessment and management.
Start by tracking your symptoms against the Reflux Symptom Index domains: throat clearing, hoarseness, cough, post-nasal drip, swallowing, breathing discomfort, globus sensation, and any heartburn. If your score pattern is consistent with what is described here and the symptoms have lasted more than two to four weeks, contact your primary care physician and bring a written log of your symptoms, their timing, and what makes them better or worse.
If you have hoarseness lasting longer than four weeks, request a referral to a board-certified otolaryngologist for laryngoscopic evaluation. That visit, and the laryngoscopic findings it produces, will give you a far more specific answer than any symptom checker can.