Broken Toe Symptoms: Full Guide to Signs and Pain 2026
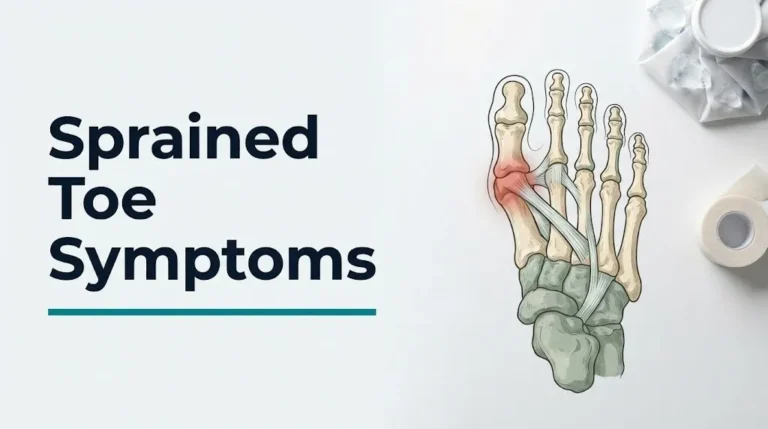
Broken toe symptoms include sharp, immediate pain at the site of injury, rapid swelling, visible bruising, and difficulty bearing weight on the affected foot. The exact pattern of symptoms depends on which toe is fractured, the type of fracture, and whether any of the injured bone has shifted out of its normal alignment.
Toe fractures are among the most common foot injuries treated in emergency rooms and urgent care clinics. According to the American Academy of Orthopaedic Surgeons, fractures of the phalanges (the small bones forming each toe) account for a large proportion of foot fractures seen in clinical practice, affecting people across all age groups and activity levels. The fifth toe (the pinky toe) is fractured more often than any other, primarily due to its exposed position on the outer edge of the foot.
This article covers every clinically recognized symptom of a broken toe, explains the precise anatomical and physiological reason each symptom occurs, distinguishes fracture from sprain, identifies which presentations require emergency room evaluation versus same-day urgent care versus a primary care appointment, and addresses how symptoms differ across specific populations including children, people with diabetes, and athletes.
Broken Toe Symptoms: The Complete Clinical Picture
Broken toe symptoms typically include sudden, intense pain at the fracture site, progressive swelling over the first 24 to 48 hours, visible bruising that may spread beyond the injured toe, tenderness with direct touch or pressure, and difficulty wearing shoes or walking normally.
The phalanges, the three small bones in each toe (or two in the great toe), are covered by the periosteum, a dense fibrous membrane packed with sensory nerve endings called nociceptors. When a phalanx fractures, the periosteum tears at the fracture line. This rupture directly stimulates those nociceptors, which are innervated by branches of the medial and lateral plantar nerves (themselves branches of the tibial nerve). The result is immediate, localized, sharp pain that most people describe as unlike any stubbing sensation they have had before.
Within minutes, the local inflammatory response begins. Tissue damage triggers the release of prostaglandin E2 (via the cyclooxygenase-2, or COX-2, pathway), bradykinin (via the plasma kinin cascade), and substance P from nociceptive C-fibers. These mediators increase local vascular permeability and cause vasodilation, which produces the edema and warmth that appear over the following hours.
Key symptoms to recognize across all toe fractures:
- Sudden, sharp pain immediately after the injury, worsening with touch or movement
- Swelling developing within 15 to 30 minutes of the injury
- Bruising (ecchymosis) appearing over the first 12 to 24 hours
- Tenderness to direct pressure over the injured bone
- Pain with weight-bearing or difficulty placing the foot flat on the floor
- Visible deformity or abnormal angle of the toe (in displaced fractures)
- A popping, cracking, or snapping sensation at the moment of injury (not always present)
People who take nonsteroidal anti-inflammatory drugs (NSAIDs) regularly for another condition may notice that their pain and swelling appear somewhat less intense in the first hours after injury, because NSAIDs partially block the COX-2 prostaglandin pathway. This does not mean the fracture is less serious; it means the inflammatory signal is chemically suppressed. This is an important consideration when assessing pain level as a severity indicator.
Symptoms of a Broken Toe That Show Up in the First Hour
The symptoms of a broken toe that appear within the first 60 minutes after injury are the most clinically useful for initial self-assessment, though they cannot replace radiographic confirmation.
The first and most consistent early symptom is point tenderness: pain that is precisely localized to the site of the fracture when you press directly on the bone. With a simple bruise or soft tissue injury, tenderness tends to be diffuse. With a fracture, pressing on the bone itself, even gently, produces disproportionate pain. This reflects direct mechanical stimulation of the ruptured periosteal nociceptors at the fracture line.
Within 15 to 30 minutes, pitting edema begins to develop over the dorsal (top) surface of the toe. Edema at this stage is driven by histamine release from mast cells in the periosteal connective tissue and by bradykinin-mediated increase in capillary permeability. The tissue around the injury becomes visibly puffy and feels tense to the touch.
According to MedlinePlus, published by the U.S. National Library of Medicine, the inability to move the toe through its normal range of motion without sharp pain is one of the early distinguishing features of fracture versus sprain, though this distinction requires clinical confirmation.
Early signs in the first 60 minutes:
| Symptom | When It Appears | Clinical Significance |
|---|---|---|
| Point tenderness over bone | Immediately | Strongest early fracture indicator |
| Swelling at injury site | 15 to 30 minutes | Inflammatory edema beginning |
| Limited range of motion | 15 to 45 minutes | Splinting reflex protecting the fracture |
| Warmth at the site | 30 to 60 minutes | Local vasodilation from inflammatory mediators |
| Initial bruising (faint) | 45 to 90 minutes | Periosteal hemorrhage beginning to track |
| Difficulty weight-bearing | Immediate to 30 minutes | Axial load pain from fractured cortex |
Older adults, particularly those over 65, may not experience the same immediate intensity of pain because of age-related changes in peripheral nerve conduction velocity. A fracture in this age group can initially feel like a moderate ache rather than sharp pain, which can delay care-seeking by hours to days.
What Does a Broken Toe Feel Like? The Exact Sensation Described
A broken toe typically feels like a sudden, deep, bone-level pain that is sharper and more localized than the broad aching pain of a bruised soft tissue injury, and it is consistently worsened by any direct pressure on the bone.
The qualitative character of fracture pain is specific enough that experienced clinicians use patient description as a primary pre-radiograph assessment tool. The pain of a fractured phalanx is most often described as a burning, throbbing, or “deep” ache that sits directly at the bone level rather than in the surrounding muscles or skin. This specific quality reflects the density of nociceptors in the periosteum compared to overlying soft tissue. The periosteum has one of the highest densities of sensory nerve endings of any tissue in the body.
Think of it this way: the periosteum surrounding a phalanx works like an alarm system hardwired directly to the bone. Any disruption of the bone surface, even a non-displaced hairline fracture, trips that alarm immediately. A bruise, by contrast, damages the soft tissue above the bone, which has a different, less acute sensory nerve distribution.

The pain typically has these specific characteristics:
- Sharp and immediate at the moment of fracture, often described as a “bright,” “electric,” or “stabbing” sensation
- Throbbing and constant in the first hours as inflammatory mediators accumulate
- Worsened significantly by any attempt to move the toe or bear weight
- Precisely located, meaning the person can point to the exact spot on the bone that hurts most
- Different from previous toe-stubbing experiences, a feature patients frequently report unprompted
Athletes who fracture a toe during competition sometimes describe a brief window of 10 to 20 minutes where the pain temporarily decreases. This reflects a transient endorphin and epinephrine release from the acute stress response. The pain returns fully once the adrenaline response fades and the inflammatory cascade accelerates.
Broken Toe Swelling and Bruising: Why They Look the Way They Do
Broken toe swelling appears within minutes to hours of the fracture and can be severe enough to make it impossible to put on a shoe; bruising typically develops over 12 to 72 hours and often spreads to adjacent toes and the top of the foot.
The swelling pattern is driven by two mechanisms. First, the local inflammatory response increases the permeability of capillary walls in the fractured phalanx’s surrounding tissue, allowing protein-rich fluid to move from the bloodstream into the interstitial space, creating inflammatory edema. Second, blood escaping from ruptured periosteal blood vessels and from the cortical bone marrow at the fracture site accumulates in the surrounding soft tissue, contributing to a firm, tense swelling that does not pit with finger pressure as cleanly as pure edema does.
The bruising pattern is anatomically informative. The digital venous plexus of the foot is an interconnected network of veins running along the dorsal and plantar surfaces of the toes. When blood from the fracture site enters this network, gravity and fascial plane anatomy allow it to spread. Bruising often appears on the top (dorsal surface) of the foot, on the bottom of the toe, or on the adjacent toes, even when the actual fracture is well-localized. This spread of bruising beyond the site of injury does not mean the injury is worse than suspected; it reflects vascular anatomy.
According to the American College of Foot and Ankle Surgeons, significant swelling and discoloration that extends beyond the injured toe into the foot itself can indicate either a more complex fracture pattern or an associated soft tissue injury such as a plantar plate tear.
Swelling and bruising severity varies by age. Younger adults tend to develop bruising more quickly and more visibly due to higher capillary perfusion. Older adults on blood-thinning medications (anticoagulants such as warfarin or apixaban) may develop extensive, dark bruising that looks alarming but reflects the medication’s effect on clot formation, not necessarily a more severe fracture.
Key Takeaway: The most reliable early indicator of a broken toe is point tenderness directly over the bone, not the severity of bruising or swelling, which can appear dramatically in soft tissue injuries and be muted in early fractures.
Fractured Toe Symptoms by Fracture Type
The specific symptoms of a fractured toe vary depending on the type of fracture, and different fracture patterns produce distinctly different clinical presentations.
The American Academy of Orthopaedic Surgeons classifies toe fractures into several types that produce different symptom profiles:
| Fracture Type | Mechanism | Key Symptoms | Urgency |
|---|---|---|---|
| Non-displaced (hairline) | Axial force or stress | Localized pain, mild swelling, no deformity | Urgent care within 24 hours |
| Displaced fracture | Direct impact or twisting | Pain, deformity, toe points abnormal direction | Same-day orthopedic evaluation |
| Avulsion fracture | Tendon or ligament pull at impact | Pain at tendon insertion, swelling at base or tip | Urgent care within 24 hours |
| Comminuted fracture | Crush injury | Severe pain, extensive swelling, multiple fracture fragments | Emergency room same day |
| Intraarticular fracture | Force through joint surface | Joint-level pain, stiffness, rapid swelling | Same-day or emergency evaluation |
| Open fracture | Bone penetrates skin | Bone visible, wound open, bleeding | Call 911 or go to the ER immediately |
| Tuft fracture (distal) | Crush at tip of toe | Pain at toe tip, nail bed disruption, subungual hematoma | Urgent care same day |
An avulsion fracture occurs when a tendon or ligament attached to the phalanx pulls a fragment of bone away from the main shaft during a forceful movement. This is particularly common at the base of the fifth metatarsal and at the attachment point of the plantar plate in the great toe. The symptom pattern differs from a typical shaft fracture: the pain is more precisely located at the tendon insertion point, and the swelling tends to be more localized rather than diffuse.
An intraarticular fracture extends into the joint surface of the metatarsophalangeal joint or interphalangeal joint. These fractures are clinically important because joint surface damage increases the risk of long-term post-traumatic arthritis if not treated correctly. The symptom that distinguishes an intraarticular fracture from a shaft fracture is that the pain and swelling are centered at the joint itself rather than along the bone shaft.
Women with osteoporosis fracture the phalanges more easily than the general population, often from forces that would not fracture healthy bone. Research published in the Journal of Bone and Joint Surgery confirms that postmenopausal women with low bone mineral density are at elevated risk of stress and insufficiency fractures of the foot, including the lesser toes, from normal daily activities rather than discrete trauma.
Stress Fracture Toe Symptoms: The Slow-Burn Warning Sign
Stress fracture toe symptoms develop gradually over days to weeks rather than appearing suddenly after a single injury, and they are typically described as a dull, aching pain that worsens with activity and improves with rest.
A stress fracture (also called a march fracture when it occurs in the metatarsals or proximal phalanges of the lesser toes) is produced by repetitive mechanical loading that exceeds the bone’s capacity for remodeling. Unlike acute fractures, where the cortical bone fails in a single event, a stress fracture develops when osteoclast activity (bone resorption) temporarily outpaces osteoblast activity (bone formation) during periods of increased physical demand. A small crack propagates through the weakened cortical bone over time.
The symptom pattern is distinct from acute fracture:
- Dull, aching pain that begins during or after activity and gradually starts to appear earlier in the activity session
- Pain that eases significantly with rest in early stages but becomes persistent with continued activity
- Swelling that is mild and localized, often with minimal or no bruising
- Point tenderness over the fracture site that may be less dramatic than in an acute fracture
- Pain that is present during the push-off phase of the walking stride as the toe bears load
Research published in Foot and Ankle International found that stress fractures of the proximal phalanx of the second toe are frequently misidentified as capsulitis (inflammation of the metatarsophalangeal joint capsule) in the early stages, because both conditions produce pain at the base of the second toe that worsens with activity.
Distance runners and military recruits are at the highest risk of phalangeal stress fractures. Women athletes are at elevated risk compared to male athletes, particularly those with the female athlete triad: low energy availability, menstrual dysfunction, and low bone mineral density, a triad recognized by the American College of Sports Medicine. Plain radiographs often appear normal in the first two to three weeks of a stress fracture; MRI is the preferred imaging tool for early detection.
Broken Pinky Toe Symptoms: Why the Fifth Toe Is Different
Broken pinky toe symptoms include sharp lateral foot pain, rapid swelling along the outer edge of the foot, and bruising that frequently extends onto the sole of the foot, and this fracture requires specific attention because it is frequently confused with an avulsion fracture at the base of the fifth metatarsal.
The fifth phalanx (pinky toe) occupies the most exposed position on the lateral border of the foot, making it the most commonly fractured toe. The typical mechanism is a “stubbing” injury where the toe strikes a hard object or an inversion (rolling) injury where the foot rolls outward. The proximal phalanx of the fifth toe is the most commonly fractured segment.
Symptoms specific to a broken pinky toe:
- Immediate pain along the outer edge of the foot and the small toe
- Swelling that extends from the little toe toward the outer ankle
- Bruising that appears on the lateral sole and outer dorsum of the foot
- Difficulty wearing any closed-toe shoe due to pressure on the lateral border
- Pain with any attempt to push off from the fifth toe during walking
A critical clinical distinction: an avulsion fracture at the base of the fifth metatarsal (the Jones fracture zone and the dancer’s fracture) produces symptoms that feel very similar to a broken pinky toe but involves a different bone entirely. The American College of Foot and Ankle Surgeons notes that fifth metatarsal base fractures require different management than phalangeal fractures, which is why radiographic evaluation is necessary to distinguish them.
Athletes and active adults who repeatedly sprain the ankle are at higher risk of avulsion fractures at the fifth metatarsal base because the peroneus brevis tendon inserts at this bony prominence and can pull a fragment away during inversion injury. If a person with a history of ankle sprains reports lateral foot pain after a twisting injury, a primary care physician or podiatrist should order foot and ankle X-rays to differentiate the injury.
Key Takeaway: Broken pinky toe symptoms often extend onto the outer edge of the foot toward the ankle, which means a plain X-ray of the entire foot (not just the toe) is needed to rule out a concurrent fifth metatarsal fracture.
Broken Little Toe Symptoms and What Makes Them Tricky
Broken little toe symptoms are similar to broken pinky toe symptoms because these refer to the same anatomical structure (the fifth digit), but the clinical challenge is that these fractures are frequently dismissed as sprains or “just a stubbed toe,” leading to delayed evaluation and occasional malunion.
The most common reason a broken little toe goes undiagnosed for days or weeks is that the person assumes the pain will resolve on its own, as it would with a simple soft tissue bruise. A non-displaced fracture of the fifth phalanx does feel somewhat better with rest, particularly after the first 48 to 72 hours when acute inflammation begins to subside. But the pain returns with any activity, and the toe may gradually heal in a misaligned position if weight-bearing resumes too early without appropriate buddy taping or splinting.
Clinically, the symptom that most reliably distinguishes a broken little toe from a severe sprain is point tenderness directly over the phalangeal shaft. Sprains produce tenderness at the joint line (the interphalangeal joint) and in the ligamentous structures, not along the bony shaft itself. A person can usually identify this distinction by pressing with one fingertip along different parts of the toe.
The National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIAMS) states that most non-displaced fractures of the lesser toes are treated with buddy taping to the adjacent toe, a stiff-soled shoe, and activity modification for four to six weeks. This conservative management works well, but only when the fracture is confirmed non-displaced by radiograph. A displaced fracture of the little toe that is mistakenly managed as a sprain can heal in an angulated position, causing chronic pain during shoe-wearing and altered gait mechanics.
Older adults who wear poorly fitting footwear are at higher risk of repeated minor fractures of the little toe. Cumulative damage can lead to a permanently deformed (mallet) toe if individual fractures are not appropriately managed.
Big Toe Fracture Symptoms: Why They’re More Serious
Big toe fracture symptoms are clinically more serious than fractures of the lesser toes because the hallux (great toe) bears approximately 40 to 50 percent of the total body weight during the propulsive phase of normal gait, making any disruption of its structural integrity directly affect walking mechanics.
The great toe has only two phalanges: the proximal phalanx (the longer, larger segment) and the distal phalanx (the tip segment). It lacks the middle phalanx present in toes two through five. Both segments can fracture, and fractures at the base of the proximal phalanx are particularly significant because this area includes the attachment of the plantar plate, the flexor hallucis brevis tendon, and the medial and lateral sesamoid bones.
Symptoms specific to a big toe fracture:
- Severe, immediate pain at the base, shaft, or tip of the great toe
- Rapid, pronounced swelling that extends across the ball of the foot
- Bruising that develops across the entire plantar forefoot and onto the dorsal foot
- Inability to bear weight or extreme pain during weight-bearing within the first hour
- Rigid, reduced range of motion at the metatarsophalangeal joint
- Visible angulation or deformity of the great toe (in displaced fractures)
The sesamoid bones embedded in the flexor hallucis brevis tendon beneath the first metatarsal head can also fracture, producing a symptom pattern that mimics but differs from a phalangeal fracture: pain is located at the ball of the foot rather than along the toe itself, and it is intensified by standing on tiptoe.
Gout attacks in the big toe joint produce swelling and extreme pain that can mimic a fracture symptom pattern. A history of gout, no trauma event, and fever alongside the toe pain points toward gout rather than fracture, though a primary care physician or podiatrist should evaluate and order imaging to confirm.
Fractured Big Toe Symptoms That Need Orthopedic Attention
Fractured big toe symptoms that warrant same-day orthopedic or podiatric evaluation include any visible deformity, any fracture affecting the metatarsophalangeal joint surface, and any fracture in a person with diabetes or peripheral vascular disease.
The American College of Foot and Ankle Surgeons recommends that all fractures of the proximal phalanx of the great toe be evaluated by a podiatrist or orthopedic surgeon within 24 hours of injury. This is because the alignment of the great toe directly determines the mechanical efficiency of the foot during walking and running. A fracture that heals in even mild malalignment can cause chronic pain, altered gait, and accelerated arthritis at the first metatarsophalangeal joint.
Specific symptoms indicating that the fracture needs orthopedic-level evaluation beyond standard urgent care:
- The great toe is visibly angled sideways or upward compared to its normal position
- The skin over the fracture site is blistered, darkened, or shows signs of pressure breakdown
- Pain is uncontrolled with basic elevation and ice after 2 to 4 hours
- There is numbness or tingling in the toe, suggesting nerve compression at the fracture site
- The toenail has a dark subungual hematoma (blood pooling under the nail), indicating a tuft fracture with possible nail bed injury
A subungual hematoma that occupies more than 50 percent of the nail bed area should be evaluated by a physician because it may indicate an open fracture of the distal phalanx even without visible skin disruption, according to clinical guidance from the American Academy of Orthopaedic Surgeons.
Runners who notice persistent pain at the base of the great toe after ramping up training mileage should have the possibility of a sesamoid stress fracture evaluated with MRI or a nuclear bone scan, because these small bones are invisible in their early fracture stages on plain radiographs.
Key Takeaway: Any fracture of the great toe requires evaluation by a podiatrist or orthopedic surgeon within 24 hours because the hallux bears nearly half of body weight during walking, and malalignment during healing directly compromises long-term gait mechanics.
How to Tell If a Toe Is Broken or Sprained
The most clinically reliable way to distinguish a broken toe from a sprained toe before imaging is to locate the point of maximum tenderness: pain that sits directly over the bone shaft points toward fracture, while pain centered at the joint line and in the surrounding soft tissue points toward sprain.
No self-assessment technique can definitively confirm a fracture or exclude one with clinical certainty. Only a plain radiograph can do that. However, because many people need to make an initial decision about urgency before imaging is available, the following step-by-step assessment can help guide that decision:
To assess whether a toe injury is more consistent with fracture or sprain:
- Wait 10 to 15 minutes after the injury for the immediate shock response to settle, then carefully examine the toe in good lighting.
- Look for visible deformity: if the toe is pointing in an abnormal direction, assume fracture and seek same-day evaluation. Do not attempt to straighten it.
- Gently press with one fingertip along the shaft of the bone between the joints. Severe, sharp, well-localized pain at the bone surface is the strongest clinical indicator of fracture.
- Press at the joint itself (the crease where the toe bends). If the worst pain is at the joint line rather than along the bone, a sprain is more likely though not confirmed.
- Attempt to gently flex and extend the toe through its natural range of motion. A fracture typically produces sharp pain through any movement; a sprain may allow some movement with moderate pain.
- Check whether the toe can bear any weight at all. Complete inability to bear weight on the forefoot suggests fracture, though this is not specific.
- If any of steps 1 through 6 suggest fracture, or if you are uncertain, seek radiographic evaluation. Do not delay if the person has diabetes, neuropathy, or is a child.
A 2018 study published in the Journal of the American Academy of Orthopaedic Surgeons confirmed that clinical examination alone without imaging misclassifies toe fractures as sprains in approximately 20 to 25 percent of cases. The only reliable method of confirmation is a three-view plain radiograph (anteroposterior, lateral, and oblique views of the affected toe).
Broken Toe Symptoms in Specific Populations
Broken toe symptoms can differ substantially from the typical presentation depending on the person’s underlying health status, and several populations are at risk of atypical presentations that delay diagnosis and worsen outcomes.
Diabetic peripheral neuropathy is the most clinically important modifier of broken toe symptoms. In people with diabetes who have developed neuropathy, the normal pain response mediated by the medial and lateral plantar nerve branches may be severely blunted or absent. A person with diabetic neuropathy can fracture a toe with minimal or no pain. The first symptom they notice may be swelling, skin redness, or warmth, without any memory of a traumatic event that caused it. This presentation pattern, sometimes called a Charcot fracture in its advanced form, requires immediate evaluation by a podiatrist or endocrinologist.
According to the Centers for Disease Control and Prevention, approximately 50 percent of people with diabetes develop some form of peripheral neuropathy during their lifetime, making painless or near-painless fractures a real and common clinical risk in this population.
People with osteoporosis fracture more easily and sometimes experience fractures without a clear traumatic event. An insufficiency fracture of the phalanx from normal walking produces a dull ache that may be attributed to arthritis or general foot pain for weeks before diagnosis.
Elderly adults may present with reduced swelling and less visible bruising despite significant fractures, because age-related reduction in skin elasticity, vascular responsiveness, and inflammatory cell mobility all dampen the typical visible symptom response.
Athletes using compression tape or athletic tape regularly may initially not notice swelling because the external pressure limits tissue expansion. Once the tape is removed, the swelling becomes visible and the pain intensifies.
Broken Toe Symptoms in Children: Growth Plate Risk
Broken toe symptoms in children are clinically distinct from adult presentations because a child’s phalangeal bones contain open physeal plates (growth plates), and fractures through or near these plates can disrupt the bone’s normal growth trajectory if not recognized and treated correctly.
The physeal plate, also called the epiphyseal plate, is a cartilaginous region near the ends of the long bones in growing children. It is structurally weaker than the surrounding bone. When a child’s toe is injured, the physeal plate can fracture (called a Salter-Harris fracture) in a pattern that can resemble a joint sprain on plain radiograph if not interpreted carefully.
A Salter-Harris Type I fracture (where the growth plate separates without any visible bone fragment) may be nearly invisible on standard X-rays. The primary clinical indicator in a child is point tenderness directly over the physeal plate region at the base of the toe, even when the radiograph appears normal. The American Academy of Pediatrics recommends that suspected growth plate injuries in children be managed as fractures even when imaging appears normal, based on clinical tenderness at the physeal region.
Symptoms that specifically warrant pediatric orthopedic evaluation after a toe injury:
- Point tenderness directly over the joint or physis in a child under 14 years
- Any visible angular deformity of the toe in a child
- A child who refuses to walk on the foot for more than 30 minutes after the injury
- Significant swelling at the base of the toe near the metatarsophalangeal joint
Boys between ages 8 and 14 and girls between ages 6 and 12 are at the highest risk of Salter-Harris fractures because this is the period of peak physeal plate activity. A primary care physician or pediatric emergency medicine physician should evaluate any toe fracture in a child in this age range, and a referral to a pediatric orthopedic surgeon is appropriate when growth plate involvement is suspected.
Key Takeaway: In children under 14, a toe injury with point tenderness at the bone’s growth plate area should be treated as a fracture even if the X-ray appears normal, because Salter-Harris fractures can be radiographically invisible in their early stages.
Broken Toe Complications and Warning Signs of Trouble
Broken toe complications are uncommon when fractures are diagnosed promptly and managed appropriately, but they do occur, and recognizing the warning signs of a complication early prevents significant long-term disability.
Malunion is the most common complication of a broken toe that heals in a malaligned position. This occurs when a displaced fracture is not properly reduced and stabilized, causing the bone to heal in an angulated or rotated position. The result is a permanent deformity of the toe, ongoing pain with shoe-wearing, and altered gait mechanics. The lesser toes are particularly prone to malunion when displaced fractures are managed as sprains.
Post-traumatic arthritis can develop after intraarticular fractures (fractures involving the joint surface). When the smooth cartilage of the metatarsophalangeal or interphalangeal joint is damaged by the fracture, the irregular joint surface leads to accelerated cartilage wear. The first metatarsophalangeal joint (the big toe joint) is most commonly affected. Symptoms of post-traumatic arthritis develop months to years after the original injury and include progressive, deep joint pain and stiffness, reduced joint range of motion, and swelling at the joint line.
Warning signs that a broken toe is developing a complication:
- Pain that worsens rather than gradually improves over 7 to 10 days of appropriate rest
- Increasing redness, warmth, or fever developing 2 to 5 days after the injury (may indicate infection, especially in open fractures)
- Numbness or persistent tingling in the toe (may indicate nerve compression)
- Skin that becomes pale, grey, or mottled and cold to the touch (may indicate vascular compromise)
- The toe gradually drifting into an abnormal angle over the first two weeks
Compartment syndrome of the foot is rare with isolated toe fractures but can occur after crush injuries involving multiple metatarsals and phalanges simultaneously. The pain of compartment syndrome is severe, constant, and unresponsive to elevation and rest. It is a surgical emergency.
Emergency Symptoms: When to Call 911 or Go to the ER
Certain symptoms associated with a broken toe or toe injury require immediate emergency evaluation. Do not wait to see if these resolve on their own.
Call 911 or go to the nearest emergency room immediately if you experience:
- Bone visibly protruding through the skin (open fracture), with or without active bleeding
- Severe, unrelenting pain in the foot that does not respond to elevation, ice, or over-the-counter pain relief, particularly after a crush injury (this can indicate compartment syndrome)
- The toe or forefoot becomes pale, grey, or blue-white and cold to the touch, or you lose sensation in the toe (signs of vascular or nerve compromise)
- Any toe injury in a person with diabetes who also has a wound, skin breakdown, or ulcer in the foot area
- A crush injury from a heavy object (machinery, vehicle, large fallen object) involving multiple toes or the forefoot
- Severe, uncontrolled bleeding from an open wound at the toe
- Signs of infection in the days following a toe injury: increasing redness spreading up the foot, red streaks, fever above 38°C (100.4°F), or pus from the wound
These presentations can indicate open fracture, vascular compromise, acute compartment syndrome, or diabetic foot emergency, all of which require emergency medical assessment, not an urgent care appointment or a phone call.
When to Go to the ER for a Broken Toe
The decision about where to go for a broken toe depends on the specific symptom pattern, the type of fracture suspected, and the person’s underlying health status.
The triage framework recommended by the American College of Foot and Ankle Surgeons broadly divides broken toe presentations into three urgency categories:
| Presentation | Appropriate Evaluation | Timeframe |
|---|---|---|
| Open fracture, vascular compromise, compartment syndrome signs | Emergency room | Immediately, call 911 |
| Visible deformity, angulation, complete inability to bear weight | Emergency room or orthopedic urgent care | Same day, within 2 to 4 hours |
| Big toe fracture (any type), fracture in person with diabetes or neuropathy | Podiatrist or orthopedic surgeon | Same day, within 24 hours |
| Suspected displaced fracture of lesser toe with severe pain | Urgent care with X-ray capability | Same day |
| Suspected non-displaced lesser toe fracture, moderate pain, no deformity | Urgent care or primary care | Within 24 to 48 hours |
| Mild pain, minimal swelling, no deformity, neurologically intact adult | Primary care physician | Within 48 to 72 hours |
Urgent care centers that do not have on-site X-ray capability cannot confirm a fracture diagnosis or assess for displacement. Before going to urgent care, call ahead to confirm they have X-ray services and the ability to interpret foot radiographs.
People with peripheral artery disease, blood clotting disorders, or immunocompromising conditions (including those taking immunosuppressant medications) should seek same-day evaluation for any toe fracture, even apparently minor ones, because their capacity to prevent infection and support healing is significantly impaired.
The key practical point: no toe fracture should go unevaluated for more than 72 hours in a neurologically intact adult, and any fracture in a person with diabetes, neuropathy, vascular disease, or a child requires same-day evaluation without exception.
Key Takeaway: A person with diabetes, peripheral neuropathy, or peripheral vascular disease should seek same-day podiatric or orthopedic evaluation for any foot or toe injury, even if the pain seems mild, because reduced sensation masks the true severity of the fracture.
Broken Toe Diagnosis and What to Expect at the Clinic
Broken toe diagnosis is confirmed by a three-view plain radiograph of the affected toe, and the clinical examination that accompanies imaging helps determine which fracture type is present, whether it is displaced, and what management is appropriate.
When a person arrives at an urgent care clinic, emergency room, or primary care office with a suspected toe fracture, the clinical assessment follows a standard sequence:
- The clinician takes a brief injury history: mechanism of injury, time of injury, whether there was an audible snap or pop, and whether the person has any relevant medical history (diabetes, osteoporosis, prior foot surgeries, anticoagulant medication use).
- Visual inspection assesses for visible deformity, angulation, skin integrity, nail bed status, and color of the toe and surrounding skin.
- Palpation identifies point tenderness along the phalangeal shaft and at the joint lines, and assesses capillary refill time and skin temperature to evaluate vascular status.
- Neurological assessment checks sensation in the toe using light touch, confirming that the digital nerve branches are intact.
- Plain radiographs in three views (anteroposterior, lateral, and oblique) are ordered. In most non-displaced fractures, these views confirm the diagnosis and fracture location definitively.
- If a stress fracture is suspected and plain radiographs appear normal, the clinician may order MRI of the foot, which can detect stress fractures within days of onset versus the 2 to 3 weeks required before plain radiograph changes appear.
- CT scan is reserved for complex intraarticular fractures where the exact orientation of fracture fragments affects surgical planning.
The diagnosis of a non-displaced phalangeal fracture typically takes 15 to 30 minutes from arrival to confirmed imaging. The treatment decision, whether buddy taping alone, a hard-soled shoe, a walking boot, or surgical fixation, depends entirely on the fracture type, displacement status, and the individual patient’s anatomy and health history.
A person should tell their treating clinician:
- All medications they take, including blood thinners, corticosteroids, and NSAIDs
- Any history of diabetes, peripheral neuropathy, or vascular disease
- Whether this is the same foot that has been previously injured or operated on
- Any recent increase in physical activity that might point toward stress fracture
- Whether the toenail is darkened under the surface, which indicates a subungual hematoma requiring evaluation for distal phalanx fracture
Frequently Asked Questions About Broken Toe Symptoms
What are the first signs of a broken toe?
The first signs of a broken toe are immediate, sharp pain at the site of injury and rapid swelling beginning within 15 to 30 minutes.
Point tenderness directly over the bone, rather than at the joint line or in surrounding soft tissue, is the most clinically reliable early indicator of fracture.
Bruising typically develops over the following 12 to 24 hours and may spread to adjacent toes through the interconnected digital venous plexus.
Can you have a broken toe with no bruising?
A broken toe can absolutely be present without visible bruising, particularly in the first 12 to 24 hours after injury, in stress fractures, or in people with reduced peripheral circulation.
Stress fractures of the phalanges frequently produce pain and swelling with little or no bruising because the bone fails gradually rather than through a single traumatic event with vessel rupture.
People who take corticosteroid medications long-term may also show minimal bruising despite significant fracture, because corticosteroids reduce capillary fragility and inflammatory response.
How do you know if you broke your big toe or just sprained it?
Point tenderness directly over the shaft of the proximal or distal phalanx of the big toe (rather than at the joint line) is the strongest clinical indicator of fracture rather than sprain.
Severe swelling that extends across the entire ball of the foot, inability to bear any weight on the forefoot, and visible angulation of the great toe all point toward fracture.
Only a plain radiograph in three views can confirm the distinction with certainty, which is why any suspected big toe injury warrants evaluation by a podiatrist or orthopedic surgeon within 24 hours.
What does a broken pinky toe feel like?
A broken pinky toe typically feels like sharp, immediate pain along the outer edge of the foot and the small toe, with rapid swelling that extends toward the outer ankle.
The pain is specifically worsened by any pressure on the lateral foot, including wearing a closed-toe shoe, and walking causes a characteristic limp where the person avoids loading the outer foot.
Because the fifth metatarsal base (a different bone) also produces very similar pain with certain fracture patterns, a plain X-ray of the foot including the base of the fifth metatarsal is needed to confirm which bone is injured.
Should I go to the ER or urgent care for a broken toe?
The answer depends on the specific symptoms: visible bone, suspected vascular compromise, compartment syndrome signs, or crush injury require the emergency room immediately.
A visible deformity or angulation of any toe, any fracture in a person with diabetes or neuropathy, or an injury to the big toe warrants same-day evaluation at an urgent care with X-ray capability or an orthopedic walk-in clinic.
A suspected non-displaced lesser toe fracture with moderate pain, no deformity, and no complicating health conditions in an otherwise healthy adult can be evaluated at urgent care within 24 to 48 hours.
How long does a broken toe take to heal?
Non-displaced fractures of the lesser toes typically heal in four to six weeks with buddy taping, a stiff-soled shoe, and activity modification.
Fractures of the big toe, displaced fractures, or intraarticular fractures take six to eight weeks or longer, with more structured immobilization and follow-up imaging to confirm healing alignment.
People with osteoporosis, diabetes, or peripheral vascular disease have slower bone healing timelines, and the treating podiatrist or orthopedic surgeon will advise on individual recovery expectations based on imaging and clinical follow-up.
Recognizing the specific symptom pattern of a broken toe, from the exact quality of the bone-level pain to the spread of bruising and swelling through the digital venous plexus, gives you the clinical framework to make a better-informed decision about urgency. The difference between going to the ER tonight and waiting for urgent care in the morning is not arbitrary; it depends on specific anatomical findings: visible deformity, vascular status, your medical history, and which toe is involved.
If you have diabetes, peripheral neuropathy, or peripheral vascular disease, treat any foot injury as a same-day medical event regardless of pain level. Your nervous system may not be giving you accurate pain signals, and a missed fracture in a compromised foot can escalate quickly. For everyone else, the rule is straightforward: visible deformity, open wounds, or uncontrolled pain mean the emergency room. Any other suspected fracture means X-ray confirmation within 24 to 48 hours from a primary care physician, urgent care with imaging, podiatrist, or orthopedic surgeon.
The clinical information in this article tells you what to look for and what it means. What happens next depends on your specific injury, your health history, and the provider who examines and images your foot.