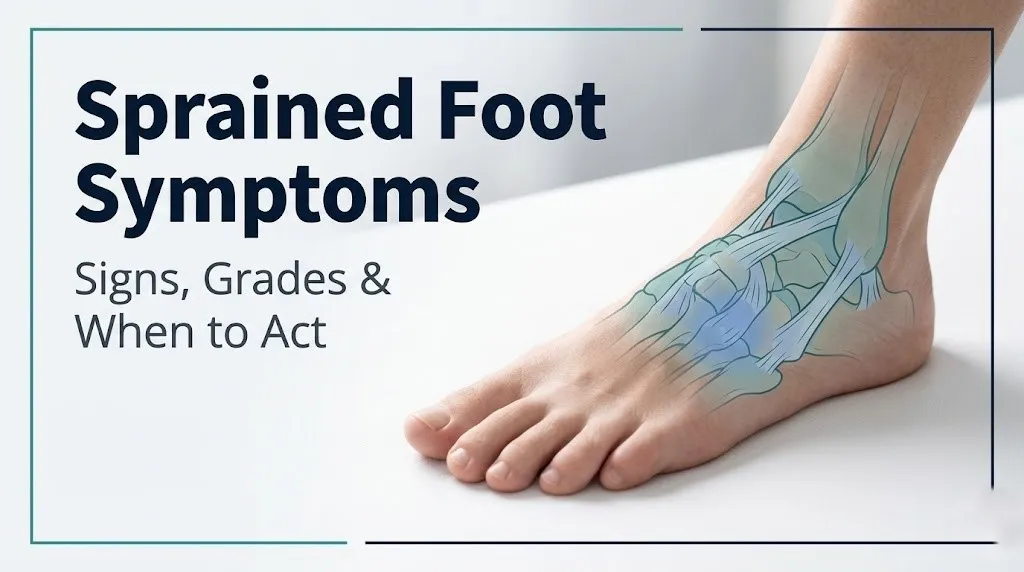
Sprained Foot Symptoms: Signs, Grades & When to Act
Sprained foot symptoms include localized pain, swelling, bruising, tenderness to touch, and difficulty bearing weight, but the specific pattern and severity depend on which ligaments are injured and how severely the collagen fibers have been disrupted. Recognizing the difference between a mild sprain you can manage at home and a serious ligament tear or hidden fracture requires understanding what each symptom actually means, not just that it hurts.
According to the National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIAMS), foot and ankle sprains are among the most common musculoskeletal injuries in the United States, accounting for an estimated 25,000 emergency department visits per day across all sprain types. The foot contains 26 bones connected by more than 30 joints, each stabilized by a complex network of ligaments, making the symptom picture more anatomically nuanced than most online resources acknowledge.
This article covers every recognized symptom of a sprained foot with the physiological reason each one occurs, how symptoms differ by injury grade and anatomical location, which presentations are self-manageable and which require same-day professional evaluation, and how symptom patterns differ by age, athletic status, and underlying health conditions.
Sprained Foot Symptoms: What Is Actually Happening Inside Your Foot
Sprained foot symptoms are produced by a specific cascade of tissue-level events triggered when ligament fibers are stretched beyond their mechanical limit or torn.
When a ligament is overstressed, collagen fibers within the ligament structure micro-tear or rupture completely. This mechanical disruption immediately activates nociceptors (pain-sensing nerve endings) embedded throughout the ligament tissue, producing the sharp or aching pain that is typically the first symptom a person notices.
Within minutes, damaged tissue cells release a cascade of inflammatory mediators. Histamine from local mast cells and bradykinin from plasma proteins cause nearby blood vessels to dilate and become more permeable. Plasma fluid leaks through capillary walls into the surrounding tissue, producing the swelling that follows injury. Prostaglandin E2, produced via activation of the cyclooxygenase-2 (COX-2) enzyme pathway, amplifies both pain sensitivity and vascular permeability, which is why foot swelling and pain tend to worsen over the first 24 to 48 hours rather than being worst at the moment of injury.
Think of a ligament like a bundle of braided rope connecting two bones across a joint. When you twist the foot past its normal range of motion, some of those rope strands snap. The body responds to a snapped rope the same way it responds to any tissue injury: it floods the area with chemical signals to protect the site, stiffen movement, and start repair. Every symptom you experience is the body running that protective program.
Disrupted mechanoreceptors within the torn ligament also produce a proprioceptive deficit, which is why a sprained foot often feels unstable or unreliable during weight-bearing, even when the pain level is moderate. This instability is not imagined; it reflects genuine loss of real-time joint position feedback from the injured ligament.
Key symptoms produced by this cascade:
- Immediate sharp or burning pain at the injury site (nociceptor activation)
- Progressive swelling over 12 to 48 hours (histamine/bradykinin-mediated vascular permeability)
- Bruising appearing 24 to 72 hours after injury (red blood cell extravasation through damaged capillaries)
- Warmth and redness over the injured area (increased local blood flow via vasodilation)
- Joint instability during weight-bearing (proprioceptive mechanoreceptor disruption)
What Is a Sprained Foot
A sprained foot is an injury to one or more of the ligaments connecting the bones of the foot, caused by the foot being forced into a position beyond its normal range of motion.
The foot contains several distinct ligament complexes, each serving a different biomechanical function. The Lisfranc ligament complex spans the midfoot, connecting the medial cuneiform to the second metatarsal base via dorsal, interosseous, and plantar bands. The plantar fascia runs along the sole from the calcaneus to the metatarsal heads, providing arch support. The spring ligament (plantar calcaneonavicular ligament) connects the calcaneus to the navicular and supports the medial longitudinal arch. The anterior talofibular ligament and calcaneofibular ligament, while technically ankle ligaments, attach near enough to the lateral foot that lateral foot sprains often involve these structures too.
A sprain differs from a strain: a sprain injures a ligament (bone-to-bone connective tissue), while a strain injures a muscle or tendon (muscle-to-bone connective tissue). A sprain also differs from a fracture, though the two can and do occur simultaneously, which is why clinical evaluation matters more than self-diagnosis.
According to the American Academy of Orthopaedic Surgeons (AAOS), most foot sprains result from sports activity, missteps on uneven surfaces, falling, or sudden directional changes that force the foot into inversion (turning inward), eversion (turning outward), or plantarflexion (pointing down under load).
Quick Tip:
- The most common foot sprain mechanism is inversion: the foot rolls inward, putting maximum stress on the lateral ligament structures
- Midfoot sprains from high-energy impacts or axial loading are less common but far more serious
- A sprain and a fracture can look nearly identical on physical exam alone, which is why imaging is sometimes the only way to confirm the diagnosis
Symptoms of a Sprained Foot: The Complete Clinical Picture
The core symptoms of a sprained foot are pain, swelling, bruising, localized tenderness, reduced range of motion, and difficulty bearing weight, though the intensity and combination of these symptoms depend on which ligaments are involved and how severely.
Pain is typically the first and most immediate symptom. In Grade I sprains, the pain is mild and aching, localized to the site of ligament stress. In Grade II and III injuries, the pain can be severe, radiating across the forefoot or arch, and made dramatically worse by any attempt to move or load the foot.
Swelling follows pain within minutes to hours. The dorsal (top) surface of the foot is where fluid accumulates most visibly because the skin there is thin and the underlying anatomy has relatively little subcutaneous fat to buffer the edema. In midfoot sprains, swelling can span the entire middle portion of the foot, from the navicular across to the cuboid.
Tenderness to palpation is one of the most diagnostically useful physical findings. A clinician pressing directly over the injured ligament will reproduce sharp, localized pain at that exact point. Diffuse tenderness across the entire foot is more typical of severe Grade III sprains or fractures.
| Symptom | Physiological Mechanism | Clinical Significance |
|---|---|---|
| Localized pain | Nociceptor activation in torn collagen fibers | Indicates site of primary injury |
| Swelling (edema) | Histamine/bradykinin-mediated vascular permeability; plasma extravasation | Peaks at 24-48 hours; worsens with dependency |
| Bruising (ecchymosis) | Red blood cell extravasation through damaged capillaries | May appear 24-72 hours after injury; can track distally |
| Tenderness to touch | Ongoing nociceptor sensitization (peripheral sensitization) | Most reliable physical sign for locating injured ligament |
| Reduced range of motion | Protective muscle spasm; joint effusion limiting movement | Guards against further ligament stress |
| Instability or “giving way” | Mechanoreceptor disruption; proprioceptive deficit | Indicates structural ligament compromise |
| Warmth over the injury site | Local vasodilation; increased blood flow | Normal acute inflammatory response |
For older adults with reduced pain sensitivity or people with diabetic peripheral neuropathy, some of these symptoms (particularly pain) may be significantly muted despite a serious injury. This population requires evaluation even when pain levels seem low.
Foot Sprain Symptoms by Grade: Grade I, II, and III
Foot sprain symptoms are classified into three grades based on the extent of ligament fiber disruption, and each grade produces a meaningfully different clinical picture.
Grade I represents a mild stretch injury with microscopic tearing of some collagen fibers. The ligament remains structurally intact. Symptoms are mild localized pain and minimal swelling with little to no bruising. Weight-bearing is painful but possible. The joint retains its mechanical stability.
Grade II represents a partial tear of the ligament. A significant portion of the collagen fibers are disrupted but some continuity remains. Symptoms include moderate to severe pain, noticeable swelling within the first few hours, bruising that often becomes visible by the next day, and clear difficulty walking. The joint may feel mildly unstable or unreliable. A research article published in the British Journal of Sports Medicine noted that Grade II sprains account for the majority of clinically evaluated ligament injuries and typically require structured rehabilitation to prevent chronic instability.
Grade III represents a complete ligament rupture. All collagen fibers across the ligament are torn. Paradoxically, some Grade III injuries initially feel less painful than Grade II because the nerve endings within the ligament are also disrupted. The hallmarks are severe, rapid swelling, inability to bear weight, visible deformity or abnormal foot position, and significant instability on any attempted movement. This grade requires professional evaluation to rule out associated fractures and assess joint stability.
| Grade | Fiber Damage | Pain Level | Swelling | Bruising | Weight-Bearing |
|---|---|---|---|---|---|
| Grade I | Microscopic tears; ligament intact | Mild, localized | Minimal | Rare or none | Painful but possible |
| Grade II | Partial tear; ligament partially intact | Moderate to severe | Moderate, visible | Common; appears within 24-48 hours | Difficult; limping |
| Grade III | Complete rupture | Severe or paradoxically reduced | Rapid, severe | Extensive; may track beyond foot | Not possible without significant pain |
Children’s growth plates complicate this grading system. In a child’s foot, the ligament is often stronger than the adjacent growth plate (physis), so a force that would produce a Grade II sprain in an adult may instead produce a Salter-Harris fracture in a child. Pain and swelling in a child’s foot after injury always warrants evaluation by a primary care physician or pediatric orthopedic surgeon, regardless of the apparent grade.
Key Takeaway: Grade III foot sprains can feel surprisingly less painful than Grade II injuries because the ligament’s own nerve fibers are fully disrupted. Severe swelling and inability to bear weight are more reliable severity indicators than pain intensity alone.
Top of Foot Sprain Symptoms
A top of foot sprain produces pain, swelling, and tenderness specifically along the dorsal (upper) surface of the foot, in the region spanning from the base of the toes back toward the ankle.
The dorsal surface of the foot is crossed by the extensor digitorum longus tendons and extensor hallucis longus tendon, along with a network of smaller dorsal ligaments connecting the metatarsals to the tarsal bones. When these structures are sprained by compression, hyperextension, or a direct impact to the top of the foot, the symptoms concentrate on the dorsum rather than the sole or lateral edge.
Swelling on the top of the foot is often dramatic in appearance because the skin there is thin and flexible. Even a moderate amount of fluid accumulation beneath the skin produces visible puffiness that can make the foot look almost domed. This visual severity does not always match injury severity; a Grade I dorsal sprain can look very swollen while a Grade II midfoot injury may show less obvious surface change.
Tenderness when pressing on specific bones or along the dorsal ligament lines is the key physical finding that distinguishes a true top-of-foot sprain from referred pain originating in the ankle. If pressing directly on a metatarsal shaft reproduces the pain, that raises concern for a stress fracture rather than a ligament injury. Research from the American Journal of Sports Medicine has shown that stress fractures of the second and third metatarsals can present identically to dorsal sprains on initial examination, making imaging important when point-tenderness over a bone is present.
Pain with toe extension (pulling the toes upward) is a characteristic feature of dorsal sprain because that movement stretches the damaged extensor mechanism and the dorsal ligaments simultaneously. Pain with toe flexion (curling the toes downward) more typically indicates a plantar or intrinsic muscle injury.
People who wear tight shoes or foot gear that compresses the dorsum (cyclists, athletes in cleats, skiers) are at elevated risk for dorsal ligament stress injuries. In these cases, a footwear assessment is a practical first step alongside the injury evaluation.
Midfoot Sprain Symptoms and Lisfranc Injury
Midfoot sprain symptoms include pain across the central portion of the foot, swelling that spans from the navicular and cuboid bones to the metatarsal bases, and severe difficulty bearing weight, particularly the forefoot push-off phase of walking.
The midfoot is stabilized primarily by the Lisfranc ligament complex, which anchors the medial cuneiform to the base of the second metatarsal. This anatomical arrangement is the most critical stabilizing junction in the midfoot. When the tarsometatarsal joints (the articulations between tarsal bones and metatarsal bases) are subjected to axial compression combined with rotation, the Lisfranc ligament and its adjacent structures can be partially or completely torn.
A Lisfranc sprain is not the same as a garden-variety midfoot sprain. According to a study published in the Journal of Bone and Joint Surgery, Lisfranc injuries are frequently misdiagnosed as simple sprains on first presentation, particularly when imaging is not obtained in weight-bearing position. The clinical consequence of a missed Lisfranc injury is post-traumatic arthritis of the tarsometatarsal joint and permanent arch collapse if the structural disruption is not identified and managed.
A key clinical test is the “piano key test”: loading each metatarsal head vertically while the foot is stabilized. Pain at the tarsometatarsal joint line during this test is a reliable indicator of Lisfranc complex involvement.
Observable symptoms that distinguish a Lisfranc sprain from a routine midfoot sprain:
- Plantar (sole-side) bruising appearing within the first 24 hours, particularly over the arch, is nearly pathognomonic for Lisfranc injury
- Inability to bear weight on the forefoot or push off with the toes
- Visible widening between the first and second metatarsal bases on a weight-bearing X-ray
- Pain localized to the Lisfranc joint line (at the base of the second metatarsal) rather than diffusely across the midfoot
Any suspicion of Lisfranc injury warrants same-day referral to a board-certified orthopedic surgeon or sports medicine physician. Delayed diagnosis is the primary reason for poor long-term outcomes in this injury.
Sprained Foot Swelling Explained
Swelling is one of the earliest and most visible sprained foot symptoms, and it develops through a well-understood physiological sequence that begins within minutes of injury.
The immediate trigger is mechanical disruption of ligament collagen fibers. Torn cells release damage signals that activate nearby mast cells, which degranulate and release histamine. Histamine acts on local capillary endothelial cells, causing them to widen the gaps between cells (paracellular permeability), allowing plasma fluid to leak from the bloodstream into the surrounding soft tissue. Bradykinin amplifies this permeability effect and also directly stimulates nociceptors, adding to pain at the same time as swelling builds.
The result is edema: an accumulation of protein-rich fluid in the interstitial space surrounding the injured ligament. On the top of the foot, where the skin is thin and loosely attached to the underlying structures, this fluid is immediately visible as puffiness. On the plantar surface, where thick skin and dense connective tissue overlay the structures, swelling is felt as tightness or pressure more than seen as external puffiness.
Swelling typically peaks between 24 and 72 hours after injury, not at the moment of injury. This is because the inflammatory cascade takes time to fully activate, and because fluid continues to accumulate as long as the inflammatory mediators remain active. Swelling that is rapidly worsening after 72 hours, rather than plateauing, suggests either re-injury, a more severe injury than initially apparent, or an associated fracture with active bleeding.
According to the NIAMS, elevation of the injured foot above heart level reduces edema by using gravity to counteract the pressure driving fluid into the tissue. This is the physiological basis for the elevation component of the standard management protocol.
People with pre-existing conditions affecting fluid balance, including heart failure, chronic venous insufficiency, or kidney disease, may develop disproportionately severe swelling from a relatively minor sprain because their baseline fluid regulation is already compromised. For these individuals, a physician evaluation is appropriate even for apparent Grade I injuries.
Key Takeaway: Foot swelling that is worst 24 to 48 hours after injury is normal inflammatory physiology; swelling that continues to increase beyond 72 hours suggests a more serious injury and warrants evaluation by a primary care physician or orthopedic surgeon.
Sprained Foot Bruising and Discoloration
Bruising after a foot sprain appears when blood escapes from damaged capillaries into the surrounding soft tissue, and its location and timing carry meaningful clinical information.
When a ligament tears, small capillaries within and around the ligament are also disrupted. Red blood cells leak through the vessel walls and disperse into the surrounding tissue, producing the blue-black or purple discoloration known as ecchymosis. Because blood is a fluid, it follows fascial planes and gravitational gradients, which explains why bruising often appears some distance from the actual injury site.
Bruising from a foot sprain typically appears 24 to 72 hours after the injury. The delay is not a sign that the injury is minor; it simply reflects the time required for enough extravasated blood to accumulate and migrate close enough to the skin surface to be visible. An injury that produces immediate bruising (at the moment of injury or within the first hour) typically reflects more significant vessel damage or a fracture involving periosteal hematoma formation.
The pattern of bruising provides clinical information. Bruising that appears on the plantar surface of the foot, particularly along the arch, within the first 24 hours is strongly associated with Lisfranc ligament complex injury, as noted in clinical observation reported by the American College of Sports Medicine. Bruising that tracks down from the lateral ankle to the outer border of the foot is more typical of lateral ankle ligament sprains with extension into the lateral foot structures.
Bruising that extends to the toes, spreads across the sole, or appears rapidly (within hours) in an elderly person is more consistent with a fracture than a pure soft tissue sprain, because bones carry a richer blood supply and a fracture hematoma dissects through tissue more aggressively.
People taking anticoagulant medications (such as warfarin, rivaroxaban, or apixaban) will develop more extensive bruising from the same injury than people not on these medications, because their coagulation cascade cannot arrest the capillary bleeding as efficiently. For this population, bruising alone should not be used as a severity indicator.
Foot Sprain Pain When Walking or Bearing Weight
The character and location of pain during weight-bearing is one of the most diagnostically useful aspects of sprained foot symptoms, and it directly determines whether clinical evaluation is needed urgently.
When weight is placed on a sprained foot, the mechanical load compresses and stresses the injured ligament. Nociceptors within the damaged collagen fibers fire pain signals along sensory nerve fibers to the spinal cord and up to the brain’s somatosensory cortex, producing a sharp or aching pain at the injury site. Secondary to this, substance P (a neuropeptide released from nociceptive nerve terminals) amplifies local inflammation, making the pain response progressively more sensitive over the first 24 to 48 hours.
In Grade I sprains, walking is painful but possible. The foot accepts weight, and the gait pattern may be altered (limping) but not completely eliminated. In Grade II sprains, walking is moderately to severely painful and most people reduce their weight-bearing significantly, shortening their stride and avoiding push-off on the affected side. In Grade III sprains, full weight-bearing is typically not possible due to both pain and joint instability.
The Ottawa Foot Rules, validated in multiple prospective clinical studies and now standard in emergency medicine, provide a reliable clinical decision tool for determining when foot pain after injury warrants an X-ray. According to published validation studies, the Ottawa Foot Rules indicate radiographic imaging is needed if the patient has:
- Pain in the midfoot zone (from the navicular to the base of the fifth metatarsal)
- Plus any one of the following: bone tenderness at the navicular, bone tenderness at the base of the fifth metatarsal, or inability to bear weight (take 4 steps) immediately after injury and in the clinical setting
These rules have a sensitivity of approximately 97% for detecting clinically relevant fractures, making them the standard for deciding between imaging and observation in emergency and primary care settings.
Pain that is worst at the very start of walking (start-up pain) and eases slightly with movement, then worsens again after prolonged walking, is a pattern more often associated with stress fractures than acute ligament sprains. For athletic patients, particularly runners, this distinction matters significantly.
Sprained Foot vs. Broken Foot Symptoms
Distinguishing a sprained foot from a broken foot is one of the most common clinical challenges after a foot injury, and the overlap in symptoms is extensive enough that physical examination alone is often insufficient.
Both injuries produce pain, swelling, bruising, and difficulty bearing weight. The key differentiating features are not the presence of these symptoms but their specific character, location, and timing.
Point tenderness directly over bone (pressing on the shaft or base of a metatarsal and reproducing the exact pain) is a stronger indicator of fracture than ligament sprain. Ligament tenderness is located over the joint line between bones, not over the bone itself.
Visible deformity, including an obvious bend, angulation, or unnatural position of any part of the foot, is always a fracture indicator. No ligament sprain produces visible bone deformity.
Audible snap at the time of injury is more often reported with fractures, particularly avulsion fractures (where a ligament pulls a fragment of bone away from its attachment) and fifth metatarsal base fractures, which are among the most frequently missed foot injuries.
| Feature | Sprained Foot | Broken Foot (Fracture) |
|---|---|---|
| Pain location | Over joint line, between bones | Directly over bone shaft or bony prominence |
| Audible sound at injury | Pop or snap (some Grade III sprains) | Crack or snap (more common) |
| Deformity | None | May be visible angulation or displacement |
| Bruising timing | 24-72 hours after injury | Can appear within hours (periosteal hematoma) |
| Weight-bearing | Possible in Grade I; limited in Grade II | Often not possible; depends on fracture type |
| Response to Ottawa Foot Rules | Negative criteria: observation reasonable | Positive criteria: X-ray required |
According to research published in the American Journal of Sports Medicine, up to 20% of apparent ankle or foot sprains in an athletic population involve associated avulsion fractures, most commonly at the base of the fifth metatarsal or the navicular. This percentage underscores why imaging is not an overcautious choice for moderate or severe presentations.
Key Takeaway: Point tenderness directly on a bone (not over a joint line), visible deformity, or rapid-onset bruising after a foot injury are fracture indicators that warrant same-day X-ray evaluation, regardless of whether the injury initially felt like a sprain.
Early vs. Late-Stage Sprained Foot Symptoms
The symptom picture of a sprained foot changes significantly over the first 72 hours and then over the first two to six weeks, and understanding this timeline helps distinguish normal healing from a complication or missed diagnosis.
In the first 0 to 6 hours, the primary symptoms are pain (immediate, at the moment of injury) and rapidly developing swelling. The inflammatory mediator cascade is in full activation. Bruising is typically not yet visible because the extravasated blood has not had time to migrate to the skin surface. The injured area is warm to touch and tender. If the injury is severe enough, weight-bearing is not possible.
Between 24 and 72 hours, swelling reaches its peak. Bruising becomes visible, often spreading beyond the original injury site. Pain may actually intensify during this window because of peripheral sensitization: the ongoing action of prostaglandin E2 lowers the firing threshold of nociceptors, so stimuli that wouldn’t normally be painful (light touch, gentle movement) become uncomfortable. Range of motion is at its most restricted during this phase.
Between 3 and 14 days, if the injury is managed appropriately, swelling should begin to decrease. Bruising changes color from purple-blue to yellow-green as hemoglobin breaks down into biliverdin and then bilirubin. Pain with weight-bearing should be gradually improving. For Grade I sprains, significant functional recovery is expected within 1 to 2 weeks.
Beyond 2 to 6 weeks, persistent symptoms that are not improving suggest either a more severe injury than initially classified, an associated fracture that was not imaged, or the development of complications such as chronic lateral instability or post-traumatic synovitis of a tarsal joint. A 2022 review in the British Journal of Sports Medicine noted that approximately 30% of ankle and foot sprain patients who are not appropriately rehabilitated develop residual symptoms lasting beyond 3 months.
Chronic Foot Sprain Symptoms
Chronic foot sprain symptoms develop when an acute sprain does not heal fully, when mechanical instability persists after initial injury, or when repeated sprain episodes cause cumulative ligament damage.
The hallmark of chronicity is functional instability: the foot feels unreliable during dynamic activity, particularly on uneven ground, during cutting or lateral movements in sport, or even during ordinary walking on an incline. This instability reflects ongoing disruption of the mechanoreceptors within the ligament tissue that provide real-time proprioceptive feedback to the central nervous system. Even if the ligament has scar-healed structurally, the proprioceptive receptor population may not fully regenerate, leaving the joint functionally compromised.
Chronic symptoms differ from acute sprain symptoms in their character:
- A dull aching or persistent soreness rather than sharp acute pain
- Swelling that recurs with activity and resolves with rest (recurrent activity-related edema)
- Stiffness, particularly in the morning or after periods of inactivity, as scar tissue within the healing ligament is less flexible than normal collagen
- A repeated sensation of “giving way” during activity even without a discrete re-injury event
- Tenderness that persists over the original injury site for more than 6 weeks after the initial event
People with chronic foot sprain symptoms that persist beyond 6 to 8 weeks despite structured rest and rehabilitation should be evaluated by a sports medicine physician or board-certified orthopedic surgeon. MRI is typically the imaging modality of choice at this stage, as it can visualize ligament integrity, scar tissue formation, joint effusion, and any associated cartilage damage that plain X-rays will not show.
Athletes who repeatedly sprain the same foot without allowing adequate healing time between injuries are at particular risk for mechanical instability, in which the ligament has become structurally elongated and unable to provide its normal joint-restraint function even when pain has resolved.
Key Takeaway: Chronic foot instability, recurring swelling with activity, and persistent soreness beyond 6 to 8 weeks after a foot sprain are not normal healing; they indicate incomplete recovery and the need for evaluation by a sports medicine physician or orthopedic surgeon.
Sprained Foot Symptoms in Athletes
Athletes present with sprained foot symptoms that can be systematically more difficult to assess because of elevated pain tolerance, pressure to return to activity, and higher pre-existing ligament laxity from repetitive training stress.
High-level athletes commonly have a higher baseline pain threshold than sedentary adults due to endogenous opioid system conditioning from regular training. This means an athlete with a Grade II sprain may describe their pain as “mild” or “manageable,” leading to underestimation of injury severity during self-assessment. Clinical evaluation, not pain self-report alone, should guide grading in athletic patients.
Athletes who participate in sports requiring lateral cutting movements (basketball, soccer, tennis), running on uneven surfaces (trail running, football), or repeated foot loading (gymnastics, ballet) are at elevated risk for Lisfranc ligament stress injuries from repetitive axial loading, rather than a single acute traumatic event. These injuries present with insidious onset of midfoot pain, tenderness localized to the tarsometatarsal joint line, and symptoms that are initially mild but progressively worsen with continued activity.
Research published in the American Journal of Sports Medicine has shown that female athletes have statistically higher rates of ligamentous laxity due to the influence of estrogen and relaxin on collagen fiber cross-linking, making them more susceptible to repeat sprains after an initial foot injury. This hormonal effect is most pronounced during the mid-cycle follicular phase, when estrogen levels peak.
For athletes, the symptom evaluation should specifically include:
- Assessment of weight-bearing capacity using the Ottawa Foot Rules criteria
- Testing of the tarsometatarsal joint line for Lisfranc tenderness (piano key test)
- Evaluation of proprioceptive function (single-leg balance on the injured foot vs. the uninjured foot)
- History of prior sprains to the same foot and whether prior injuries were fully rehabilitated
An athlete who cannot perform a single-leg heel raise on the injured foot without significant pain has a functional deficit that warrants formal evaluation by a sports medicine physician before any return to training is considered.
Sprained Foot Symptoms in Older Adults and Children
Sprained foot symptoms present differently in older adults and children for distinct anatomical and physiological reasons, and both groups carry diagnostic risks that are not present in healthy adults of working age.
In older adults, the primary differences stem from reduced collagen elasticity and slower inflammatory response. Ligaments in older adults are stiffer and less able to absorb mechanical load before tearing, meaning even a low-energy mechanism (stepping off a curb, tripping on carpet) can produce a Grade II or III sprain. At the same time, the inflammatory response is blunted in aging tissue, so swelling and pain may be less dramatic than expected for the injury severity. Older adults with osteoporosis face a compounded risk: a force that would produce a ligament sprain in a younger adult may produce an associated fracture in bone with reduced mineral density.
Older adults taking anticoagulants, NSAIDs for chronic conditions, or corticosteroids will have altered symptom presentation: more bruising (anticoagulants), reduced swelling and pain signal (NSAIDs and corticosteroids), and slower tissue healing (corticosteroids). A physician evaluation is appropriate for any foot injury in an older adult, regardless of apparent symptom severity.
In children, the critical anatomical consideration is the growth plate (physis): cartilaginous zones at the ends of growing bones that are structurally weaker than the adjacent ligaments. Because a child’s ligaments are relatively stronger than their growth plates, the same inversion or twisting force that causes a lateral ligament sprain in an adult may instead produce a Salter-Harris fracture through the physis in a child. The external symptoms (pain, swelling, bruising) can be identical between these two injury types, making clinical differentiation impossible without imaging.
The AAOS recommends that all significant foot and ankle injuries in skeletally immature patients be evaluated with X-rays to rule out growth plate injury, regardless of the apparent clinical presentation.
For children, additional observable signs suggesting more than a minor sprain include:
- Refusal to bear any weight for more than a few minutes after injury
- Point tenderness over a bony growth plate rather than a joint line
- Significant swelling in a child who is not crying or reporting severe pain (which may indicate numbness from growth plate injury, not mild injury)
Emergency Symptoms: When to Call 911 or Go to the ER
Certain symptoms associated with a foot injury require immediate emergency evaluation. Do not wait to see if these resolve on their own.
Call 911 or go to the nearest emergency room immediately if you experience:
- Visible deformity of the foot, including bones appearing out of alignment or the foot sitting at an abnormal angle, which indicates a fracture-dislocation requiring emergency orthopedic management
- An open wound (skin broken) over the injured foot, particularly if bone is visible through the wound, which carries immediate infection risk and requires surgical evaluation
- Complete numbness or loss of sensation in the foot or toes after injury, indicating possible nerve or vascular damage requiring urgent assessment
- Absent or markedly reduced pulse in the foot (if the foot feels cold, looks pale or bluish, or lacks normal sensation), indicating possible arterial injury
- Inability to bear any weight combined with suspected high-energy injury mechanism (motor vehicle accident, fall from height, crush injury), where fracture-dislocation is the primary concern rather than isolated ligament sprain
- A suspected Lisfranc injury with rapid, severe midfoot swelling and inability to bear any forefoot weight, because delayed diagnosis of this injury leads to permanent structural damage and post-traumatic arthritis
These presentations can indicate fracture-dislocation, arterial injury, or compound fracture, and they require emergency medical assessment, not an urgent care appointment or a phone call.
When to See a Doctor for a Sprained Foot
Knowing when a foot sprain requires professional evaluation rather than home management is the practical decision that this entire symptom picture ultimately leads to.
The Ottawa Foot Rules provide the clearest evidence-based threshold: if you have pain in the midfoot zone and cannot bear weight (take 4 steps) immediately after the injury and again in the clinical setting, or if you have bone tenderness at the navicular or the base of the fifth metatarsal, an X-ray is indicated. These criteria were designed to reduce unnecessary imaging while catching fractures reliably, with a sensitivity of approximately 97% in validation studies.
Beyond the Ottawa criteria, the following circumstances indicate that a same-day or next-day evaluation by a primary care physician, emergency medicine physician, sports medicine physician, or orthopedic surgeon is appropriate:
- Grade II or III injury with significant swelling, bruising, and difficulty walking despite attempted rest
- Plantar bruising appearing within 24 hours (possible Lisfranc injury)
- Pediatric foot injury in a child who refuses to bear weight or has point tenderness over a bone
- Symptoms that are worsening after 48 to 72 hours rather than plateauing
- Any foot injury in a person with diabetes, peripheral neuropathy, or other condition that reduces pain perception
- A foot injury in an older adult, particularly one with osteoporosis or who takes anticoagulant medications
- Prior history of chronic instability in the same foot and a new injury that feels different or more severe
For ongoing symptoms (pain or instability persisting beyond 4 to 6 weeks despite appropriate management), a referral to a board-certified sports medicine physician or board-certified orthopedic surgeon is the appropriate next step. MRI will typically be ordered at that stage to assess ligament integrity, cartilage status, and any associated injury to the joint.
When you do see a provider, bring a clear description of:
- The exact mechanism of injury (how the foot was positioned, what activity you were doing)
- Whether you could walk immediately after the injury
- Where the pain is worst and whether it is over a joint line or directly on a bone
- What you have done since injury (ice, compression, elevation, any weight-bearing)
- Any prior injuries to the same foot and whether they were fully evaluated
Frequently Asked Questions About Sprained Foot Symptoms
How do I know if my foot is sprained or broken?
The most reliable physical signs of a fracture are point tenderness directly over a bone (not over a joint line), visible deformity, and bruising that appears within the first few hours of injury.
A sprain produces tenderness over the ligament between bones, not over the bone itself, and bruising typically takes 24 to 72 hours to appear.
Because many fractures and sprains look identical on physical exam, the Ottawa Foot Rules and X-ray imaging are the clinical standard for distinguishing them when bone tenderness or inability to bear weight is present.
What does a sprained foot feel like?
A sprained foot typically feels painful and tender at the injury site, with swelling that builds over the first 24 to 48 hours and a sensation of tightness or fullness across the foot.
In mild sprains, walking is painful but possible; in more severe injuries, the foot feels unstable and weight-bearing may be too painful to attempt.
The injured area is usually warm to touch and tender when pressed, and bruising often develops across the dorsum (top) or lateral border of the foot within one to three days.
Can you walk on a sprained foot?
Walking on a sprained foot depends on the injury grade: Grade I sprains allow painful but functional weight-bearing, while Grade III (complete ligament rupture) typically makes full weight-bearing impossible.
The ability to take 4 steps immediately after injury is the weight-bearing criterion used in the Ottawa Foot Rules to determine whether imaging is needed.
If you cannot take 4 steps without severe pain or the foot giving way, the same-day evaluation by a primary care physician or emergency medicine physician is the appropriate step, not continued attempts to walk.
How long does swelling last with a sprained foot?
Swelling from a foot sprain typically peaks between 24 and 72 hours after injury and then gradually decreases over the following 1 to 2 weeks for Grade I injuries.
Grade II sprains may retain some residual swelling for 3 to 4 weeks, and Grade III injuries can have intermittent swelling for 6 to 12 weeks during the rehabilitation phase.
Swelling that continues to increase beyond 72 hours, or that returns after a period of improvement without a new injury, warrants evaluation to rule out a missed fracture or developing complication.
What are the signs of a serious foot sprain?
A serious foot sprain (Grade II or III) is indicated by inability to bear weight, rapid and severe swelling, bruising that appears within the first few hours, and a sensation of instability or complete “giving way” of the foot.
Plantar bruising (on the sole of the foot) appearing within 24 hours is a strong clinical indicator of Lisfranc ligament complex injury, which is a more serious injury requiring orthopedic evaluation.
Any combination of these features warrants same-day evaluation by a primary care physician, emergency medicine physician, or orthopedic surgeon.
Should I go to the ER for a sprained foot?
You should go to the nearest emergency room if you cannot bear weight at all, if there is visible deformity, if the foot feels numb or cold, or if there is an open wound over the injured area.
For moderate injuries where you can walk but have significant pain and swelling, an urgent care clinic or same-day appointment with a primary care physician is an appropriate alternative to the emergency room for most adults.
Children with foot injuries who refuse to bear weight should be evaluated in an emergency room or by a pediatrician the same day, given the risk of growth plate injury that may not be apparent on exam alone.
A foot sprain is not simply a soft tissue nuisance you rest through for a few days. The specific symptoms, their anatomical location, their timing, and their severity collectively tell you which structures are injured, how seriously, and what the right next step is.
If you have midfoot swelling with plantar bruising, point tenderness over bone, or inability to take 4 steps, those are not signs to monitor at home. They are the clinical signals that warrant same-day evaluation, imaging, and a clear diagnosis before you put more weight on that foot.
The reader who understands the difference between a Grade I lateral foot sprain they can manage with structured rest and a suspected Lisfranc injury they cannot is in a far better position than someone who guesses based on pain level alone. Use that understanding to make the call with confidence, either to your primary care physician, a sports medicine physician, or the emergency room, depending on what your symptoms are telling you.