Sprained Toe Symptoms: Signs, Severity, and When to Act
Sprained toe symptoms include localized pain, periarticular swelling, bruising, stiffness, and reduced ability to bear weight, and the specific pattern of these symptoms tells you whether you’re dealing with a minor ligament stretch or a complete structural tear that needs imaging. The difference between those two presentations is not always obvious from the outside, which is exactly why understanding what each symptom means anatomically matters before you decide whether to tape it and rest or go get an X-ray.
Toe sprains are among the most frequently underestimated musculoskeletal injuries in primary care and sports medicine. The American Academy of Orthopaedic Surgeons notes that foot and ankle ligament injuries account for a substantial proportion of sports-related musculoskeletal visits annually, and toe joint injuries are frequently misclassified as minor because of their anatomical location, which delays appropriate management of higher-grade tears.
This article covers every clinically recognized symptom of a sprained toe with the physiological mechanism behind each one, the three-grade severity classification with its distinct symptom profiles, how to distinguish a sprain from a fracture using validated clinical criteria, and the population-specific presentations that most general symptom guides miss entirely.
Sprained Toe Symptoms: The Full Clinical Picture
Sprained toe symptoms are caused by mechanical disruption of one or more ligaments surrounding a toe joint, triggering an acute inflammatory response that produces pain, swelling, bruising, stiffness, and functional instability at the affected joint.
The hallmark symptoms appear within minutes to hours of the injury and typically peak in severity between 24 and 72 hours. The specific combination of symptoms varies by which joint is injured (metatarsophalangeal vs. interphalangeal), which direction the force came from (hyperextension, lateral deviation, direct impact), and how severely the ligament fibers were disrupted (microscopic stretching vs. partial tear vs. complete rupture).
Here is the full clinical picture of sprained toe symptoms ranked by clinical significance:
| Symptom | Onset | Clinical Significance | When It Warrants Concern |
|---|---|---|---|
| Localized joint pain | Immediate | Primary sign of ligament injury | Pain disproportionate to injury or worsening after 48 hrs |
| Periarticular swelling | Minutes to hours | Inflammatory edema from capillary leak | Swelling spreading to entire forefoot |
| Bruising (ecchymosis) | Hours to 24 hrs | Extravasated blood from torn capillaries | Bruising tracking proximally up the foot |
| Stiffness and reduced ROM | Immediate to hours | Protective muscle guarding and joint effusion | Loss of all active movement |
| Tenderness to palpation | Immediate | Sensitized nociceptors at injury site | Tenderness over bone, not just soft tissue |
| Functional instability | Variable | Mechanoreceptor disruption from torn fibers | Feeling of joint “giving way” |
| Warmth and redness | Hours | Increased periarticular blood flow | Expanding warmth with fever (infection risk) |
Individual variation note: In people taking anticoagulant medications (warfarin, apixaban, rivaroxaban), bruising and swelling may be more pronounced and appear faster than in people without anticoagulation because vascular permeability changes are amplified by impaired coagulation. This population should seek professional evaluation for even moderate-appearing toe injuries to rule out hematoma formation requiring drainage.
What Is a Sprained Toe and Which Structures Are Injured
A sprained toe is an injury to one or more ligaments at a toe joint, produced by a force that stretches the ligament beyond its elastic capacity, causing microscopic or macroscopic tearing of its collagen fiber bundles.
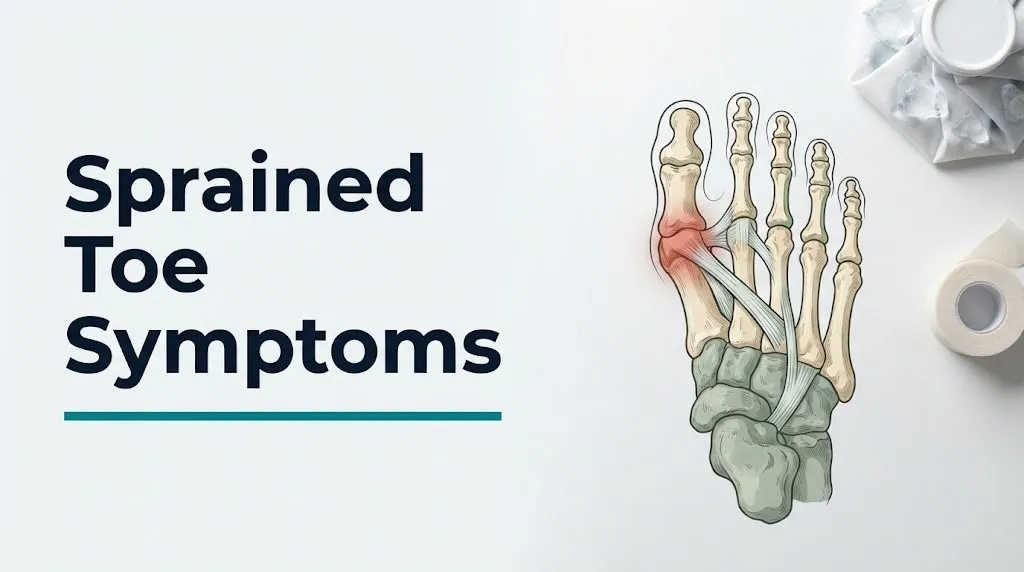
The toes contain two types of joints: the metatarsophalangeal (MTP) joints, where the toe bones (phalanges) meet the foot bones (metatarsals), and the interphalangeal (IP) joints within each toe (the proximal interphalangeal joint, or PIP, and the distal interphalangeal joint, or DIP). Each of these joints is stabilized by medial collateral ligaments and lateral collateral ligaments on either side, a plantar plate (a dense fibrocartilaginous pad at the underside of each MTP joint), and a dorsal capsule at the top of the joint.
Think of the plantar plate like the thick rubber sole on a good work boot. It sits at the bottom of each MTP joint, absorbs load, and prevents the toe from bending too far upward. When the toe is hyperextended forcefully (the classic mechanism for stubbing or jamming a toe), the plantar plate is the first structure to be stressed. In the big toe, this is called turf toe.
The sesamoid bones (two small oval bones embedded in the flexor hallucis brevis tendon beneath the first MTP joint) also come under stress in big toe injuries. Sesamoid fracture or sesamoiditis can produce symptoms that closely mimic a first MTP sprain. The volar plate at the IP joints functions similarly to the plantar plate at the MTP joint and is the structure most commonly injured in finger-like “jamming” injuries to the lesser toes.
According to the American Orthopaedic Foot and Ankle Society, the first metatarsophalangeal joint is the most commonly sprained toe joint in athletic populations, primarily because of its role as the terminal lever in push-off during gait and sprinting.
Individual variation note: In adolescent athletes whose physeal plates (growth plates, also called the physis) are still open, a force that sprains a ligament in an adult can instead fracture through the cartilaginous growth plate in a child. This is a Salter-Harris fracture, and it can look and feel almost identical to a soft tissue sprain on initial examination, which is why children with toe injuries generally require radiographic evaluation earlier than adults.
Pain From a Sprained Toe
Pain from a sprained toe is produced by the activation of nociceptors (specifically A-delta and C-fiber free nerve endings) embedded throughout the ligament, joint capsule, and periarticular soft tissue, which are directly stimulated by mechanical disruption of collagen fibers and chemically sensitized by inflammatory mediators released at the injury site.
Within seconds of ligament injury, mast cells in the periarticular tissue release histamine and the plasma kinin system generates bradykinin. Both of these molecules directly stimulate C-fiber nociceptors, producing the sharp, immediate pain felt at the moment of injury. Over the following minutes to hours, the COX-2 enzyme converts arachidonic acid into prostaglandin E2, which lowers the activation threshold of peripheral nociceptors. This sensitization is what produces hyperalgesia, the state in which the injured area hurts more than expected from a given stimulus, and is why light touch or gentle movement of a sprained toe produces pain that feels disproportionate to the force applied.
The pain from a sprained toe is typically well-localized to the joint line on the first examination. It worsens with active movement (flexion or extension of the toe), with passive range-of-motion testing, and with direct palpation over the affected ligament. Pain that reproduces maximally over the bone shaft or over a bony prominence rather than the joint line raises concern for fracture rather than ligament injury.
Key characteristics of sprained toe pain that distinguish it clinically from fracture pain:
- Located at the joint line or periarticular soft tissue, not the bone shaft
- Worsens with specific directional movement (the direction of the original injury)
- Reproduces with palpation of the ligament rather than bone
- Partial weight-bearing is generally possible in Grade I and II sprains (pain with weight, but possible)
Individual variation note: People with diabetic peripheral neuropathy affecting the feet may experience minimal or no pain despite a severe Grade III ligament tear or even an associated fracture. In this population, the absence of significant pain is not reassuring. Swelling, warmth, instability, and visible deformity become the primary diagnostic indicators because the nociceptive warning system is impaired.
Swelling From a Sprained Toe
Swelling from a sprained toe is periarticular edema, produced by increased vascular permeability in the small capillaries surrounding the injured joint, driven by prostaglandin E2, histamine, and bradykinin released during the acute inflammatory cascade.
When capillary walls in the periarticular tissue are chemically dilated, protein-rich plasma fluid leaks into the interstitial space faster than the lymphatic system can clear it. This fluid accumulation is what you see and feel as swelling around the toe joint. In moderate to severe sprains, synovial tissue inside the joint capsule also responds to the injury by producing excess synovial fluid, creating a joint effusion that adds to the visible swelling over the joint itself.
Swelling peaks between 24 and 72 hours after injury as the inflammatory response reaches its maximum. A sprained toe that is still swelling or worsening after 72 hours, rather than showing early stabilization, suggests either a more severe injury grade than initially apparent or a missed fracture contributing additional tissue disruption.
The distribution of swelling also carries diagnostic information. Swelling tightly localized to one joint suggests injury at that joint. Swelling that spreads rapidly across the entire forefoot or tracks up toward the ankle suggests a more extensive injury, possible fracture, or in rare cases, early acute compartment syndrome of the foot.
Quick Tip:
- Ice application (wrapped in a cloth, never directly on skin) for 20 minutes every 1 to 2 hours during the first 48 hours reduces prostaglandin-mediated vasodilation and limits edema volume.
- Elevation of the foot above heart level uses gravity to reduce hydrostatic pressure in the capillary bed, slowing additional fluid accumulation into the interstitial space.
- People with congestive heart failure or chronic venous insufficiency may develop proportionally greater swelling from the same injury because their baseline venous return is already compromised; seek professional evaluation sooner in this population.
Individual variation note: In pregnant individuals, generalized lower extremity edema from increased plasma volume and reduced venous return can mask or amplify the localized swelling from a toe sprain, making it harder to assess whether swelling is injury-related or systemic. A podiatrist (DPM) or primary care physician should evaluate any toe injury during pregnancy if swelling appears disproportionate or does not respond to elevation within 24 hours.
Key Takeaway: Swelling that is still increasing after 72 hours, or that spreads beyond the injured toe joint to the forefoot, is a reliable signal that the injury may be more severe than a simple Grade I ligament stretch, and warrants professional evaluation with plain radiographs.
Bruising From a Sprained Toe
Bruising (ecchymosis) from a sprained toe is visible because torn capillaries and small vessels within the injured ligament, joint capsule, and periarticular soft tissue release erythrocytes (red blood cells) into the surrounding subcutaneous tissue, where hemoglobin undergoes stepwise enzymatic breakdown into biliverdin and bilirubin, producing the characteristic color progression from dark red-purple to green to yellow over 7 to 14 days.
Not every sprained toe produces visible bruising, particularly in Grade I sprains where capillary disruption is minimal. According to clinical observation published in sports medicine literature, bruising is more consistently present in Grade II and Grade III sprains, where macroscopic ligament tearing disrupts more capillary beds simultaneously. The absence of bruising does not rule out a significant sprain, and its presence does not distinguish sprain from fracture.
The location and tracking of bruising is clinically useful. Bruising that appears directly over the injured joint and remains localized there is consistent with periarticular ligament injury. Bruising that tracks across the plantar surface of the foot, or that appears proximally on the dorsum of the foot away from the original injury site within 24 to 48 hours, suggests deeper tissue disruption or a bony injury where the hematoma is tracking along tissue planes from the fracture site.
Individual variation note: People with fair or thin skin (common in older adults and those with long-term corticosteroid use) may develop more dramatic-appearing bruising from minor sprains because subcutaneous tissue provides less resistance to hematoma spreading. Conversely, individuals with darker skin tones may have bruising that is difficult to see on visual inspection; palpation for tenderness and firmness over the injured area is a more reliable assessment tool than visual inspection alone in this population.
Sprained Toe Stiffness and Limited Range of Motion
Stiffness and reduced range of motion in a sprained toe result from two simultaneous mechanisms: protective muscle guarding (involuntary co-contraction of muscles surrounding the injured joint, mediated by pain-avoidance reflexes through the spinal cord) and joint effusion (excess fluid accumulation in the joint capsule that physically limits the available arc of movement).
In the acute phase (first 48 to 72 hours), nearly all toe sprains produce some degree of movement restriction. The flexor and extensor tendons crossing the injured joint reflexively tighten to splint the area, a response mediated through spinal cord interneurons that receive input from sensitized C-fiber nociceptors at the injury site. This is a protective mechanism. It limits further movement of the damaged ligament while acute repair begins.
Think of it like a muscle cramp that protects a fragile structure. The surrounding muscles won’t let the joint move freely because moving it risks further tissue disruption. The joint effusion compounds this by distending the capsule, which mechanically prevents full flexion or extension the way an overfilled water balloon resists compression.
Persistent stiffness beyond 3 to 4 weeks, or stiffness that worsens rather than gradually improves with gentle movement, should prompt professional evaluation. Prolonged stiffness can indicate periarticular fibrosis (scar tissue formation from poorly managed acute inflammation), a missed fracture with callus formation, or an unrecognized complete ligament rupture producing joint instability that triggers chronic protective guarding.
The National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIAMS) notes that early controlled mobilization within the pain-free range, beginning after the acute inflammatory phase (generally after 48 to 72 hours), improves collagen fiber alignment during the healing process and reduces the risk of permanent range-of-motion restriction compared with prolonged immobilization.
Individual variation note: Older adults with pre-existing osteoarthritis at the toe joints may have baseline stiffness and limited range of motion before an injury occurs. In this population, it is worth documenting the pre-injury range of motion (or estimating it from the uninjured side) so that post-injury restriction can be accurately attributed to the acute injury rather than the underlying degenerative joint change.
Grade 1, Grade 2, and Grade 3 Toe Sprain Symptoms
The three-grade classification of ligament sprains reflects the degree of collagen fiber disruption and the corresponding severity of symptoms, functional impairment, and expected recovery time, with Grade I representing microscopic injury and Grade III representing complete structural failure of the ligament.
Grade I toe sprain involves microscopic tearing of individual collagen fibers within the ligament with no macroscopic disruption of the ligament’s structural continuity. The joint remains stable. Symptoms include mild, well-localized pain at the joint line, mild swelling that develops within the first few hours and typically peaks before 24 hours, little or no visible bruising, preserved weight-bearing ability (painful but possible), and minimal range-of-motion restriction. Most people with Grade I sprains can bear weight with discomfort and do not experience instability.
Grade II toe sprain involves partial macroscopic tearing of the ligament, where enough fiber bundles are disrupted to reduce the ligament’s structural integrity but not eliminate it entirely. Symptoms include moderate pain that is worse with weight-bearing and movement, moderate to significant swelling peaking at 24 to 72 hours, visible bruising in the majority of cases, noticeably limited range of motion from guarding and effusion, and mild to moderate joint laxity on stress testing (the joint opens further than normal when gentle force is applied to the affected side, but has a firm endpoint).
Grade III toe sprain is a complete ligament rupture with loss of structural continuity across the full ligament width. Symptoms include severe immediate pain that may paradoxically decrease quickly after the rupture (because the ligament can no longer generate tension), rapid and pronounced swelling, significant bruising, markedly limited range of motion, and joint instability with no firm endpoint on stress testing (the joint opens excessively with no resistance). Weight-bearing may be severely limited or impossible.
| Grade | Fiber Disruption | Pain Level | Weight-Bearing | Instability | Typical Recovery |
|---|---|---|---|---|---|
| Grade I | Microscopic only | Mild | Possible with discomfort | None | 1 to 2 weeks |
| Grade II | Partial macroscopic | Moderate | Painful, limited | Mild to moderate | 3 to 6 weeks |
| Grade III | Complete rupture | Severe (may diminish rapidly) | Severely limited or impossible | Marked (no endpoint) | 6 to 12+ weeks |
Individual variation note: High-level athletes may sustain Grade II or III sprains through high-energy mechanisms but continue playing through pain due to adrenaline-mediated analgesia at the time of injury. Delayed onset of full symptom severity (swelling and stiffness developing fully only hours later) is common in athletic injuries and does not indicate a less severe grade.
Key Takeaway: Grade III toe sprains can paradoxically feel less painful immediately after injury than Grade II sprains because a completely ruptured ligament no longer generates the tension that stimulates nociceptors. Feeling that the pain “isn’t that bad” shortly after a high-energy toe injury is not reassurance that the injury is minor.
Acute vs. Chronic Sprained Toe Symptoms
The acute presentation of a sprained toe refers to the symptom pattern in the first 1 to 2 weeks after injury, while chronic presentation refers to symptoms persisting beyond 6 weeks that indicate incomplete healing, structural instability, or the development of secondary complications from a poorly managed initial injury.
In the acute phase (day 1 through approximately day 10 to 14), symptoms reflect the active inflammatory and early repair processes: pain is present at rest and worsens with activity, swelling is visible and palpable, bruising may still be present and evolving in color, range of motion is restricted by guarding and effusion, and weight-bearing is limited by pain.
The subacute phase (approximately week 2 through week 6) is characterized by gradual symptom resolution as the inflammatory mediators diminish, edema clears through lymphatic drainage, and fibroblasts begin laying down new collagen across the tear site. Pain should progressively improve with gentle weight-bearing, swelling should be noticeably decreasing, and range of motion should be gradually returning. A sprained toe that is not showing measurable improvement by the end of week 2 warrants professional evaluation./
Chronic toe sprain symptoms (beyond 6 weeks) include persistent joint-line pain with specific activities (particularly push-off in walking or running), recurring swelling after activity, a sense of joint looseness or “giving way” during weight-bearing, and sometimes a clicking or catching sensation in the joint produced by scar tissue or a partially healed plantar plate fragment catching on joint structures. These chronic symptoms often represent periarticular fibrosis, unresolved instability, or an unrecognized Grade III tear that was never appropriately immobilized during healing.
Individual variation note: People who returned to full activity too quickly after a toe sprain (a common pattern in recreational athletes who undertape and push through residual pain) are at higher risk for developing chronic instability because the collagen remodeling phase of healing requires 6 to 12 weeks of reduced mechanical load to produce organized, mechanically competent scar tissue. Premature return to high-impact activity disrupts this process and leads to disorganized, weaker scar tissue that is more prone to re-injury.
Sprained Toe vs. Broken Toe Symptoms
Distinguishing a sprained toe from a broken toe (fracture) based on symptoms alone is not reliably possible, and this is one of the most practically important clinical questions surrounding toe injuries, because the two conditions require different management approaches.
The symptom overlap between sprain and fracture is substantial. Both produce immediate pain, swelling, bruising, tenderness to palpation, and limited range of motion. Both can present with or without the ability to bear weight. The clinical distinction is made more reliably by the location of tenderness, the mechanism of injury, and validated clinical decision frameworks than by pain intensity alone.
The Ottawa Foot Rules, validated in a landmark study published in the Annals of Emergency Medicine, provide a clinically validated framework for deciding whether radiographic evaluation is needed after a foot or toe injury. While the original Ottawa rules were developed for midfoot and fifth metatarsal injuries, their principles of bony tenderness mapping and weight-bearing capacity assessment apply to toe injuries as well. An inability to bear weight (take 4 steps) immediately after injury and at the time of examination is one of the most reliable indicators that an X-ray is needed.
Distinguishing features that suggest fracture rather than sprain:
- Tenderness that localizes directly over the bone shaft or a bony prominence (rather than exclusively at the joint line or ligament insertion)
- Visible angular deformity or rotational malalignment of the toe
- A palpable crepitus (grinding or crackling sensation) over the bone with gentle manipulation
- A distinct “crack” or “snap” heard or felt at the moment of injury
- Inability to bear any weight on the foot at all, even briefly
Individual variation note: In children, a fracture through the cartilaginous growth plate (Salter-Harris fracture) can be present at the base of a phalanx with only mild symptoms and without visible deformity. The growth plate in children is mechanically weaker than the surrounding ligament, so the bone fractures at the physis before the ligament tears. Point tenderness at the base of the phalanx in a child (not at the joint line) should prompt radiographic evaluation by a primary care physician or emergency medicine physician before a diagnosis of “sprain” is made.
Turf Toe Symptoms
Turf toe is a sprain of the plantar plate and associated soft tissue structures at the first metatarsophalangeal joint (first MTP joint), produced by forced hyperextension of the great toe, and it presents with a distinct symptom profile that differs from a generic MTP joint collateral ligament sprain in its mechanism, severity, and recovery trajectory.
The name comes from its association with athletes playing on artificial turf surfaces, which provide less shoe-surface friction than natural grass, allowing the foot to plant firmly while the body continues forward, forcing the great toe into extreme dorsiflexion. The plantar plate (the fibrocartilaginous pad at the plantar surface of the first MTP joint) is the primary structure disrupted, though the joint capsule, medial and lateral collateral ligaments, and sesamoid bone attachments may all be involved in higher-grade injuries.
Turf toe symptoms include:
- Immediate pain at the plantar and medial aspect of the first MTP joint, often described as sharp and pressure-like during push-off
- Swelling over the plantar surface of the first MTP joint (which is clinically distinct from the dorsal swelling seen in dorsal capsule injuries)
- Bruising at the plantar aspect of the first MTP joint or spreading into the first web space
- Marked pain with dorsiflexion (bending the big toe upward) and push-off, while plantarflexion is relatively less painful
- A sense of weakness in push-off even after pain begins to improve, reflecting disrupted plantar plate biomechanical function
The Clinical Journal of Sport Medicine has published a turf toe-specific grading system: Grade 1 involves stretching of the plantar complex with minimal symptoms and full weight-bearing; Grade 2 involves partial tearing with moderate pain, swelling, and limited motion; Grade 3 involves complete disruption with severe pain, inability to push off, and often sesamoid bone involvement requiring imaging.
Individual variation note: Female athletes in sports requiring significant toe push-off (gymnastics, dance, sprinting) may develop sesamoid stress fractures alongside or instead of turf toe, producing a symptom presentation that overlaps closely with Grade 2 or 3 turf toe. A sports medicine physician familiar with sesamoid pathology should evaluate any first MTP injury in a female athlete that does not respond to conservative management within 2 to 3 weeks.
Key Takeaway: Turf toe is not a “minor” big toe sprain. A Grade 2 or 3 turf toe involves disruption of the plantar plate, which is a load-bearing fibrocartilaginous structure, and recovery timelines of 6 to 12 weeks or longer are common, particularly in athletes who continue activity through early symptoms.
Sprained Big Toe Symptoms
Sprained big toe symptoms tend to be more functionally disabling than injuries to the lesser toes because the first MTP joint bears approximately 40 to 60 percent of the body’s total weight during the push-off phase of walking and running, making any instability or pain at this joint disproportionately impactful on gait.
A sprain of the first MTP joint produces pain at the medial or lateral joint line (depending on which collateral ligament is injured), or at the plantar surface of the joint if the plantar plate is involved. The first toe also contains the tibial and fibular sesamoid bones, embedded in the flexor hallucis brevis tendon directly beneath the first MTP joint. These bones transmit forces from the intrinsic foot muscles to the base of the great toe during push-off, and they can be fractured or displaced when the first MTP joint sustains significant hyperextension or axial loading.
Pain specifically on the underside of the first MTP joint that worsens when rising onto the balls of the feet is a clinical feature that distinguishes a plantar plate or sesamoid injury from a pure collateral ligament sprain (where pain is typically at the joint margin, not the plantar surface). Weight-bearing in a flat shoe or barefoot tends to compress the sesamoids, worsening sesamoid-related pain, while a rigid-soled shoe or a shoe with an elevated heel reduces this compression.
Key symptoms that distinguish a first MTP sprain from other first toe pathology:
- Pain at the medial or lateral joint line (collateral ligament injury)
- Pain at the plantar surface of the first MTP joint, worse with rising onto toes (plantar plate or sesamoid involvement)
- Difficulty pushing off during walking (functional deficit from plantar plate disruption)
- Swelling localized to the first MTP joint, distinct from midfoot or bunion-related swelling
Individual variation note: People with hallux valgus (bunion deformity) have a pre-existing alteration of first MTP joint mechanics, with lateral deviation of the great toe and medial subluxation of the first metatarsal head. An acute sprain in this population may produce symptoms that are difficult to attribute specifically to the acute injury versus the pre-existing deformity, and a podiatrist (DPM) or board-certified orthopedic foot and ankle surgeon should evaluate the injury to establish the acute component.
Sprained Little Toe Symptoms
A sprained little toe (fifth toe, or digitus minimus pedis) typically involves injury to the collateral ligaments or IP joints of the fifth digit, or occasionally the fifth MTP joint, and is often produced by a direct lateral impact (catching the little toe on furniture) or an inversion mechanism where the foot rolls outward.
The little toe lacks the weight-bearing responsibility of the first toe, so functional impairment from a sprained fifth toe is less severe in terms of gait disruption. However, the fifth toe is the most laterally exposed digit and is consequently the most frequently injured toe in everyday household trauma. It is also anatomically close to the styloid process of the fifth metatarsal, a bony prominence at the base of the fifth metatarsal where the peroneus brevis tendon inserts. An avulsion fracture at this location (where the tendon pulls a fragment of bone off the styloid process during an inversion injury) can produce symptoms almost identical to a fifth MTP or fifth toe sprain.
This makes the fifth toe one of the locations where the sprain-vs-fracture distinction is most clinically pressing. Tenderness that localizes to the base of the fifth metatarsal (approximately 2 to 3 centimeters proximal to the toe itself) rather than the toe joint is a specific indicator for fifth metatarsal styloid fracture and warrants radiographic evaluation regardless of the ability to bear weight.
Symptoms of a sprained fifth toe:
- Pain at the lateral aspect of the fifth MTP joint or along the shaft of the proximal phalanx
- Swelling localized to the fifth toe, sometimes with rapid bruising due to thin subcutaneous tissue on the lateral foot
- Tenderness at the joint line or ligament insertion points of the fifth toe
- Preserved but painful range of motion in partial injuries
Individual variation note: People who habitually walk barefoot or in minimal footwear (flexible sandals, slip-on shoes) sustain little-toe sprains and avulsion injuries at a higher rate from low-furniture impact injuries because the lateral forefoot receives no protective buffer from shoe upper materials.
Sprained Toe Symptoms in Children and Older Adults
In children, the key clinical distinction is that the physeal growth plate at the base of each phalanx is the mechanically weakest point in the toe’s structural chain, meaning the same force that produces a ligament sprain in an adult is more likely to fracture through the cartilaginous physis in a skeletally immature child.
A Salter-Harris fracture of the phalanx in a child can present with point tenderness at the physeal line (typically at the base of the proximal phalanx), mild swelling, and minimal deformity. On plain radiograph, non-displaced Salter-Harris Type I fractures may not show a visible fracture line because the fracture is through cartilage that does not appear on X-ray. These injuries are diagnosed by the clinical pattern of physeal-line tenderness in a child rather than by radiographic confirmation.
The American Academy of Pediatrics recommends that any toe injury in a child younger than 16 years with point tenderness at a bony location (rather than purely at the joint line soft tissue) be evaluated with plain radiographs before a diagnosis of soft tissue sprain is assigned, because missed physeal fractures can cause growth disturbance if the physis is not adequately protected during healing.
In older adults, the primary concern is that osteoporosis or osteopenia lowers the fracture threshold, meaning the same low-energy mechanism that produces a Grade I sprain in a younger person may produce a complete phalangeal fracture in a person with reduced bone mineral density. Women over 65 and men over 70 are the populations with the highest prevalence of clinically relevant osteoporosis, according to the National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIAMS).
Individual variation note: Older adults on long-term corticosteroid therapy (prednisone and similar agents) have additional bone density reduction beyond age-related loss and soft tissue fragility from corticosteroid-related collagen inhibition, making their toe injuries more likely to involve combined fracture and ligament disruption even from minimal trauma. A primary care physician or podiatrist should evaluate any toe injury in a patient on chronic corticosteroid therapy.
Sprained Toe Symptoms in People With Diabetes or Inflammatory Arthritis
In people with diabetes mellitus who have developed peripheral neuropathy, the neurological warning system that normally makes a sprained toe painful is partially or completely impaired, which means a significant toe injury, including a Grade III ligament rupture or even a fracture, may produce remarkably little pain and very little functional disability at the time of injury.
This is not a reassuring picture. The absence of significant pain in a diabetic foot injury does not mean the injury is minor. It means the nociceptive signal is being blocked before it reaches conscious awareness. Swelling, warmth, and visible deformity become the primary observable indicators of injury severity in this population. Any swollen, warm, or deformed toe in a person with known diabetic neuropathy warrants same-day evaluation by a primary care physician, podiatrist, or endocrinologist familiar with diabetic foot complications, with plain radiographs to assess for fracture and assessment for the early signs of Charcot arthropathy (a serious progressive joint destruction process that can begin with what appears to be a minor foot injury).
In people with gout (monosodium urate crystal deposition disease), an acute gout flare at the first MTP joint (called podagra) produces symptoms that are clinically almost indistinguishable from a high-grade toe sprain: severe pain, marked swelling, redness, warmth, and inability to bear weight. The critical distinction is that gout typically develops without a clear traumatic event, progresses over 12 to 24 hours to reach maximum severity, and may be accompanied by fever. A sprain typically follows a clear mechanical event.
In people with rheumatoid arthritis, chronic MTP joint inflammation and ligamentous laxity from synovial proliferation means that acute toe injuries occur on a background of pre-existing joint changes, making it difficult to assess what is acute injury versus underlying disease activity. A rheumatologist familiar with the patient’s baseline joint status should be involved in evaluating any new acute toe injury in this population.
Individual variation note: Serum uric acid measurement and joint aspiration for crystal analysis are the definitive diagnostic tools for distinguishing gout from traumatic toe sprain when the clinical picture is ambiguous; these tests require evaluation by a primary care physician or emergency medicine physician.
Key Takeaway: In people with diabetic peripheral neuropathy, the severity of a toe injury must be assessed primarily through swelling, warmth, and deformity rather than pain, because neuropathy can completely suppress the pain signal even from a fracture or complete ligament rupture.
When to See a Doctor for a Sprained Toe
Certain presentations of a toe injury require professional medical evaluation and should not be managed with home monitoring alone, regardless of whether the injury initially seems minor.
See a primary care physician, sports medicine physician, or podiatrist (DPM) within 24 to 48 hours if:
- You cannot bear weight on the foot at all, even briefly
- Swelling is substantial or spreading beyond the injured toe to the forefoot
- Pain is worsening rather than improving after 48 hours
- Bruising is tracking proximally up the foot from the injury site
- The toe appears visibly deformed, angulated, or rotated compared to the uninjured side
- The injury involves the first (big) toe with pain specifically at the plantar surface (possible plantar plate or sesamoid involvement)
- The child injured is younger than 16 and has tenderness at a bony location (possible physeal fracture)
- You have diabetes, peripheral neuropathy, gout, rheumatoid arthritis, or osteoporosis
- You are taking anticoagulant medications (warfarin, apixaban, rivaroxaban, dabigatran)
See an emergency medicine physician or go to the nearest emergency room if:
- The toe appears severely deformed, dislocated, or has a wound over it suggesting an open fracture
- There is numbness, tingling, or pallor in the toe or forefoot (possible neurovascular compromise)
- Pain is severely disproportionate to the injury mechanism
- Warmth and redness are spreading and accompanied by fever (possible infected wound or septic arthritis)
At your appointment, tell your provider:
- The exact mechanism of injury (direction of force, what you were doing)
- Whether you heard or felt a snap, pop, or crack
- Whether you could bear weight immediately after injury
- Your baseline medications, especially anticoagulants or corticosteroids
- Any pre-existing toe or foot conditions
Individual variation note: Athletes in competitive sports should be seen by a sports medicine physician with experience in foot injuries rather than a general urgent care provider, because sports-medicine-specific grading of turf toe or MTP ligament injuries directly determines return-to-play protocols and whether MRI is needed to assess plantar plate integrity before resuming training.
Emergency Symptoms: When to Go to the Emergency Room
Certain toe injury presentations require immediate emergency evaluation. Do not wait to see if these resolve on their own.
Go to the nearest emergency room immediately if you experience:
- Severe progressive pain in the toe or foot that is disproportionate to the injury mechanism, with the skin over the foot becoming tight, shiny, or unusually firm (possible acute compartment syndrome of the foot, a surgical emergency)
- A wound or laceration over or near the injured toe, particularly if bone is visible or the skin is broken over a deformed joint (possible open fracture requiring immediate surgical evaluation)
- Numbness, tingling, pallor, or absence of a palpable pulse in the toes following a toe or foot injury (possible neurovascular compromise from dislocation or severe fracture)
- A toe that is visibly dislocated (displaced completely out of the joint with obvious step-off deformity) and cannot be gently reduced
- Progressive worsening of pain in a diabetic foot injury with spreading redness and fever (possible septic arthritis or early Charcot arthropathy)
These presentations indicate conditions beyond a soft tissue sprain and require emergency surgical or medical assessment, not an urgent care appointment scheduled for the next day.
How a Sprained Toe Is Diagnosed
A sprained toe is diagnosed through a combination of clinical history, physical examination, and imaging, with the specific tests ordered determined by the severity of symptoms and the clinical concern for fracture, complete ligament rupture, or other structural injury.
The clinical history focuses on the mechanism of injury (direction and force), immediate symptoms (pain, ability to bear weight, audible crack), and subsequent symptom progression. The physical examination includes palpation along the joint lines and bone shafts to localize tenderness, assessment of active and passive range of motion at each toe joint, and stress testing of the collateral ligaments (applying gentle medial and lateral force to the joint while the joint is in slight flexion to isolate collateral ligament laxity).
Imaging is ordered based on the Ottawa Foot Rules principle: when there is bony tenderness, inability to bear weight, or visible deformity, plain radiographs (X-rays) of the foot and toe are obtained. Most foot and ankle radiographic series include anteroposterior (AP), lateral, and oblique views. Weight-bearing views are preferable when the patient can tolerate them because they reveal dynamic joint alignment that non-weight-bearing views may miss.
Diagnostic test options for suspected toe sprain:
| Test | What It Shows | When It Is Ordered |
|---|---|---|
| Plain radiograph (X-ray) | Fracture, avulsion, joint alignment | Bony tenderness, inability to bear weight, deformity |
| Weight-bearing radiograph | Dynamic joint space, sesamoid position | Suspected instability or sesamoid injury |
| MRI of foot | Plantar plate integrity, Grade III ligament tears, bone marrow edema | Persistent symptoms beyond 4 to 6 weeks, suspected turf toe Grade 2-3 |
| Diagnostic ultrasound | Collateral ligament continuity, dynamic stress assessment | Sports medicine settings; real-time stress testing |
| Stress radiograph | Ligament laxity quantification under controlled force | Suspected Grade III instability before surgical decision |
According to the American Academy of Orthopaedic Surgeons, MRI is the imaging modality of choice for assessing plantar plate integrity in first MTP joint injuries when plain radiographs are negative but symptoms suggest Grade 2 or 3 turf toe. MRI can detect bone marrow edema at the sesamoids (indicating sesamoid stress fracture or sesamoiditis), plantar plate tearing, and collateral ligament disruption with a level of detail that plain X-ray cannot provide.
Individual variation note: In children, MRI or dedicated oblique radiographic views may be needed to visualize a Salter-Harris Type I fracture that does not show a fracture line on standard plain films. If a child has physeal-line tenderness with a normal X-ray, the injury should still be treated as a presumptive physeal fracture and managed with appropriate immobilization while being followed by a primary care physician or pediatric orthopedic surgeon.
Frequently Asked Questions About Sprained Toe Symptoms
What does a sprained toe feel like?
A sprained toe feels like sharp, localized pain at the toe joint immediately after the injury, followed by progressive swelling and stiffness over the next several hours.
The pain is typically worst at the joint line or the specific ligament that was stretched, worsens with movement in the direction of the injury, and may be accompanied by a throbbing ache at rest.
Weight-bearing is painful but often possible in mild to moderate sprains, while severe sprains may make any pressure on the foot feel intolerable.
How do I know if my toe is sprained or broken?
You cannot reliably distinguish a sprained toe from a broken toe based on pain intensity alone, because both injuries produce similar symptoms.
Tenderness located directly over the bone shaft (rather than the joint line), visible deformity or rotational malalignment of the toe, and inability to take 4 steps are clinical indicators that increase the likelihood of a fracture and warrant radiographic evaluation.
A plain X-ray ordered by a primary care physician, emergency medicine physician, or podiatrist is the only way to definitively confirm or rule out a fracture.
Can a sprained toe bruise without being broken?
Yes, bruising is a normal and expected symptom of a sprained toe, particularly in Grade II and Grade III ligament tears where torn capillaries in the injured ligament and periarticular tissue release blood into the subcutaneous tissue.
Bruising does not distinguish between a sprain and a fracture because both injuries disrupt capillaries in the periarticular area.
The location, distribution, and spread of the bruising over 24 to 48 hours provides more diagnostic information than its presence or absence alone.
How long does it take for a sprained toe to stop hurting?
A Grade I toe sprain typically produces pain that improves substantially within 7 to 14 days with appropriate rest, taping, and activity modification.
Grade II sprains generally take 3 to 6 weeks for pain to resolve with activity, while Grade III sprains involving complete ligament rupture or plantar plate disruption may produce pain for 6 to 12 weeks or longer, particularly with push-off activities.
Pain that is not showing measurable improvement by 2 weeks, or that worsens after an initial period of improvement, warrants evaluation by a primary care physician or podiatrist to rule out a missed fracture or non-healing ligament tear.
Can you walk on a sprained toe?
Walking is possible with a mild to moderate sprained toe, though it will be painful, particularly during push-off and when descending stairs.
A rigid-soled shoe or a post-operative shoe that limits toe joint flexion significantly reduces the load on the injured ligament and makes weight-bearing more tolerable during the early healing phase.
Complete inability to bear weight after a toe injury is a clinical indicator that imaging is needed, per the Ottawa Foot Rules principle, because it increases the probability of a fracture.
What is turf toe and how is it different from a regular toe sprain?
Turf toe is a specific sprain of the plantar plate and surrounding soft tissue at the first metatarsophalangeal joint, produced by forced hyperextension of the great toe, rather than a collateral ligament sprain from a sideways force.
The plantar plate is a fibrocartilaginous load-bearing structure, and its disruption produces pain specifically on the underside of the first MTP joint that worsens with push-off, which is distinct from the joint-line pain of a typical collateral ligament sprain.
Grade 2 and Grade 3 turf toe often require MRI for plantar plate assessment and have recovery timelines of 6 to 12 weeks or longer, making early sports medicine evaluation advisable for athletes.
Closing
A toe injury that produces pain, swelling, and bruising is telling you that at least one ligament has been disrupted at the joint level. The most important question is not “is this a sprain?” but “what grade is it, and is there a fracture involved?” Those two questions determine whether you tape it and rest or get an X-ray and see a specialist.
If you can bear weight, the injury happened from a low-energy mechanism, swelling is localized to one joint, and your symptoms are improving by 48 to 72 hours, monitoring at home with rest, taping, and a stiff-soled shoe is a reasonable approach. If any of those conditions don’t apply, contact a primary care physician, sports medicine physician, or podiatrist (DPM) for same-day or next-day evaluation with plain radiographs.
The symptom that most often gets missed is failure to improve. A sprained toe that is still as painful or more swollen at two weeks than it was at day two is not a normal healing trajectory, and that’s the signal to stop waiting and get it properly evaluated.