Bad AC Capacitor Symptoms: Heat Illness Health Risks 2026
Bad AC capacitor symptoms are not just mechanical warning signs for your HVAC system. They are also the starting point for a chain of heat-related health events that can escalate from discomfort to a life-threatening emergency, particularly when capacitor failure leaves a home or workplace without functional cooling in hot weather.
The Centers for Disease Control and Prevention (CDC) reports that extreme heat kills more Americans each year than any other weather-related event, with loss of indoor cooling being a primary contributing factor in heat-related deaths. The same agency’s surveillance data shows that residential settings account for a substantial proportion of heat stroke fatalities, most of which occur in homes where air conditioning has failed or is absent.
This article covers the full health picture: what your body experiences when an AC system fails due to capacitor failure, the physiological reasons each symptom occurs, which populations face the greatest danger, how to distinguish heat exhaustion from heat stroke, and exactly when to call 911.
Bad AC Capacitor Symptoms: What Happens to Your Body
Bad AC capacitor symptoms, from a health perspective, begin when an indoor space loses its ability to maintain a safe ambient temperature, forcing the human body to work progressively harder to prevent core temperature from rising to dangerous levels.
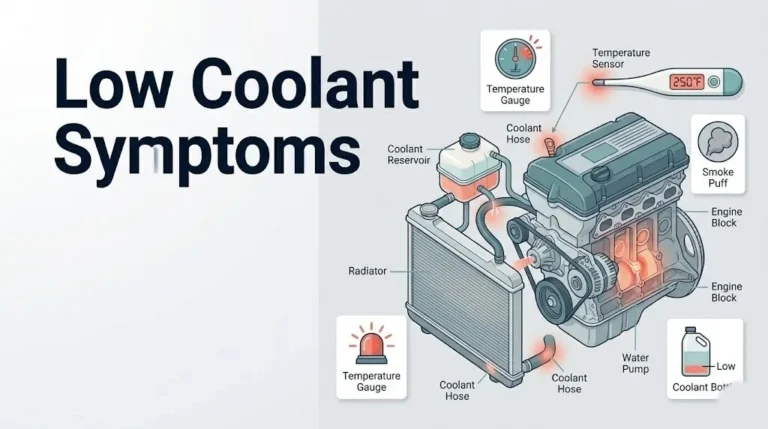
An AC capacitor is the cylindrical component that stores electrical charge and releases it to start and sustain the compressor motor and fan motors. When it fails, the entire cooling cycle stops. In summer months, indoor temperatures in an un-air-conditioned home can rise rapidly. Research published in the journal Environmental Health Perspectives found that indoor temperatures in closed residences can exceed outdoor temperatures by 5 to 10°F during the afternoon heat peak, creating conditions that exceed the body’s thermoregulatory capacity within hours.
The body’s first physical responses to rising indoor temperature include an increase in skin blood flow, the onset of sweating, and a rise in heart rate. These are compensatory physiological responses managed by the hypothalamus and the autonomic nervous system. They are not symptoms of illness. They become symptoms when the compensatory system is overwhelmed.
What happens physically when indoor cooling fails:
- Skin becomes flushed, warm, and moist as the body attempts to transfer heat to the environment
- Heart rate rises to maintain blood pressure as blood redistributes from core organs to the skin surface
- Thirst sensation intensifies as the body begins to lose fluid through sweating
- Fatigue and cognitive slowness develop as the brain begins operating in a higher-temperature environment
- Muscle cramping can begin in the legs and abdomen as electrolyte losses from sweat accumulate
Older adults over age 65 may not experience thirst sensation accurately, because the thirst mechanism becomes less sensitive with age per research cited by the National Institute on Aging. This means an older adult in a home with a failed AC system may not drink enough to replace sweat losses, accelerating dehydration and heat illness progression without recognizing the early warning signals.
AC Capacitor Symptoms and Their Health Effects
AC capacitor symptoms, the signs that the capacitor is failing before complete breakdown, provide a warning window during which residents can take protective action before serious heat illness develops.
The classic mechanical signs of a failing AC capacitor include the unit humming without starting, the AC taking much longer than usual to begin cooling, warm air blowing despite the thermostat being set low, and the system shutting off shortly after starting. Each of these mechanical failures has a direct health consequence: the home temperature rises, and the body begins the physiological stress response described below.
Think of the AC capacitor like the starter mechanism in a car engine. When a car’s starter fails, the engine does not run and the vehicle goes nowhere. When an AC capacitor fails, the compressor does not run and the cooling cycle stops. The difference is that without a car, you might be inconvenienced. Without cooling in a heat wave, vulnerable people in your home may be in danger within hours.
Health effects that emerge as AC capacitor failure progresses:
| AC Failure Stage | Indoor Consequence | Body Response | Health Risk Level |
|---|---|---|---|
| Partial failure (unit cycles poorly) | Room 5-10°F above set temperature | Mild heat stress, increased sweating | Low to moderate |
| Complete failure in mild heat (below 85°F outdoor) | Indoor temp reaches 80-90°F | Significant sweating, fatigue | Moderate |
| Complete failure in high heat (above 90°F outdoor) | Indoor temp reaches 90-105°F | Early heat exhaustion symptoms | High |
| Complete failure during heat wave (above 95°F outdoor, high humidity) | Indoor temp may exceed 105°F | Heat stroke risk within hours | Emergency |
Children under age 12 months are at elevated health risk even during the partial failure stage because their eccrine sweat gland system is not yet fully mature. Infants cannot sweat as efficiently as adults and cannot move themselves to a cooler area or request fluids. Caregivers should monitor indoor temperature directly when AC is functioning poorly, not rely on infant behavior alone as an indicator.
Symptoms of a Bad AC Capacitor: What Your Body Feels
Symptoms of a bad AC capacitor, translated into what the body physically experiences, follow a predictable progression from mild discomfort to medical emergency as indoor temperature rises.
The earliest physical symptoms are non-specific. Feeling warmer than usual, mild fatigue, and mild headache are the body’s first detectable signals that core temperature is beginning to rise above normal baseline. Core body temperature in healthy adults is maintained between 36.5°C and 37.5°C (97.7°F to 99.5°F) by the hypothalamic thermoregulatory system. When ambient heat load exceeds the system’s dissipation capacity, core temperature begins to climb.
The headache that many people notice first is produced by two mechanisms. Cutaneous vasodilation, the widening of blood vessels in the skin to carry heat outward, slightly reduces blood pressure. The brain responds to reduced perfusion pressure with a dull, throbbing headache similar in character to a dehydration headache. Heat also directly affects the cerebral vasculature, causing mild vasodilation that increases intracranial pressure slightly.
Physical symptoms in the order they typically appear during indoor heat exposure from AC failure:
- Feeling warmer than the room temperature would seem to justify
- Increased sweating on the forehead, neck, and torso
- Mild to moderate headache with a throbbing character
- Fatigue disproportionate to activity level
- Nausea without vomiting in many cases
- Muscle heaviness, particularly in the legs
- Reduced concentration and mild cognitive slowing
- Pale or flushed skin, depending on hydration status and cardiovascular response
- Increased thirst, dry mouth, and reduced urine output
Pregnant women experience these symptoms at lower indoor temperatures than non-pregnant adults, because pregnancy increases basal metabolic rate by approximately 15-20% per data from the National Institutes of Health’s National Institute of Child Health and Human Development (NICHD). This elevated heat production, combined with the cardiovascular demands of pregnancy, means a pregnant woman in a home with a failing AC system reaches heat stress thresholds faster than other adults in the same space.
Bad Capacitor Symptoms and Indoor Heat Warning Signs
Bad capacitor symptoms, when recognized early, provide a practical opportunity to take protective action before health consequences escalate.
The key indoor heat warning signs that tell you the environment has become medically unsafe include a room temperature above 90°F (32°C), a relative humidity above 60% (which prevents sweat from evaporating efficiently), and the observation that a fan is circulating warm air without providing any cooling sensation. None of these signs require a thermometer or special equipment to recognize, though having a simple indoor thermometer is the most reliable way to track the risk level accurately.
The National Weather Service heat index scale, which factors both temperature and humidity, is the standard tool for assessing heat danger. An indoor environment with 95°F temperature and 50% humidity has a heat index of approximately 107°F, which the NWS classifies as “danger” level where heat stroke is possible with prolonged exposure.
Warning signs that the indoor environment has crossed from uncomfortable to hazardous:
- The room feels hotter than outdoor temperature
- Fans provide no cooling relief because the air they circulate is warmer than skin temperature
- Metal surfaces (door handles, window frames) feel warm to the touch
- Pets are seeking the lowest points of the home or are panting heavily without recent exercise
- Plants are wilting in an air-conditioned room that now has no cooling
Men tend to sweat at higher rates than women per research published in the Journal of Applied Physiology, which can make men appear more visibly distressed in heat while actually tolerating the exposure longer. Women with lower sweat rates may have less obvious external signs of heat stress while still experiencing rising core temperatures. This sex-based difference means that external sweating alone is not a reliable indicator of who is at greater health risk in a hot home.
Key Takeaway: When indoor temperature exceeds 90°F with humidity above 60%, the environment has moved from uncomfortable to medically hazardous, and vulnerable household members need to be moved to a cooled space immediately.
AC Capacitor Failure Symptoms and Heat-Related Illness
AC capacitor failure symptoms, in the health context, represent the beginning of a clinical exposure event that can produce one of four recognized heat-related illness syndromes: heat cramps, heat syncope, heat exhaustion, or heat stroke, each with distinct physiological mechanisms.
These four conditions exist on a continuum of severity. They are defined by the CDC and codified in the International Classification of Diseases (ICD-10) under category T67 (effects of heat and light). Understanding which syndrome is occurring in a household member when AC has failed is the single most practically important clinical question, because it determines whether home management is appropriate or whether 911 must be called immediately.
The four heat illness syndromes produced by indoor heat exposure from AC failure:
| Syndrome | Core Temp | Key Features | ICD-10 | Action |
|---|---|---|---|---|
| Heat cramps | Normal | Painful muscle spasms, heavy sweating | T67.2 | Rest, oral fluids, electrolytes |
| Heat syncope | Normal or mildly elevated | Brief loss of consciousness, dizziness | T67.1 | Lie flat, cool area, oral fluids |
| Heat exhaustion | Up to 40°C (104°F) | Heavy sweating, weakness, nausea, pale skin | T67.3-T67.5 | Cool environment, oral or IV fluids |
| Heat stroke | Above 40°C (104°F) | Altered mental status, hot skin, potential organ failure | T67.0 | Call 911 immediately |
People with congestive heart failure face a particularly elevated risk during AC failure because their hearts already operate with reduced reserve capacity. The cardiovascular demand of heat dissipation, which requires significantly increased cardiac output to perfuse dilated skin vessels, can exceed the failing heart’s capacity and trigger acute decompensated heart failure in addition to heat illness. This population should be evacuated to a cooled environment before heat illness symptoms develop, not after.
Heat Exhaustion Symptoms When Your AC Fails
Heat exhaustion symptoms when your AC fails represent the most commonly encountered moderate-severity heat illness syndrome and the clinical stage at which prompt action can prevent progression to the life-threatening emergency of heat stroke.
Heat exhaustion occurs when the cardiovascular system cannot maintain adequate circulation to both the skin (for cooling) and the brain and muscles (for function) simultaneously. Core body temperature in heat exhaustion is elevated but remains below 40°C (104°F). Mental status is intact or only mildly affected. This is the key clinical distinction from heat stroke, which requires a different and more urgent response.
Physically, heat exhaustion produces a recognizable constellation of symptoms. Heavy, persistent sweating is present because the eccrine sweat gland system is still functioning, unlike in classic heat stroke where sweating can be absent. The skin is typically pale or ashen rather than deeply flushed, because the cardiovascular system is struggling to maintain blood pressure. Nausea and vomiting are present in a proportion of cases.
Symptoms of heat exhaustion to recognize when AC has failed:
- Heavy, continuous sweating that persists even at rest
- Weak or rapid pulse, typically above 100 beats per minute
- Pale, cool, and moist skin (despite the hot environment, reduced blood pressure produces pale appearance)
- Nausea, with or without vomiting
- Muscle weakness, particularly in the legs
- Dizziness or lightheadedness, especially when standing
- Headache that is moderate to severe
- Fainting or near-fainting when changing position
According to the Mayo Clinic, heat exhaustion that is not treated with removal to a cooled environment and adequate rehydration can progress to heat stroke within minutes to hours. This progression is not predictable, and the rate depends heavily on the person’s cardiovascular reserve, hydration status, and whether they continue to be exposed to the hot environment.
Heat Stroke Warning Signs From Indoor Overheating
Heat stroke warning signs from indoor overheating represent a medical emergency that requires immediate 911 activation, not home treatment or a wait-and-see approach.
Heat stroke is defined clinically as a core body temperature at or above 40°C (104°F) combined with central nervous system dysfunction. The CNS dysfunction is the defining feature that separates heat stroke from heat exhaustion. It can present as confusion, slurred speech, agitation, combativeness, loss of coordination, seizure, or loss of consciousness. Any of these neurological signs in the context of heat exposure require emergency response without exception.
There are two subtypes of heat stroke, both of which can occur in a hot home. Classic heat stroke occurs in people at rest in a hot environment, making it the type most directly relevant to AC failure situations. It disproportionately affects older adults, people with chronic illness, and people on certain medications. Exertional heat stroke occurs during physical activity in heat and is more common in younger, otherwise healthy individuals who are physically active indoors in an un-air-conditioned space.
In classic heat stroke from indoor overheating, the skin is often hot and dry because the eccrine sweat gland system has failed, unlike the wet skin of heat exhaustion. This hot-dry skin finding is a classic clinical warning sign. However, the American College of Emergency Physicians notes that some heat stroke patients, particularly those with exertional heat stroke, may still be sweating when they arrive for emergency evaluation. The presence of sweating does not rule out heat stroke if other signs are present.
Warning signs of heat stroke in a home with failed AC:
- Confusion, disorientation, or speaking incoherently
- Agitation, combativeness, or unusual behavior
- Loss of muscle coordination, stumbling gait, or inability to walk normally
- Hot skin that may be dry or still wet
- Very rapid heart rate (tachycardia above 130 beats per minute in many cases)
- Loss of consciousness or unresponsiveness
- Seizure activity
Key Takeaway: If anyone in a home without cooling shows signs of confusion, loss of coordination, or altered behavior during hot weather, treat this as heat stroke and call 911 immediately; do not attempt to manage this at home.
Heat Syncope and Heat Cramps: Recognizing Early Symptoms
Heat syncope and heat cramps are the two earliest and mildest recognized heat illness syndromes, but they are not benign: both indicate that the body’s thermoregulatory and cardiovascular systems are already under physiological stress.
Heat syncope is a brief loss of consciousness or near-fainting episode caused by the pooling of blood in the dilated peripheral blood vessels during heat exposure. When the body redirects blood flow toward the skin to dissipate heat, venous return to the heart decreases. If the person stands up quickly or remains standing without moving (which normally pumps blood back to the heart through the calf muscle pump), blood pressure drops enough to reduce cerebral perfusion, causing syncope. The person typically recovers quickly once lying flat.
Heat syncope is most likely to occur in people who have been standing in a hot environment without moving, such as someone standing in a kitchen or laundry room while the AC has failed on a hot day. It is more common in people who are already mildly dehydrated, because reduced blood volume amplifies the effect of peripheral vasodilation on blood pressure. Older adults with baseline low blood pressure or those taking antihypertensive medications are at higher risk of heat syncope at lower heat exposures than younger, healthy adults.
Heat cramps are painful, involuntary muscle spasms that occur in heavily exercised or heated muscles, most often the calves, thighs, and abdomen. They result from the combined effect of sweat-related electrolyte loss, particularly sodium and chloride, and muscle fatigue from sustained activity in a hot environment. Drinking large amounts of plain water without replacing electrolytes can actually worsen heat cramps by further diluting remaining sodium.
To recognize and respond to heat syncope:
- Note whether the person briefly lost consciousness or felt they were about to faint in a hot environment
- Have them lie flat with their legs elevated slightly to restore cerebral blood flow
- Move them to the coolest available area and provide oral fluids with electrolytes
- Monitor for any confusion, persistent altered consciousness, or high fever, which would indicate progression beyond syncope
- If the person does not recover fully within 15 minutes of lying flat and cooling, call 911
How the Body Regulates Temperature and When It Fails
The body regulates temperature through a precisely coordinated system centered in the hypothalamus, and understanding how this system works makes it clear why AC failure creates a genuine physiological crisis for certain people.
The preoptic nucleus of the hypothalamus serves as the body’s thermostat. Thermosensitive neurons in this structure continuously monitor blood temperature as it circulates through the brain. When blood temperature rises even slightly above baseline, these neurons fire signals through the autonomic nervous system to activate heat-dissipation responses. The two primary responses are eccrine sweat gland activation and cutaneous vasodilation.
Eccrine sweat glands are distributed across the entire skin surface, with the highest density on the palms, soles, forehead, and axillae. They are activated by sympathetic cholinergic nerve fibers: sympathetic in origin (part of the fight-or-flight system) but using acetylcholine as the neurotransmitter rather than norepinephrine. When these fibers fire, the glands produce sweat, which evaporates from the skin surface and carries heat away. An adult producing sweat at maximum rate can dissipate approximately 600 to 700 kilocalories of heat per hour through evaporation alone.
The second response, cutaneous vasodilation, redirects blood flow from the body’s core to the skin surface. Blood carries heat from the metabolically active core tissues to the skin, where it radiates and convects into the surrounding air. This process requires the heart to increase its output substantially: cardiac output can increase by 3 to 4 liters per minute per degree Celsius of core temperature rise during heat stress.
The system fails when:
- Ambient temperature exceeds skin temperature, eliminating the gradient for radiation and convection
- Humidity exceeds approximately 75-80%, preventing sweat evaporation
- The cardiovascular system cannot sustain the increased cardiac output demand
- Dehydration reduces sweat production below the level needed for adequate cooling
- Medications or disease states impair sweat gland function or cardiovascular response
According to the National Institute for Occupational Safety and Health (NIOSH), the combination of high temperature and high humidity is more dangerous than either factor alone because it simultaneously eliminates two of the body’s four heat dissipation pathways (evaporation and convection), leaving only radiation and conduction as options.
Cardiovascular Effects of Indoor Heat Exposure From AC Failure
Cardiovascular effects of indoor heat exposure from AC failure are among the most clinically serious consequences because the heart must dramatically increase its workload to support both normal organ perfusion and the additional demands of heat dissipation through the skin.
During heat stress, the cardiovascular system faces a specific physiological conflict. The body needs to redirect a large portion of cardiac output, up to 8 liters per minute at high heat loads, to the dilated cutaneous blood vessels for heat dissipation. Simultaneously, it must maintain adequate blood flow to the brain, kidneys, liver, and skeletal muscle. The heart meets this demand primarily by increasing heart rate, since stroke volume is often reduced by the dehydration-related decrease in blood volume.
For people with healthy hearts and normal blood volume, this increased cardiac demand is manageable for hours to days. For people with coronary artery disease, congestive heart failure, valvular heart disease, or cardiac arrhythmias, the additional workload of heat stress can trigger acute cardiac events. Research published in Circulation, the journal of the American Heart Association, has documented elevated rates of acute myocardial infarction and arrhythmia events during heat waves, with indoor temperature being an independent risk factor.
Cardiovascular symptoms that can develop during indoor heat exposure:
- Rapid or pounding heartbeat (palpitations) that persists even at rest
- Shortness of breath on minimal exertion or at rest (suggests cardiac decompensation)
- Chest tightness or pressure (warrants immediate evaluation regardless of heat context)
- Ankle or foot swelling worsening over hours (suggests volume overload in a heart failure patient)
- Unusually low blood pressure readings in a person who normally has controlled hypertension
People taking beta-blockers face a specific cardiovascular risk during heat exposure. Beta-blockers limit the heart’s ability to increase rate in response to demand. Because tachycardia is one of the primary mechanisms by which the heart increases output during heat stress, beta-blockers blunt this response, reducing the cardiovascular system’s ability to sustain heat dissipation. This does not mean people should stop taking beta-blockers during hot weather; it means they should be monitored more carefully and prioritized for cooling when AC fails.
Elderly and Infant Heat Illness Risk When AC Stops Working
Elderly adults and infants face disproportionately high health risk when AC stops working because both groups have impaired thermoregulatory physiology that differs fundamentally from healthy young adults.
Adults over age 65 have measurably reduced eccrine sweat gland function. Research published in the Journal of Applied Physiology has shown that older adults begin sweating at higher core temperatures than younger adults, meaning their thermoregulatory cooling response activates later and produces less sweat per gland. They also have reduced cardiac output reserve, reduced blood volume, diminished thirst perception (increasing dehydration risk), and a higher prevalence of chronic conditions and medications that further impair heat tolerance.
The CDC reports that adults over age 65 account for the majority of heat-related deaths in the United States during heat events. In many of these cases, the death occurred indoors in a home with non-functional air conditioning.
Infants under 12 months present a different set of physiological vulnerabilities. The eccrine sweat gland system is anatomically present at birth but functionally immature. Sweat gland secretory capacity in newborns is approximately one third of the adult capacity per unit area, per research in the journal Pediatrics. Infants also have a higher surface-area-to-volume ratio than adults, which causes faster heat gain from a hot environment. They are completely dependent on caregivers for hydration and cooling.
Warning signs of heat illness in infants when AC has failed:
- Skin that is hot and red or hot and dry (normal infant skin in heat should be warm and moist with sweating)
- Rapid breathing not explained by activity or crying
- Unusual listlessness, poor feeding, or difficulty waking
- Fontanelle (soft spot on top of head) appears sunken (dehydration) or, less commonly, bulging
- Urine output decreased: fewer than 4-6 wet diapers in 24 hours in a hot environment
- Rectal temperature above 38°C (100.4°F) in an infant under 3 months, or above 39°C (102.2°F) in an infant 3-12 months, in the context of heat exposure
Any of these signs in an infant warrant immediate contact with a pediatrician or pediatric emergency medicine physician. Fever with heat exposure in infants under 3 months requires emergency room evaluation the same day.
Key Takeaway: Adults over 65 and infants under 12 months are at the highest risk of rapid health deterioration when AC fails because their thermoregulatory physiology is inherently limited, and standard signs of heat stress may appear later or differently than in healthy young adults.
Medications That Increase Heat Sensitivity in a Hot Home
Certain medications significantly impair the body’s ability to tolerate heat, and people taking these drugs are at elevated risk of heat illness when an AC system fails, even in conditions that would not threaten a healthy adult.
The most clinically important drug classes affecting heat tolerance are anticholinergics, beta-blockers, diuretics, antipsychotics, and stimulant medications. Each affects a different part of the thermoregulatory or cardiovascular response to heat, and their effects are additive when a person is taking more than one.
Anticholinergic medications block the muscarinic acetylcholine receptors that activate eccrine sweat glands. Because sweating is the body’s primary heat dissipation mechanism in hot environments, blocking it can cause core temperature to rise rapidly even without extreme outdoor temperatures. Drugs with significant anticholinergic activity include certain antihistamines (diphenhydramine), some bladder medications (oxybutynin, tolterodine), certain antidepressants (tricyclic antidepressants such as amitriptyline and nortriptyline), some antiparkinson medications, and certain antipsychotics (clozapine, olanzapine, quetiapine).
Diuretics, prescribed for high blood pressure, heart failure, and certain kidney conditions, reduce blood volume as part of their mechanism. Reduced baseline blood volume means the cardiovascular system has less reserve capacity to support both organ perfusion and cutaneous vasodilation during heat stress. People on diuretics reach dehydration thresholds faster during heat exposure.
Medications that require heightened monitoring when AC fails:
- Anticholinergics: reduce or eliminate sweating, raising core temperature rapidly
- Beta-blockers: limit compensatory tachycardia, reducing cardiovascular heat-response capacity
- Diuretics: reduce blood volume baseline, accelerating dehydration during heat stress
- Antipsychotics: impair hypothalamic thermoregulation and may increase muscular heat production
- Lithium: toxicity risk rises when dehydration occurs, which is more likely in heat
- Stimulants (methylphenidate, amphetamines): increase metabolic heat production
- Tricyclic antidepressants: combine anticholinergic effects with cardiovascular effects
People taking any of these medications should prioritize relocation to a cooled environment before heat symptoms develop when AC fails, not after. A primary care physician or clinical pharmacist can review a specific medication list and clarify which agents carry the highest heat-risk profile for a given patient.
Diabetes and Heat Illness Risk From AC Capacitor Failure
Diabetes increases the risk of heat illness from AC failure through two distinct pathways: diabetic autonomic neuropathy, which impairs the sweating response, and microvascular disease, which reduces the efficiency of skin-level heat transfer.
Diabetic autonomic neuropathy (DAN) affects the autonomic nerve fibers that regulate multiple body functions, including the sympathetic cholinergic fibers that innervate eccrine sweat glands. The National Institute of Neurological Disorders and Stroke (NINDS) describes sudomotor dysfunction as one of the earliest detectable features of diabetic autonomic neuropathy. People with DAN may have reduced sweating (hypohidrosis) or absent sweating (anhidrosis) in the feet and lower legs, the areas where autonomic nerve damage typically begins. In severe cases, the impairment extends to the trunk and upper body.
A person with diabetic sudomotor neuropathy operating in a hot home without AC cannot rely on sweat evaporation as a cooling mechanism in the affected body regions. The skin in those areas remains dry even as core temperature rises, eliminating a significant portion of their heat dissipation capacity. Core temperature can rise toward dangerous levels without the external visual cue of heavy sweating that would alert both the person and their caregivers to take action.
People with diabetes also face an additional risk from heat-related dehydration. Elevated blood glucose levels in poorly controlled diabetes produce an osmotic diuresis (glucose spills into urine and takes water with it), increasing baseline fluid losses even before heat-related sweating begins. When AC fails and sweating adds to these losses, dehydration can develop rapidly and may worsen glycemic control through the stress hormone response.
Quick Tip:
- People with diabetes should check blood glucose more frequently when indoor temperature is elevated, as heat stress activates the sympathetic nervous system, which can transiently raise blood glucose through epinephrine-mediated glycogenolysis
- Carry glucose monitoring supplies when relocating to a cooled environment, as glycemic control can change with the physical stress of the heat event
- People with known diabetic autonomic neuropathy should be prioritized for evacuation to cooled spaces when AC fails, because their sweating impairment removes a key clinical warning sign
According to the American Diabetes Association’s clinical standards of care, people with diabetes and autonomic neuropathy should be specifically educated about heat illness risk and should have an action plan for situations where cooling systems fail.
Heat Exhaustion vs Heat Stroke: The Critical Difference
The difference between heat exhaustion and heat stroke is the difference between a condition that can be managed with prompt home cooling measures and a life-threatening emergency that requires immediate 911 activation and hospital-level care.
Both conditions result from the body’s thermoregulatory system being overwhelmed by heat exposure. The distinction lies in the degree of core temperature elevation and whether central nervous system function is impaired. Heat exhaustion involves core temperatures below 40°C (104°F) and preserved mental status. Heat stroke involves core temperatures at or above 40°C (104°F) with central nervous system dysfunction, including confusion, ataxia, agitation, or loss of consciousness.
The practical difficulty is that core temperature is not always easily measurable at home. Oral thermometers are unreliable during heat illness because open-mouth breathing from heat stress artificially lowers oral readings. Ear (tympanic) thermometers have variable accuracy. Rectal thermometry is the clinical gold standard for heat illness assessment but is not routinely performed outside of medical settings.
| Feature | Heat Exhaustion | Heat Stroke |
|---|---|---|
| Core temperature | Below 40°C (104°F) | At or above 40°C (104°F) |
| Mental status | Normal or mildly foggy | Confused, agitated, ataxic, or unconscious |
| Skin | Pale, cool, and moist | Hot; may be dry or moist |
| Sweating | Present, often profuse | Absent in classic; may persist in exertional |
| Heart rate | Elevated (100-120 bpm typical) | Markedly elevated (often above 130 bpm) |
| Blood pressure | Low to normal | Variable; often low |
| 911 required? | No, if cooling begins immediately | Yes, always |
| Home management sufficient? | Yes, if no high-risk features | No, never |
When in doubt between these two diagnoses, always treat the situation as heat stroke and call 911. The consequences of treating heat stroke as heat exhaustion are catastrophic. The consequences of calling 911 for what turns out to be heat exhaustion are minimal. This asymmetry makes the decision straightforward.
Emergency Symptoms From Indoor Overheating: When to Call 911
Certain symptoms caused by indoor heat exposure when AC fails require immediate emergency evaluation. Do not wait to see if these resolve on their own.
Call 911 or go to the nearest emergency room immediately if anyone in the home shows:
- Confusion, disorientation, or inability to recognize familiar people or surroundings (indicates central nervous system involvement consistent with heat stroke)
- Slurred speech, loss of coordination, or stumbling gait (cerebellar and cerebral cortex dysfunction from hyperthermia)
- Loss of consciousness, even briefly, in the context of heat exposure in a person over age 65, an infant, a person with heart disease, or a person on any of the medications listed above
- Seizure activity in the context of heat exposure, at any age
- Hot skin that is dry or minimally moist in a person who appears severely ill (suggests eccrine sweat gland failure, a feature of advanced heat stroke)
- Heart rate that appears extremely rapid and the person is confused or unable to respond normally
- Chest pain or severe shortness of breath in a heat-exposed person with known heart disease
- A rectal temperature at or above 40°C (104°F) if you are able to measure it
- Any infant under 3 months with a rectal temperature above 38°C (100.4°F) in the context of heat exposure
- Any person who does not improve or who worsens within 30 minutes of being moved to a cooled environment and given oral fluids
While waiting for emergency services, move the person to the coolest available space, apply cool (not ice-cold) water to the skin, particularly the neck, armpits, and groin where large blood vessels run close to the surface, and do not give fluids by mouth to anyone who is confused or unconscious.
These presentations indicate heat stroke, acute cardiac decompensation, or severe heat-related organ injury. They require emergency medical assessment and hospital-level intervention, not urgent care and not a phone call to a physician.
When to See a Doctor After Heat Exposure From AC Failure
Knowing when to seek medical evaluation after heat exposure from AC failure prevents two outcomes that are both avoidable: undertreating a condition that progresses to permanent harm, and over-responding to temporary discomfort that resolves with rest and fluids.
For mild heat exhaustion that resolves within 30 to 60 minutes of moving to a cooled space and taking oral fluids, same-day medical evaluation is not required in otherwise healthy young adults. The exception is any person in a high-risk group: age over 65, age under 12 months, pregnancy, known cardiovascular disease, known diabetes with autonomic neuropathy, or use of any of the medications identified above. These individuals warrant contact with a primary care physician or pediatrician the same day, even if acute symptoms have resolved, because recurrence risk is high and their baseline physiology makes reassessment valuable.
Heat cramps that resolve with rest, rehydration, and electrolyte replacement do not typically require physician evaluation unless they are recurrent, severe, or occur in a person with known musculoskeletal or renal disease.
To prepare for a medical appointment after heat exposure from AC failure:
- Document the indoor temperature if known, the duration of exposure, and what outdoor temperature and humidity were during the event
- List all current medications, including over-the-counter antihistamines, as anticholinergic effects are often not recognized by patients
- Note any pre-existing conditions, particularly cardiovascular disease, diabetes, or kidney disease
- Describe the sequence of symptoms in the order they appeared and whether any have persisted after cooling and rehydration
- Note whether the person is now urinating normally (a good indicator of adequate rehydration) or has reduced urine output (suggesting dehydration requiring further evaluation)
A primary care physician evaluating post-heat-exposure symptoms may order a basic metabolic panel (BMP) to check electrolytes and kidney function, a creatine kinase (CK) level to rule out rhabdomyolysis if muscle pain or dark urine were present, and liver function tests in cases where the exposure was severe.
Key Takeaway: Healthy young adults who recover fully from mild heat exhaustion within an hour of cooling and rehydration do not typically need same-day medical evaluation; anyone in a high-risk group, or anyone whose symptoms do not fully resolve in that timeframe, does.
Frequently Asked Questions About Bad AC Capacitor Symptoms and Heat Illness
Can a bad AC capacitor make you sick?
Yes, a bad AC capacitor can contribute to heat-related illness by causing the air conditioning system to stop cooling, allowing indoor temperatures to rise to levels that exceed the body’s thermoregulatory capacity.
The illness is not caused by the capacitor itself but by the heat exposure that results from its failure, which can produce symptoms ranging from mild heat cramps to life-threatening heat stroke depending on the duration of exposure and the vulnerability of the person exposed.
The CDC identifies loss of indoor cooling as a primary risk factor for heat-related illness and death during hot weather.
What are the first signs of heat illness when your AC stops working?
The first signs of heat illness when AC stops working are feeling warmer than usual with increased sweating, mild headache with a throbbing character, unusual fatigue, and mild nausea.
These early symptoms reflect the cardiovascular and eccrine sweat gland system working at maximum capacity to prevent core temperature from rising, and they typically appear within one to three hours of exposure to indoor temperatures above 90°F depending on humidity.
Acting on these early signs by moving to a cooled environment and rehydrating with electrolyte-containing fluids can prevent progression to heat exhaustion or heat stroke.
How hot does a house have to be to get heat stroke?
There is no single indoor temperature that universally produces heat stroke, because heat stroke risk depends on temperature, humidity, duration of exposure, hydration status, and individual vulnerability.
The National Weather Service classifies a heat index (combined temperature and humidity measure) above 103°F as “danger” level where heat exhaustion is likely and heat stroke is possible with prolonged exposure, making indoor environments at or above this index value the threshold of serious concern.
Vulnerable individuals, including older adults, infants, and people with cardiovascular disease or diabetes, can develop heat stroke at lower heat index values and after shorter exposure durations than healthy young adults.
What is the difference between heat exhaustion and heat stroke?
Heat exhaustion involves core body temperature below 40°C (104°F) with preserved mental status, heavy sweating, pale moist skin, and symptoms of cardiovascular stress like dizziness and nausea.
Heat stroke is defined by core temperature at or above 40°C (104°F) combined with central nervous system dysfunction, which can appear as confusion, agitation, loss of coordination, seizure, or unconsciousness.
Heat exhaustion can often be managed by moving to a cooled environment and rehydrating; heat stroke always requires immediate 911 activation because it is a life-threatening emergency requiring hospital-level intervention.
Who is most at risk for heat illness when air conditioning fails?
Adults over age 65, infants under 12 months, pregnant women, people with cardiovascular disease, and people with diabetes with autonomic neuropathy are at highest risk of heat illness when AC fails.
People taking anticholinergic medications, diuretics, beta-blockers, antipsychotics, or lithium face additional risk because these drugs impair specific components of the body’s heat tolerance mechanisms.
The CDC reports that adults over age 65 account for the majority of heat-related deaths in the United States, most of which occur indoors.
When should I go to the emergency room for heat exposure symptoms?
Go to the emergency room immediately or call 911 if heat exposure has produced confusion, loss of coordination, seizure, loss of consciousness, or hot dry skin in any person.
Any infant under 3 months with a rectal temperature above 38°C (100.4°F) in a heat exposure context requires emergency room evaluation the same day without waiting to monitor at home.
Symptoms that do not resolve within 30 to 60 minutes of moving to a cooled environment and rehydrating, or any worsening after initial improvement, also require emergency evaluation regardless of age.
Closing
When an AC capacitor fails during hot weather, the mechanical problem becomes a health problem quickly, and the timeline depends heavily on who is in the home. Recognizing the progression from heat discomfort to heat exhaustion to heat stroke is the most important thing you can do to protect yourself and anyone in your household.
If you or someone in your home is showing symptoms beyond mild sweating and fatigue after AC failure, move to a cooled space immediately, use electrolyte-containing fluids rather than plain water, and monitor for any sign of confusion, loss of coordination, or unresponsiveness. Those signs require 911, not home treatment.
Your primary care physician can review your specific medications and medical history to tell you exactly which heat illness risk category you fall into and what your action plan should be before the next heat event. Make that conversation happen before the next capacitor fails.