Symptoms of Ear Tubes Falling Out: Complete 2026 Guide
The most common symptoms of ear tubes falling out include a return of ear fullness or muffled hearing, a change in the amount or appearance of ear drainage, and occasionally the visible presence of a small metallic or plastic object in the outer ear canal or on a pillow. In most cases, these symptoms indicate the tube is naturally working its way out as expected, not that something has gone wrong.
According to the American Academy of Otolaryngology-Head and Neck Surgery (AAO-HNS), tympanostomy tubes are intentionally designed to be temporary. The AAO-HNS Clinical Practice Guideline on Tympanostomy Tubes in Children, updated to reflect current clinical evidence, confirms that natural tube extrusion is the desired and expected outcome for most short-acting tubes placed in children. Recognizing the difference between normal extrusion and a tube-related complication can prevent unnecessary anxiety or, in some cases, a missed warning sign.
This article explains exactly what the symptoms of ear tubes falling out look like, why they occur at the anatomical level, what drainage patterns are expected versus worrying, how extrusion differs in adults and children with specific health conditions, and precisely when you need to contact an ENT specialist or go to the emergency room.
Symptoms of Ear Tubes Falling Out
The primary symptoms of ear tubes falling out are muffled hearing on the affected side, a sense of ear fullness or pressure, and a visible small cylinder or ring-shaped object in the outer ear canal or on a pillow or towel. These symptoms may appear gradually over days or more abruptly depending on the tube’s position during extrusion.
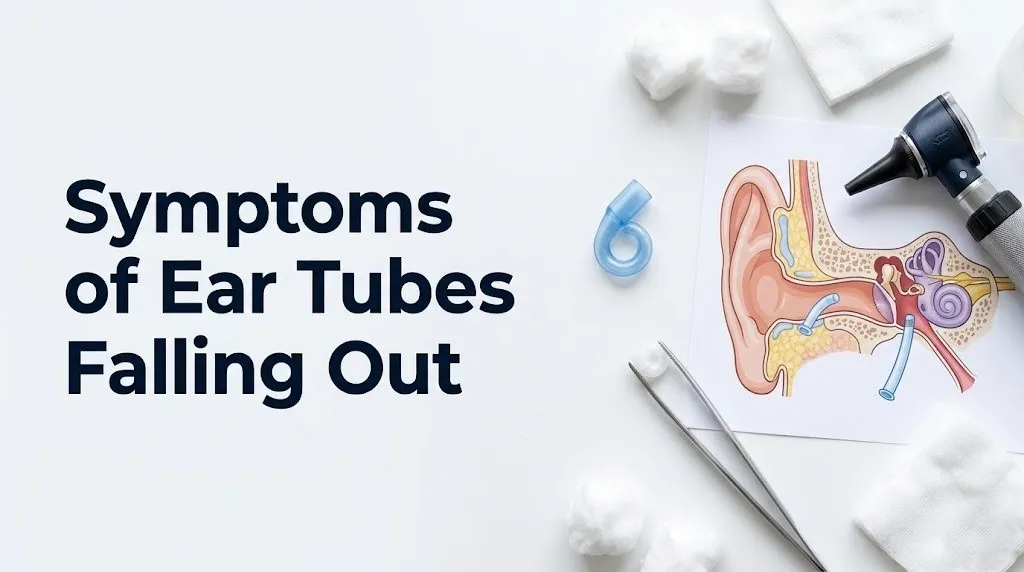
The tympanic membrane, the structure most people call the eardrum, does not simply release the tube passively. The surface of the tympanic membrane is covered by a specialized layer of squamous epithelium that migrates laterally at roughly 0.05 to 0.1 mm per day from the central attachment point called the umbo outward toward the bony ring called the annulus fibrosus. This biological movement, called lateral epithelial migration, is the actual mechanism that carries the tube from its placement site toward the outer ear canal. Think of the tympanic membrane surface like a very slow conveyor belt, always moving outward. The tube is simply a passenger.
As the tube approaches the outer canal, the child or adult may notice a change in how their ear feels before the tube becomes visible. The shift in hearing can be subtle at first, presenting as a slight “cottonball” sensation, or more noticeable if the tube was providing significant pressure equalization.
Key symptoms to recognize:
- Muffled hearing or a return of the “underwater” sound quality experienced before tube placement
- A feeling of pressure or fullness inside the ear
- A small metallic, silver, or flesh-colored cylinder visible in the opening of the ear canal
- Finding the tube on a pillow, in a towel, or in the outer ear after sleeping
- A slight cracking or popping sensation in the ear as the tube shifts position
- A brief episode of clear or slightly yellowish drainage as the tube exits
For children who are not yet verbal, parents may notice them tugging at the affected ear, appearing less responsive to sound, or turning one ear toward sound sources more than before.
What Happens When Ear Tubes Come Out
When an ear tube comes out, the small opening created in the pars tensa of the tympanic membrane during the original myringotomy procedure closes spontaneously in the vast majority of cases. The tympanic membrane has a strong capacity for self-repair because the epithelial cells surrounding the perforation migrate inward from the edges to seal the opening, typically within days to weeks.
A 2022 systematic review published in Otolaryngology-Head and Neck Surgery found that spontaneous closure of the tympanic membrane occurs in approximately 97% of patients following short-acting tube extrusion when no complicating infection or retained tube fragment is present. The remaining 3% may develop a persistent perforation, a finding that warrants formal audiological evaluation and ENT follow-up.
What the body does after tube extrusion depends on whether the underlying Eustachian tube dysfunction that originally required tube placement has resolved. If Eustachian tube function has normalized, the middle ear maintains appropriate pressure and fluid drainage without assistance, and no further intervention is needed. If Eustachian tube dysfunction persists, middle ear fluid can begin to re-accumulate within weeks to months, leading to a return of the symptoms that prompted tube placement initially.
The transition period immediately after extrusion can feel strange. The ear may feel more sensitive to pressure changes, such as altitude changes during travel or even elevation changes during driving, because the ventilating function the tube was providing has ended. This pressure sensitivity is normal and typically resolves as the tympanic membrane repairs itself and Eustachian tube function adapts.
The NIDCD reports that approximately 30% of children will need a second set of ear tubes after the first set extrudes, with higher rates in children with persistent Eustachian tube dysfunction or specific anatomical risk factors.
How Long Do Ear Tubes Stay In
Short-acting tympanostomy tubes, the type most commonly placed in children during a standard myringotomy procedure, typically stay in place for 6 to 15 months before natural extrusion occurs. Long-acting tubes, often called T-tubes or flanged tubes, are designed to remain in place for 2 to 4 years and may require surgical removal rather than falling out naturally.
| Tube Type | Average Retention Time | Extrusion Method | Common Use |
|---|---|---|---|
| Short-acting (grommet/bobbin) | 6 to 15 months | Natural lateral epithelial migration | Recurrent acute otitis media, children |
| Intermediate (extended-duration) | 14 to 24 months | Natural extrusion, occasionally surgical | Persistent middle ear effusion |
| Long-acting (T-tube, flanged) | 2 to 4 years or longer | Usually surgical removal required | Craniofacial conditions, adults, chronic Eustachian tube dysfunction |
| Silicone or fluoroplastic tube variants | Variable; 12 to 36 months | Variable; depends on flange design | Varied clinical contexts |
The tube type selected by the otolaryngologist at the time of surgery influences not only how long the tube stays in but also how the extrusion happens. Grommet or bobbin tubes, which account for the majority of pediatric tube placements, extrude along the natural epithelial migration pathway without intervention. Long-acting T-tubes have a wider flange that anchors more firmly through the tympanic membrane and cannot extrude along this pathway without tissue stretching or deliberate surgical removal.
Parents of children with short-acting tubes can generally expect to start noticing extrusion-related symptoms somewhere between 9 and 12 months after placement, though significant variation exists. A child who had frequent ear infections before tube placement, or who develops otitis media through the tube post-placement, may experience faster extrusion due to accelerated inflammation-driven epithelial activity.
Key Takeaway: Natural tube extrusion is driven by the tympanic membrane’s built-in epithelial migration mechanism, and most short-acting tubes exit on their own within 6 to 15 months without any intervention needed.
Signs Ear Tubes Have Fallen Out
Confirmed signs that an ear tube has fallen out include finding the physical tube outside the ear, visualization of the tube in the outer ear canal during examination with an otoscope, a documented return of hearing threshold shift on a follow-up audiogram, and a tympanogram showing altered middle ear pressure consistent with a sealed or scarred tympanic membrane without tube patency.
At home, the clearest sign is finding the tube itself. Tubes are small, roughly 1 to 3 millimeters in diameter, and may look like a tiny metallic or translucent plastic spool, a small ring, or a short cylindrical piece. Parents sometimes discover them in a child’s ear during bath time, on a pillow after sleep, or in a towel after the ear has been dried.
Signs that are less obvious but clinically meaningful:
- A return of the hearing difficulty, ear fullness, or speech delay that prompted the original tube placement
- New or worsening episodes of acute otitis media, particularly in a child who had been infection-free while tubes were in place
- A subtle change in the child’s behavior, including increased inattention, louder TV volume, or asking for sounds to be repeated more often
- Tympanogram results at a follow-up appointment showing a Type B (flat) or Type C (negative pressure) curve instead of the normal Type A curve, indicating middle ear effusion or pressure imbalance
It is worth noting that hearing changes after tube extrusion are not always dramatic. If Eustachian tube function has improved naturally during the period the tube was in place, hearing may remain essentially normal even after the tube exits. For these children, the tube falling out is a non-event. This is the best-case scenario and occurs in a meaningful proportion of children, particularly those whose otitis media was linked to transient upper respiratory tract infections in early childhood rather than persistent structural Eustachian tube dysfunction.
Ear Drainage After Tubes Fall Out
Ear drainage, called otorrhea, during or immediately after tube extrusion is not automatically a sign of infection. A small amount of clear to slightly yellowish, odorless drainage during the final days of tube extrusion is a normal finding produced by the middle ear mucosa as the tube exits.
What produces this drainage is straightforward physiology. The middle ear space is lined by ciliated columnar epithelium that produces mucus continuously as part of normal mucociliary clearance. As long as the tube is in place, this mucus can drain outward through the tube lumen into the external auditory canal. During the extrusion process, the tube’s angle shifts, and mucus that would normally drain through the tube lumen may instead track around the tube’s outer surface as it moves through the canal.
This type of drainage:
- Is clear, pale yellow, or slightly milky in color
- Has no odor
- Appears in small quantities, typically just enough to notice on a cotton ball or ear pillow
- Resolves within 24 to 72 hours as the tube fully exits and the tympanic membrane begins closing
The drainage becomes clinically concerning and warrants same-day ENT contact if it meets any of these characteristics:
- Yellow-green or frankly purulent (pus-like) in color
- Foul-smelling
- Persisting beyond 72 to 96 hours without improvement
- Accompanied by ear pain, fever, or tenderness behind the ear
- Present in notably high volume, such as visibly soaking a pillow or requiring repeated cotton ball changes
According to a clinical review published in Otology and Neurotology, tube-associated otorrhea occurring at the time of extrusion is distinct from otorrhea caused by active otitis media through a patent tube, and the two should not be treated the same way. Post-extrusion drainage that resolves quickly without antibiotic intervention is consistent with normal mucosal activity, not active infection.
Ear Pain After a Tube Falls Out
Ear pain after a tube falls out, called otalgia, is not a universal finding. Most natural, gradual tube extrusions cause little to no pain because the lateral epithelial migration moves the tube slowly enough that the tympanic membrane has time to adapt without acute stretching or pressure changes.
When pain does occur in the setting of tube extrusion, it is most commonly produced by one of three distinct mechanisms. The first is inflammatory otalgia from a concurrent or early acute otitis media recurrence, where bacteria re-establish themselves in the middle ear space after the tube’s protective ventilation effect ends. The second is referred otalgia from the external auditory canal itself, where a tube that is partially expelled but not yet fully out creates localized pressure or mild abrasion against the canal skin. The third, less commonly, is otalgia from a small residual perforation in the tympanic membrane that responds to air pressure fluctuations with discomfort.
The Mayo Clinic notes that mild, transient ear discomfort during the final phase of tube movement is generally not concerning if it resolves within 24 to 48 hours and is not accompanied by fever, purulent drainage, or significant hearing change.
Pain that does warrant prompt ENT evaluation:
- Pain rated as moderate to severe (not just a pressure sensation) persisting beyond 48 hours
- Pain accompanied by fever of 38 degrees Celsius or higher
- Pain in a child who is inconsolably crying, not sleeping, or refusing to eat
- Pain with visible redness, swelling, or warmth behind the ear (postauricular region), which suggests mastoiditis rather than simple otitis media recurrence
- Sudden sharp pain followed by a pop and then drainage, which can indicate spontaneous tympanic membrane perforation unrelated to the tube extrusion
Children under age two deserve particular attention here. Otalgia in this age group is frequently expressed as behavioral changes rather than verbal complaint: unusual irritability, sleep disruption, and reaching or rubbing at the affected ear. A behavioral change pattern like this persisting more than 24 to 48 hours after a suspected extrusion event warrants a phone call to the child’s pediatrician or otolaryngologist rather than watchful waiting.
Key Takeaway: Mild, brief ear pressure or discomfort during tube extrusion is expected, but pain lasting more than 48 hours, accompanied by fever or postauricular swelling, requires same-day evaluation by an otolaryngologist or pediatrician.
Hearing Loss After Ear Tubes Fall Out
A return of muffled or reduced hearing after ear tube extrusion reflects the restoration of the normal middle ear physiology that was bypassed while the tube was in place, and it is one of the most reliably reported patient-reported symptoms when tubes fall out. The hearing change is conductive in nature, meaning it results from impaired sound transmission through the outer and middle ear structures rather than damage to the cochlea or the auditory nerve.
The physics of this hearing change are direct. While a tympanostomy tube is in place, sound waves pass through the tube lumen, bypassing the need for the tympanic membrane to vibrate efficiently. Once the tube exits and the perforation closes, all sound transmission must occur through the tympanic membrane again. If middle ear effusion re-accumulates, the effusion dampens tympanic membrane vibration, reducing the mechanical energy transferred to the ossicular chain (the malleus, incus, and stapes), and producing a conductive hearing loss typically in the range of 20 to 40 decibels across speech frequencies.
According to data summarized by the National Institute on Deafness and Other Communication Disorders (NIDCD), children with persistent middle ear effusion commonly experience hearing thresholds 25 decibels or more below normal across the 500 Hz to 4000 Hz speech frequency range, the range most relevant to language acquisition and classroom listening.
What parents and caregivers can observe at home:
- The child increases television or device volume progressively
- The child begins asking “what?” more frequently or requires closer proximity for conversation
- Speech that had improved while tubes were in place begins sounding less clear or articulated
- In a quiet environment, the child seems fine, but noisy environments (classrooms, group play) produce noticeably more difficulty
Not all hearing change after extrusion represents new effusion. Some transient hearing dip can occur simply because the tympanic membrane takes days to weeks to fully re-seal and optimize its mechanical properties. For this reason, a post-extrusion audiogram is typically recommended by otolaryngologists approximately 4 to 6 weeks after confirmed tube loss to establish an accurate baseline hearing threshold.
Can You See the Ear Tube When It Falls Out
Yes, in many cases you can see the ear tube when it falls out, and finding the tube outside the ear is considered the clearest confirmation that extrusion has occurred. Tubes are small enough to be missed easily, which is why parents are sometimes advised to check their child’s pillow, ear canal opening, and bed linens after sleep.
What the tube looks like depends on the type placed during surgery. Most short-acting pediatric tubes (grommets or bobbins) are 1 to 1.5 millimeters in internal diameter and about 1 to 2 millimeters in length. They appear as:
- A tiny silver or gold metallic ring or spool (for stainless steel or titanium tubes)
- A small translucent or off-white plastic cylinder (for polyethylene or fluoroplastic tubes)
- Occasionally encrusted with dried cerumen or a thin film of dried mucus, making them appear beige or brownish
Numbered steps for what to do if you find your child’s ear tube:
- Pick up the tube carefully with clean fingers or tweezers and place it in a small sealed plastic bag or container.
- Note the date and which ear it came from (left or right).
- Check the child’s ear canal visually with a penlight if available. A tube fully out of the canal leaves the ear opening looking normal.
- Contact your child’s otolaryngologist’s office to report the extrusion and confirm the next follow-up appointment timeline.
- Bring the tube to the follow-up appointment if possible. The otolaryngologist may wish to examine it for signs of blockage, biofilm, or structural change.
- Do not attempt to reinsert the tube or push it further into the ear if it is partially visible in the canal.
If you cannot find the tube but suspect it has come out, this does not require an emergency visit. Partial tubes or tube fragments can sometimes remain in the ear canal or, less commonly, in the middle ear. This warrants a scheduled otoscopic examination rather than urgent care unless other concerning symptoms are present.
Normal vs. Abnormal Ear Tube Drainage
Normal ear tube drainage during extrusion is clear to pale yellow, odorless, appears in small quantities, and resolves within one to three days without treatment. Abnormal drainage is purulent, foul-smelling, high in volume, or persistent, and indicates an active middle ear infection rather than simple extrusion-related mucosal discharge.
| Drainage Feature | Normal Extrusion Drainage | Abnormal Drainage (Infection Likely) |
|---|---|---|
| Color | Clear, pale yellow, slightly milky | Yellow-green, dark yellow, brown, bloody |
| Odor | Odorless or very faint | Foul, fetid, noticeably unpleasant |
| Volume | Small; light spotting on cotton ball | Moderate to large; soaks pillow or pad |
| Duration | 24 to 72 hours | More than 72 to 96 hours, or recurring |
| Associated symptoms | None, or very mild ear pressure | Fever, pain, postauricular swelling |
| Clinical action | Monitor at home; confirm at follow-up | Same-day ENT or pediatrician contact |
| Drainage consistency | Thin, watery | Thick, creamy, mucoid |
This distinction matters clinically because abnormal drainage after tube extrusion can indicate that acute otitis media has recurred and requires treatment, whereas normal extrusion drainage resolves without antibiotics. Treating all post-extrusion drainage with antibiotics is not supported by the AAO-HNS guidelines, which emphasize clinical differentiation between drainage types rather than blanket antibiotic prescribing.
One population deserves special attention in this context: children who are immunocompromised, whether from primary immunodeficiency, chemotherapy, corticosteroid therapy, or HIV, are less able to produce the inflammatory signals that create obvious purulent drainage even when active infection is present. In these children, even pale, thin drainage persisting beyond 48 hours warrants prompt medical evaluation rather than home monitoring.
Key Takeaway: The color, smell, volume, and duration of ear drainage after tube extrusion are the four features that most reliably distinguish normal extrusion-related mucus from infection-driven otorrhea requiring medical treatment.
Premature Ear Tube Extrusion
Premature ear tube extrusion refers to tube loss occurring earlier than the expected timeline for the tube type placed, generally within the first three to six months for short-acting tubes. It can result from an episode of otitis media that accelerates the local inflammatory environment, from tube displacement due to trauma, from cerumen accumulation that physically moves the tube, or from a mismatch between the tube’s flange size and the thickness of the patient’s tympanic membrane.
From a physiological standpoint, active middle ear inflammation accelerates the lateral epithelial migration rate. When bacteria colonize the middle ear and trigger an acute otitis media episode, the mucosal response includes increased prostaglandin and cytokine release that upregulates epithelial cell turnover across the tympanic membrane. This effectively speeds the conveyor belt. A child who develops three episodes of otitis media through the tube during its first several months may lose the tube months ahead of the typical schedule.
Premature extrusion is not always a clinical failure. If Eustachian tube function has improved sufficiently, losing the tube early may cause no meaningful problem. However, premature extrusion in a child who still has active Eustachian tube dysfunction, persistent effusion, or a high baseline infection frequency returns that child to the clinical situation that prompted surgery in the first place.
Warning signs that premature extrusion may have occurred in a high-risk child:
- Tube loss confirmed or suspected before 4 months post-placement
- Immediate return of bilateral ear fullness or significant hearing difficulty
- Acute otitis media within 30 days of confirmed extrusion in a child with a history of recurrent infections
- Persistent effusion documented at a follow-up tympanogram within 6 weeks of extrusion
According to research published in Otolaryngology-Head and Neck Surgery, premature extrusion rates for standard grommet-type tubes range from 4% to 8% across pediatric populations, with higher rates in children who experience tube otorrhea during the tube’s retention period.
Recurring Ear Infections After Tubes Fall Out
Recurring ear infections after ear tube extrusion are one of the most significant clinical concerns for families and the most common reason repeat tube placement is considered. The return of recurrent acute otitis media after extrusion reflects the persistence of the underlying condition that tubes were meant to manage: dysfunctional Eustachian tube-mediated middle ear ventilation.
The Eustachian tube connects the middle ear space to the nasopharynx and serves three functions: pressure equalization between the middle ear and the atmosphere, drainage of middle ear secretions into the nasopharynx, and protection of the middle ear from nasopharyngeal pathogens and sound pressure. In children, the Eustachian tube is shorter, more horizontal, and floppier than in adults. This anatomy makes middle ear fluid accumulation far more common in children under age six, and it explains why otitis media is so strongly age-dependent.
When tubes fall out and Eustachian tube function has not matured sufficiently, the middle ear loses its artificial ventilation and reverts to the same physiological environment that produced infections before surgery.
According to the AAP Clinical Practice Guideline on Otitis Media, approximately 25% to 33% of children who receive tympanostomy tubes for recurrent acute otitis media will experience recurrence rates that meet criteria for repeat tube placement after extrusion of the first set. Children younger than age two at the time of first placement are at higher risk for requiring a second set.
Families can monitor for recurrence by watching for:
- Return of the pattern of ear infections that preceded the original surgery (frequency, severity, antibiotic need)
- Documented middle ear fluid at a follow-up tympanogram appointment
- Behavioral changes consistent with hearing loss returning, particularly in preschool-aged children
- Speech or language regression in a child whose communication had improved while tubes were in place
Children with enlarged or chronically inflamed adenoids are at particularly elevated risk for recurrent otitis media post-extrusion, because the adenoid pad in the posterior nasopharynx harbors bacterial biofilm that seeds the Eustachian tube with organisms during viral upper respiratory infections.
Ear Tube Complications and Their Symptoms
Ear tube complications are uncommon but real, and recognizing their symptoms prevents mismanagement as normal extrusion events. The most clinically relevant complications are tube obstruction (blockage of the tube lumen), tube-associated otorrhea from active infection through the patent tube, tympanosclerosis, persistent tympanic membrane perforation post-extrusion, and, rarely, tube displacement into the middle ear.
Tube obstruction occurs when cerumen, dried blood from the original surgery, mucus, or bacterial biofilm occludes the tube’s inner lumen, preventing its ventilating function. A child with a fully obstructed tube may present identically to a child whose tube has already extruded: muffled hearing, ear fullness, and possible return of middle ear effusion. The tube is still in place anatomically, but it has stopped working. Pneumatic otoscopy or tympanometry at a follow-up appointment reveals this situation, and an ENT can often restore patency with office-based tube suction.
Symptoms by complication type:
| Complication | Key Symptoms | Clinical Action Needed |
|---|---|---|
| Tube obstruction | Muffled hearing, fullness, no visible drainage | ENT appointment; office-based tube suctioning |
| Tube otorrhea (infection through patent tube) | Purulent drainage, pain, possibly fever | Same-day ENT or pediatrician; antibiotic eardrops typically |
| Tympanosclerosis | No acute symptoms; white chalky patches on eardrum seen on otoscopy | Routine follow-up; usually no treatment needed |
| Persistent perforation | Hearing loss, sensation of wind through ear, drainage with water exposure | ENT evaluation; possible surgical repair |
| Tube displacement into middle ear | No symptoms or foreign body sensation; found on otoscopy | ENT evaluation; may require surgical retrieval |
| Acute mastoiditis | High fever, postauricular swelling, ear protrusion, severe pain | Emergency room immediately |
Tympanosclerosis, a condition where calcium deposits form in the fibrous layer of the tympanic membrane, is a known long-term finding after tympanostomy tube placement. Research published in Otolaryngology-Head and Neck Surgery reports tympanosclerosis rates of 30% to 50% in children examined years after tube placement. This appears as white, chalky patches on the eardrum visible during otoscopic examination. In the vast majority of cases it causes no hearing loss and requires no treatment, though parents sometimes discover it incidentally at a follow-up visit and find it alarming.
Ear Tube Displaced Into the Middle Ear
An ear tube displaced into the middle ear space, rather than extruding outward through the external auditory canal, is a relatively rare but clinically important complication. It occurs in less than 1% of tube placements based on available clinical case series data, but when it happens, it creates a foreign body situation inside the middle ear that may require surgical retrieval.
Medial displacement happens when the tube shifts inward rather than following the normal lateral epithelial migration pathway outward. This can be caused by a tube that was placed too deeply at the time of surgery, trauma to the ear (including vigorous ear syringing or water pressure), significant middle ear negative pressure pulling the tube inward, or a tube flange that becomes entrapped in granulation tissue or scar that then contracts, pulling the tube toward the middle ear.
The physiological concern with a medially displaced tube is that a small foreign body in the middle ear can trigger persistent granulation tissue, chronic inflammation of the mucosa lining the middle ear, and rarely, erosion adjacent to the ossicular chain or the horizontal segment of the facial nerve in the fallopian canal.
Symptoms that suggest medial rather than lateral displacement:
- The tube cannot be visualized in the external auditory canal at a follow-up visit
- Persistent unilateral hearing loss without a clear cause on imaging
- Chronic middle ear pressure or fullness without evidence of effusion
- Foreign body sensation in the ear that does not match typical cerumen impaction
If medial displacement is suspected, the ENT will typically arrange imaging with high-resolution computed tomography (CT) of the temporal bone to confirm the tube’s location before planning retrieval. Most retrievals can be performed in an outpatient surgical setting rather than emergency surgery, unless the tube is adjacent to critical structures.
This complication is more likely with long-acting T-tubes in adults and with tubes placed in patients with prior middle ear scarring or tympanosclerosis, which can alter the normal tissue planes through which the tube should migrate.
Key Takeaway: Tube displacement into the middle ear is rare but produces persistent unexplained hearing loss and cannot be diagnosed without otoscopic or imaging examination by an ENT specialist, making follow-up appointments after suspected extrusion genuinely important.
Tympanic Membrane Perforation After Ear Tubes
A persistent tympanic membrane perforation after ear tube extrusion occurs when the myringotomy site fails to close spontaneously after the tube exits. The tympanic membrane’s normal repair mechanism relies on the migration of epithelial cells from the perforation’s edges inward to meet and seal, but this process can be disrupted by prior scarring, repeated surgery in the same location, infection, or the use of certain tube materials.
The pars tensa of the tympanic membrane, where the vast majority of tubes are placed, has a fibrous middle layer called the lamina propria that provides structural strength and supports the epithelial repair response. When this fibrous layer is damaged by repeated episodes of infection, by prior tube placements, or by prolonged tube retention, the repair response is less reliable.
Clinically, a persistent perforation presents as:
- A sensation of wind passing through the ear during changes in ambient pressure
- Reduced hearing on the affected side, typically a 10 to 25 decibel conductive loss across speech frequencies
- Drainage into the ear canal when water enters the ear (during bathing or swimming), because the water can pass directly into the middle ear space through the perforation
- On otoscopic examination by an ENT, a visible hole or thinned, translucent area in the tympanic membrane
Most perforations following short-acting tube extrusion close within 4 to 8 weeks if no active infection is present. Perforations persisting beyond 3 months after tube extrusion are considered unlikely to close spontaneously and warrant ENT assessment for possible surgical repair, a procedure called myringoplasty or tympanoplasty, depending on whether additional middle ear reconstruction is needed.
According to data in the Cochrane Database of Systematic Reviews, persistent perforation rates after short-acting tympanostomy tube extrusion range from 1% to 3% in children. Rates are higher, approximately 10% to 16%, after long-acting T-tube use, which reflects the more extensive tissue alteration produced by prolonged tube retention.
Ear Tube Falling Out in Adults
Adults who receive tympanostomy tubes for Eustachian tube dysfunction, patulous Eustachian tube, or conditions such as chronic serous otitis media experience tube extrusion through the same lateral epithelial migration mechanism as children, but several important clinical differences exist in the adult context.
First, Eustachian tube dysfunction in adults is less commonly driven by the positional and anatomical factors that affect children and more frequently linked to chronic allergic rhinitis, chronic sinusitis, laryngopharyngeal reflux, barotrauma (in divers and frequent air travelers), or nasopharyngeal pathology. If the underlying cause of adult Eustachian tube dysfunction is not addressed, tube extrusion leads to rapid symptom recurrence.
Second, adult tympanic membranes are typically thicker, more fibrous, and less mobile than pediatric ones. Lateral epithelial migration still occurs in adults, but the rate may be slightly slower on average, meaning some adults retain tubes toward the longer end of the expected range.
Third, the symptom profile in adults after tube extrusion includes features that are easier for adults to articulate than children can:
- A clear subjective return of the “plugged” sensation previously present before tube placement
- Autophony (hearing their own voice or breathing unusually loudly), which indicates pressure dysregulation
- A pop or click sensation in the ear when swallowing or yawning, reflecting middle ear negative pressure developing as Eustachian tube dysfunction returns
- Return of low-frequency hearing difficulty, particularly in noisy environments
Adults who received tubes for barotrauma-related Eustachian tube dysfunction should be aware that the period immediately after tube extrusion is a higher-risk window for pressure-related ear injury if they fly or dive before the tympanic membrane has fully healed. A board-certified otolaryngologist should clear adults with this history before they resume activities that involve significant ambient pressure change.
When to Call Your ENT After an Ear Tube Falls Out
Calling your ENT after an ear tube falls out is appropriate in nearly every case, even when the extrusion appears normal, because post-extrusion audiological assessment and tympanometric evaluation are the only ways to confirm that the tympanic membrane has sealed properly and that middle ear function is recovering as expected.
The question is not whether to call, but how urgently.
Schedule a routine appointment (within 2 to 4 weeks) when:
- You found the tube outside the ear and the child or adult has no pain, no fever, and no purulent drainage
- Hearing seems slightly reduced but the child is otherwise behaving normally
- There is a small amount of clear drainage that resolves within 48 hours
Call the same day (not urgent care, but ENT or pediatrician) when:
- Purulent or foul-smelling drainage has persisted beyond 72 hours
- The child has a fever of 38 degrees Celsius or higher with ear symptoms
- Pain is described as moderate to severe, not just pressure
- Hearing on the affected side has dropped noticeably and seems worse than before tubes were placed
- You cannot find the tube and the child is showing symptoms, making it unclear whether the tube extruded or displaced inward
Go to the emergency room when:
- Postauricular swelling, redness, warmth, or protrusion of the auricle is visible (these are signs of mastoiditis)
- The child has high fever with neck stiffness or severe headache (meningeal signs)
- Any symptom of facial weakness on the affected side appears (facial nerve involvement)
- Sudden severe vertigo or loss of balance accompanies ear symptoms
To communicate effectively with your ENT at the appointment, prepare to describe:
- The exact date you noticed the tube was gone or when symptoms began
- Which ear was affected and whether the child had bilateral tubes
- The drainage characteristics (color, odor, volume, duration)
- Whether fever was present and the peak temperature recorded
- Current hearing observations compared to when the tube was in place
- Any recent ear infections, upper respiratory tract infections, or antibiotic courses
Key Takeaway: A routine ENT follow-up appointment after confirmed tube extrusion is not optional, even when everything looks normal, because a tympanogram and hearing test are the only way to confirm the tympanic membrane has sealed and Eustachian tube function is adequate.
Emergency Symptoms: When to Call 911 or Go to the ER
Certain symptoms that can occur around the time of ear tube extrusion represent otologic emergencies. Do not wait to see if these resolve on their own.
Call 911 or go to the nearest emergency room immediately if you observe:
- Visible swelling, redness, or warmth behind the ear (postauricular area) combined with the outer ear being pushed forward away from the head. This presentation suggests acute mastoiditis, a bacterial infection of the mastoid air cells adjacent to the middle ear that can spread intracranially and requires emergency IV antibiotic treatment and often surgical drainage.
- High fever (above 39 degrees Celsius) with severe ear pain that is not responding to over-the-counter pain relief, particularly in a child under age five.
- Neck stiffness, photophobia (sensitivity to light), or severe headache in combination with ear symptoms. These are signs of meningeal irritation and require immediate emergency evaluation to rule out intracranial spread of infection.
- Sudden weakness or drooping on one side of the face in the same setting as ear pain and drainage. Facial nerve involvement in the context of middle ear or mastoid infection is a surgical emergency.
- Sudden severe spinning vertigo with inability to stand or walk, combined with ear pain, fever, or a history of ear infection. This presentation suggests labyrinthitis or, in severe cases, a labyrinthine complication of mastoid infection.
- A child who is lethargic, cannot be roused normally, or shows altered consciousness in the setting of ear symptoms and fever.
These presentations indicate infectious complications of otitis media that have progressed beyond the middle ear and require emergency medical assessment, IV antibiotics, and possible emergency surgical intervention. These are not conditions to monitor at home overnight or manage with an urgent care appointment.
Frequently Asked Questions About Symptoms of Ear Tubes Falling Out
How do I know if my child’s ear tube has fallen out?
The clearest sign is finding the tube itself outside the ear, on a pillow, towel, or in the outer ear canal.
Other indicators include a return of muffled hearing, ear fullness, or the behavioral signs of hearing difficulty (tugging at the ear, increased TV volume, saying “what?” more often) that were present before tubes were placed.
A formal tympanogram and audiogram at a follow-up ENT appointment are the only way to confirm extrusion and assess whether the tympanic membrane has closed properly.
Is it normal to have ear drainage when tubes fall out?
A small amount of clear to pale yellow, odorless drainage is normal during the final days of tube extrusion and typically resolves within 24 to 72 hours without treatment.
This drainage comes from the middle ear’s mucosal surface as the tube shifts position and is not a sign of infection.
Drainage that is yellow-green, foul-smelling, heavy in volume, or persists beyond 72 hours warrants same-day contact with your child’s otolaryngologist or pediatrician.
What does it look like when an ear tube falls out?
A typical short-acting tympanostomy tube (grommet or bobbin type) looks like a tiny metallic or translucent plastic cylinder or spool, roughly 1 to 2 millimeters in length and 1 to 1.5 millimeters across.
It may be coated with dried cerumen or mucus, giving it a beige or brownish appearance.
Parents often find it on a pillow after sleep or in the outer ear opening during bath time.
Can ear tubes fall out too early?
Yes. Premature extrusion, generally defined as tube loss within the first three to six months after placement, occurs in approximately 4% to 8% of pediatric grommet-tube placements according to research published in Otolaryngology-Head and Neck Surgery.
Premature extrusion can result from accelerated inflammation during acute otitis media episodes through the tube, cerumen displacement, or a mismatch between tube flange size and tympanic membrane thickness.
Whether premature extrusion requires action depends on whether Eustachian tube function has improved enough to maintain middle ear health without tube assistance, which an ENT can assess with tympanometry.
Do ear tubes need to be replaced after they fall out?
Not always. If Eustachian tube function has matured and middle ear health remains stable after extrusion, no further intervention is needed.
The AAP and AAO-HNS estimate that approximately 25% to 33% of children who had tubes placed for recurrent acute otitis media will experience recurrence rates that meet criteria for a second tube placement after the first set extrudes.
The decision for repeat surgery is based on documented hearing loss, effusion duration, infection frequency, and the child’s age and developmental needs, not on the simple fact that tubes fell out.
What should I do if I find my child’s ear tube on their pillow?
Place the tube in a clean sealed bag, note the date and which ear it came from, and contact your child’s otolaryngologist’s office to report the extrusion.
If the child has no pain, no fever, and no purulent drainage, this is typically a routine notification rather than an emergency.
Schedule a follow-up ENT appointment for a tympanogram and hearing assessment within two to four weeks to confirm the tympanic membrane has healed and middle ear function is stable.
Closing
Most of the time, an ear tube falling out is exactly what it is supposed to be: the tympanostomy tube completing its job and exiting naturally, leaving behind a tympanic membrane that is well-positioned to heal on its own. Recognizing this as the expected outcome prevents unnecessary anxiety. At the same time, knowing the specific drainage characteristics, pain patterns, and timeline features that signal something other than normal extrusion gives parents and adult patients the clinical clarity to act quickly when it matters.
The single most actionable step after any suspected tube extrusion, even one that appears completely normal, is a follow-up ENT appointment within two to four weeks for a tympanogram and hearing assessment. This appointment is the only objective way to confirm the eardrum has sealed, check for middle ear effusion, and determine whether the Eustachian tube is functioning well enough to maintain ear health without a new tube.
If you see postauricular swelling, a child who cannot be consoled, a fever above 39 degrees Celsius combined with ear pain, or any facial weakness, stop reading and go to the emergency room. Those symptoms belong in a different category entirely, one that moves fast.