What Causes Eye Mites? Demodex Facts for 2026
Eye mites, clinically called Demodex, are microscopic parasites that live inside hair follicles and oil glands along the eyelid margin, and what causes eye mites to become a problem is not their presence alone but the biological conditions that allow them to overgrow. Almost every adult has Demodex on their skin; the difference between harmless colonization and a clinical infestation comes down to sebum levels, immune response capacity, skin barrier integrity, and several well-defined individual risk factors.
According to research published in the journal Cornea, Demodex infestation is identified in a substantial proportion of people evaluated for chronic blepharitis, and its prevalence increases steeply with age, affecting an estimated 84% of adults over age 60 and nearly 100% of adults over age 70. The National Eye Institute, part of the National Institutes of Health, recognizes Demodex as one of the leading contributors to anterior blepharitis and recurrent eyelid inflammation in clinical practice.
This article covers the full picture of what causes eye mites to colonize, what shifts them from harmless passengers to active irritants, which populations carry the highest biological risk, and what the current diagnostic and treatment landscape looks like in 2026.
What Are Eye Mites (Demodex)?
Eye mites are microscopic arachnids belonging to the genus Demodex, and they are obligate parasites that live exclusively inside the pilosebaceous units (hair follicles and their associated sebaceous glands) of human skin, including the eyelids and eyelashes.
Unlike bacteria or fungi, Demodex are eight-legged arthropods, making them more closely related to spiders and ticks than to any microbial organism. They are visible only under microscopic examination, measuring between 0.1 and 0.4 millimeters in length. Their bodies are elongated and translucent, with short, stubby legs adapted for gripping follicular walls.
Demodex are not inherently pathological. They belong to what dermatologists and ophthalmologists call the skin microbiome, the complex ecological community of organisms that lives on healthy human skin. The key physiological distinction is density. At low population levels, Demodex mites appear to cause no harm and may even perform a scavenging function by consuming dead keratinocytes and excess sebum within follicles.
Problems arise when the mite population exceeds what the host’s innate immune system can regulate. That threshold, rather than mite presence alone, is what transforms a commensal relationship into a clinical condition called Demodex blepharitis or ocular demodicosis.
Key facts about Demodex biology:
- Two distinct species affect humans: Demodex folliculorum (eyelash follicle inhabitant) and Demodex brevis (sebaceous and meibomian gland inhabitant)
- The entire egg-to-adult lifecycle completes in approximately 14 to 18 days within the follicle
- Mites die and decompose inside follicles; their exoskeletal proteins and bacterial endosymbionts are the primary triggers of inflammation
- Demodex lack an excretory system, meaning their waste accumulates within and around the follicle until mite death
Older adults and people with oily skin types tend to have higher baseline mite densities, a pattern supported by clinical epidemiological data reviewed by the American Academy of Ophthalmology.
What Causes Eye Mites in Humans?
What causes eye mites in humans is a combination of normal skin biology, the availability of sebum as a food source, and any factor that reduces the immune system’s ability to keep the mite population in check.
Demodex mites require sebum, the waxy lipid-rich secretion produced by sebaceous glands throughout the skin, to survive and reproduce. They feed on sebum, dead skin cells, and the cellular lining of the follicle wall. This makes the eyelid margin a particularly favorable habitat: the eyelid skin contains a high density of both eyelash follicles and the specialized meibomian glands (also called tarsal glands) that produce the lipid layer of the tear film. Demodex brevis in particular targets the meibomian glands directly.
The actual cause of symptomatic eye mite infestation involves several overlapping biological mechanisms:
- Sebum overproduction provides excess nutritional substrate, allowing mite populations to expand beyond the host-tolerated threshold
- Follicular keratinization changes (abnormal accumulation of keratin within the follicle) create physical barriers that trap mites and debris in the follicle lumen
- Reduced immune surveillance allows mite density to increase without the normal inflammatory braking mechanism that would otherwise limit population growth
- Bacillus oleronius bacterial endosymbionts carried inside Demodex mites trigger an additional toll-like receptor (TLR)-mediated inflammatory cascade when mites die and release their contents, amplifying the immune response disproportionately
Research published in the British Journal of Dermatology by Lacey and colleagues identified Bacillus oleronius as a key secondary driver of inflammation in Demodex-associated skin conditions, noting that proteins produced by this bacterium activated immune responses in patients with rosacea-related Demodex overgrowth.
People with naturally oilier skin are at higher baseline risk because the sebum availability is greater. Women taking androgen-elevating medications (including some hormonal contraceptives that shift the androgen-to-estrogen ratio) may notice increased sebaceous activity that can raise mite density over time.
Demodex Folliculorum vs Demodex Brevis: Two Different Species
The two species of Demodex that cause eye mites in humans are Demodex folliculorum and Demodex brevis, and they differ in their preferred habitat, depth of tissue involvement, and the specific symptoms they produce.
Demodex folliculorum is the larger of the two species (0.3 to 0.4 mm) and lives primarily within the lumen of the eyelash hair follicle itself. It tends to cluster in groups of 2 to 6 mites per follicle, oriented head-down toward the follicle base. Its presence is most associated with anterior blepharitis, the form of eyelid inflammation that affects the eyelid margin at the base of the eyelashes. The characteristic sign of Demodex folliculorum overgrowth is cylindrical dandruff, a collarette of waxy debris encircling the base of individual eyelashes. This collarette forms because mite waste and dead mite bodies accumulate within the follicle and push outward along the hair shaft.
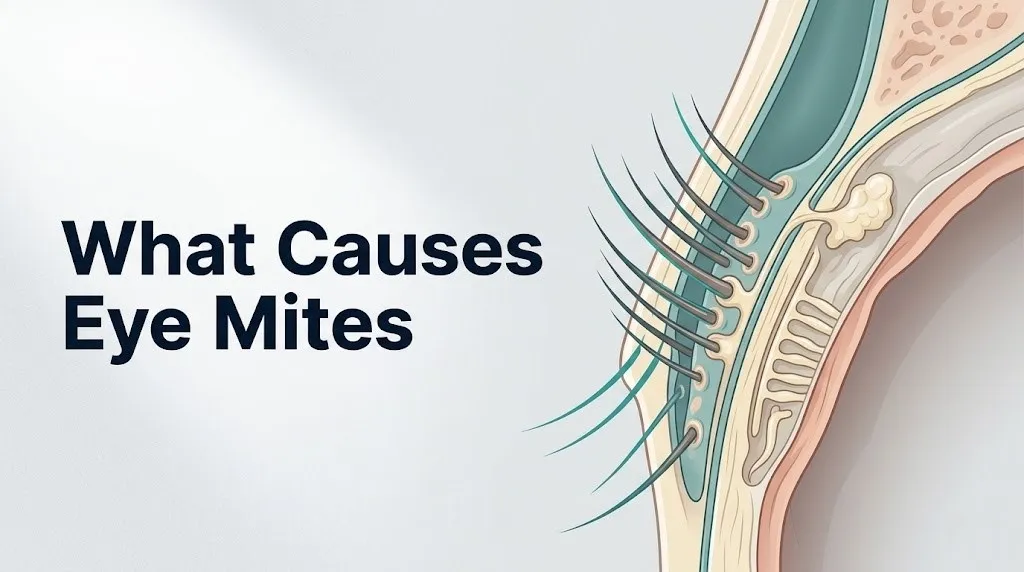
Demodex brevis is smaller (0.1 to 0.2 mm) and burrows deeper, inhabiting the sebaceous glands and meibomian glands rather than the follicle lumen. It lives as a solitary mite per gland. Its deeper location makes it the primary driver of posterior blepharitis and meibomian gland dysfunction, and it is harder to treat because it is less accessible to topical acaricide agents that penetrate only the eyelid surface.
| Feature | Demodex folliculorum | Demodex brevis |
|---|---|---|
| Size | 0.3 to 0.4 mm | 0.1 to 0.2 mm |
| Location | Eyelash hair follicle lumen | Sebaceous and meibomian glands |
| Typical density | 2 to 6 per follicle | 1 per gland |
| Associated condition | Anterior blepharitis, cylindrical collarettes | Posterior blepharitis, meibomian gland dysfunction |
| Treatment accessibility | Moderate (surface-accessible) | Lower (deeper tissue location) |
Children rarely develop pathological Demodex infestation because their sebaceous glands have not yet matured to adult-level secretory activity.
How Common Are Eye Mites?
Eye mites are extraordinarily common. Research published in the Cornea journal estimates that Demodex colonization, at some level, is present in approximately 45% of adults in their 20s and 30s, rising to roughly 84% in adults over 60, and approaching near-universal presence in adults over 70.
These figures reflect colonization, not symptomatic infestation. The proportion of people with Demodex at a density high enough to produce clinical symptoms is meaningfully lower. The American Academy of Ophthalmology has noted that Demodex blepharitis is estimated to affect approximately 20 million Americans based on clinical presentation data, making it one of the most underdiagnosed causes of chronic eyelid irritation.
The global prevalence of Demodex in patients presenting with blepharitis symptoms is estimated at 44% to 83%, depending on the clinical population studied and the diagnostic technique used, according to a systematic review summarized in the British Journal of Ophthalmology. That wide range reflects the substantial variation in how different clinical practices define pathological infestation threshold.
The condition is genuinely underrecognized in clinical practice. Many patients with Demodex blepharitis spend years being managed for generic dry eye disease or allergic conjunctivitis without ever being evaluated for Demodex specifically, because standard eyelid examination without slit-lamp evaluation of collarettes or eyelash sampling will miss the diagnosis.
Postmenopausal women represent a population that clinical observation consistently identifies as underdiagnosed: their sebum production changes with declining estrogen levels, and their immune function shifts with age, but their symptoms often overlap substantially with hormonal dry eye, delaying the Demodex-specific diagnosis.
Key Takeaway: Eye mites (Demodex) are present on most adults’ skin; the question is not whether you have them but whether their density is high enough to cause symptoms, a threshold shaped by sebum levels, immune function, and age.
What Causes Eyelash Mites to Overgrow?
Eyelash mites overgrow when the biological conditions in the eyelid environment tip in the mites’ favor: more food, less immune control, or both simultaneously.
The primary driver is excess sebum production by the eyelid’s sebaceous glands. Sebum is composed of triglycerides, wax esters, squalene, cholesterol, and free fatty acids. Demodex mites metabolize these lipid fractions as their primary nutritional source. When sebum output increases, whether due to hormonal shifts, skin condition, medication effect, or gland hyperplasia, the carrying capacity of the eyelid follicular environment for Demodex rises in parallel.
The mite’s rapid reproductive cycle amplifies this effect. Within a single follicle, a fertilized female Demodex deposits eggs in the follicle base. The egg hatches into a 6-legged larva within 60 hours. The larva molts through two nymph stages (protonymph and deutonymph) before reaching the 8-legged adult stage, completing the full cycle in 14 to 18 days. This means that in a sebum-rich environment with reduced immune regulation, the mite population can double in under three weeks.
The second major driver is follicular keratinization. Abnormal keratin buildup within the follicle lumen physically traps mites, debris, and bacterial products inside the follicle. Instead of the mite population turning over naturally as mites age and die, dead mite bodies and their bacterial payload (Bacillus oleronius proteins) accumulate within the follicle, triggering sustained inflammatory responses via TLR-2 and TLR-4 signaling.
Factors that cause eyelash mites to overgrow include:
- Elevated sebum production from hormonal changes, oily skin type, or androgen excess
- Abnormal follicular keratinization (seen in seborrheic dermatitis)
- Reduced innate immune surveillance (aging, immunosuppressive medications, HIV)
- Inadequate eyelid hygiene that allows debris, oils, and mite waste to accumulate
- Warm, humid environmental conditions that support mite activity and reproduction
- Use of heavy oil-based eye makeup or cosmetic products that are not fully removed nightly
Men tend to have higher sebum production than women before age 50 due to androgen-driven sebaceous gland activity, which partially explains why Demodex density is higher in men across most age groups studied.
Eye Mites Causes Related to Immune Function
Eye mite overgrowth is fundamentally a failure of immune regulation to keep a normally occurring organism at a benign population density.
The innate immune system, the body’s first-line defense that does not require prior exposure to a specific pathogen, normally surveils the skin for signals of microbial excess. Toll-like receptors embedded in keratinocytes and dendritic cells of the skin detect molecular patterns from Demodex exoskeletal proteins and from Bacillus oleronius products released when mites die within follicles. At low mite densities, this surveillance produces a controlled, low-grade inflammatory response that limits mite reproduction without causing symptomatic tissue damage.
When immune function is reduced, whether through disease, medication, or age-related immune senescence, this regulatory mechanism fails. The mite population grows beyond the threshold that produces pathological inflammation, and the resulting unchecked inflammatory cascade causes the tissue changes characteristic of Demodex blepharitis.
The strongest evidence for immune suppression as a driver of pathological eye mite infestation comes from studies of immunocompromised patient populations. According to research data reviewed by the National Institutes of Health, patients with HIV/AIDS, organ transplant recipients on long-term immunosuppressive therapy, and patients receiving prolonged systemic corticosteroid treatment have Demodex infestation rates and densities substantially higher than age-matched immunocompetent individuals.
Specific immune conditions that elevate Demodex risk:
- HIV/AIDS with advanced CD4 T-cell depletion
- Post-organ transplant immunosuppressive regimens (calcineurin inhibitors, mycophenolate mofetil)
- Long-term systemic corticosteroid therapy (prednisone, dexamethasone)
- Chemotherapy-associated immune suppression
- Primary immune deficiency disorders
- Topical corticosteroid overuse on eyelid skin (damages local skin immunity and disrupts the eyelid skin barrier)
People with diabetes mellitus also show higher Demodex colonization density in clinical studies, likely because both innate immune dysregulation and altered sebum composition in diabetic individuals create a more favorable mite environment.
Key Takeaway: Pathological eye mite infestation is not simply about having Demodex — it is about the immune system’s failure to regulate mite density, which is why immunocompromised individuals and older adults carry the highest infestation burden.
Age and the Risk of Eye Mite Infestation
Age is the strongest single predictor of Demodex density, and the biological reason is dual: sebaceous gland changes and progressive immune senescence.
From puberty through middle age, sebaceous glands (including the meibomian glands of the eyelid) are under androgenic hormonal regulation. Sebum production peaks in young adulthood and begins to change in composition and volume through the 5th and 6th decades of life. Paradoxically, while overall sebum volume may decrease with age, the sebum composition shifts, with higher proportions of waxy esters and altered fatty acid profiles that are favorable for Demodex nutrition.
Simultaneously, the aging immune system undergoes immune senescence, the progressive decline in innate and adaptive immune function that occurs naturally with advancing age. This includes reduced toll-like receptor signaling efficiency, decreased natural killer cell activity, and a reduced ability to mount localized inflammatory responses that would ordinarily limit Demodex population growth. The net effect is that older adults cannot regulate mite density the way younger adults can, even at the same sebum production levels.
According to data cited by the American Academy of Ophthalmology, the near-universal Demodex presence observed in adults over 70 reflects this combined biological shift. Adults in this age group often have Demodex blepharitis as a primary undiagnosed driver of their dry eye and eyelid discomfort symptoms.
| Age Group | Estimated Demodex Colonization Rate | Clinical Infestation Likelihood |
|---|---|---|
| Under 20 | Rare, under 10% | Very low |
| 20 to 40 years | Approximately 45% | Low to moderate |
| 40 to 60 years | Approximately 60 to 75% | Moderate |
| Over 60 years | Approximately 84% | Moderate to high |
| Over 70 years | Approaching 100% | High |
Older adults who wear contact lenses or who have concurrent dry eye disease face compounded eyelid margin stress that can accelerate the shift from asymptomatic colonization to clinical blepharitis.
Demodex and Rosacea: The Inflammatory Connection
Demodex density is consistently higher in people with rosacea than in the general population, and the relationship between these two conditions is bidirectional: rosacea creates biological conditions that favor Demodex overgrowth, and Demodex overgrowth worsens the inflammatory pathology of rosacea.
Rosacea is a chronic inflammatory skin condition characterized by facial flushing, persistent erythema, papules, pustules, and telangiectasia, primarily affecting the central face including the nose, cheeks, chin, and eyelid area. A defining feature of rosacea pathophysiology is the dysregulation of innate immune signaling, particularly through toll-like receptor 2 (TLR-2), which is overexpressed in rosacea-affected skin. This dysregulation means that when Bacillus oleronius proteins from Demodex mites are detected by TLR-2, the inflammatory response is substantially amplified compared to what occurs in non-rosacea skin.
Research published in the Journal of the American Academy of Dermatology has found that patients with rosacea have Demodex folliculorum densities 2 to 5 times higher than age-matched control subjects without rosacea. This elevated mite density is not fully explained by increased sebum production alone and appears partly attributable to the altered immune environment of rosacea-affected skin.
The clinical implication is that patients with ocular rosacea (rosacea involving the eyelids and conjunctiva) have a particularly high likelihood of concurrent Demodex blepharitis. The American Academy of Ophthalmology recommends that patients with established rosacea presenting with eyelid symptoms be evaluated specifically for Demodex as a potential co-contributor rather than managed exclusively as standard dry eye disease.
Women with rosacea represent a population in whom Demodex blepharitis is substantially underdiagnosed because their eyelid symptoms are frequently attributed to hormonal dry eye or allergic sensitivity rather than evaluated for the Demodex-rosacea connection.
Key Takeaway: In a patient with rosacea and eyelid symptoms, Demodex overgrowth is a likely co-driver of the condition rather than a coincidental finding, because rosacea’s TLR-2 dysregulation creates a permissive inflammatory environment for mite population expansion.
Demodex and Seborrheic Dermatitis
Seborrheic dermatitis is a chronic inflammatory skin condition of the scalp, face, and other sebum-rich areas, driven by abnormal immune responses to the yeast Malassezia furfur in sebum-rich environments. Its connection to Demodex eye mites is direct, physiological, and clinically underappreciated.
The mechanism links through sebum overproduction. Seborrheic dermatitis produces elevated sebaceous gland activity and disrupted follicular keratinization on affected skin surfaces. Both of these changes directly elevate Demodex carrying capacity: more sebum means more food, and follicular keratinization traps mites and debris within follicles longer than normal.
When seborrheic dermatitis affects the scalp, eyebrows, and forehead (its most common distribution), the eyelid margin is directly adjacent to affected skin. Demodex mites can migrate short distances across the skin surface, and the inflamed, sebum-rich eyelid margin skin in people with seborrheic dermatitis provides an ideal environment for the mite population to establish and grow.
Clinically, people with seborrheic dermatitis who develop eyelid symptoms should be evaluated for concurrent Demodex blepharitis because treating the blepharitis with standard lid hygiene alone will be insufficient if the underlying seborrheic dermatitis remains uncontrolled.
Consider this as an ecological parallel: seborrheic dermatitis is like leaving food out in a warm room. Demodex, already present in small numbers, has everything it needs to expand its population. Treating the eyelid symptoms without addressing the seborrheic dermatitis is equivalent to cleaning the food off the counter but leaving the warm conditions unchanged.
Treatment of the scalp and facial seborrheic dermatitis (using ketoconazole shampoo, selenium sulfide, or other dermatologist-recommended antifungal approaches) is typically managed in parallel with Demodex blepharitis treatment for patients who have both conditions. A board-certified dermatologist should be involved in the management plan when seborrheic dermatitis is a confirmed or suspected contributing cause.
Contact Lens Wearers and Eye Mite Risk
Contact lens wear creates a specific set of mechanical and physiological changes to the eyelid margin environment that increase the risk of both Demodex colonization and symptomatic infestation.
The primary mechanism involves the tear film lipid layer. In a healthy eye without contact lenses, the meibomian glands secrete a lipid layer that spreads across the tear film surface with each blink, stabilizing the tear film and preventing rapid evaporation. Contact lenses disrupt this process mechanically: the lens surface traps some lipid secretions, alters the blink dynamics, and creates a warmer, more humid microenvironment between the lens and the eyelid. This altered environment elevates local temperature slightly and increases moisture, both of which support Demodex mite activity and reproduction.
Extended-wear contact lens users (those who sleep in their lenses, either accidentally or by prescription) show significantly higher rates of eyelid margin colonization in clinical studies reviewed in Cornea journal. The eyelid margin in extended-wear lens users accumulates more lipid debris, cellular material, and protein deposits at the eyelid margin, all of which serve as additional nutritional substrate for Demodex.
Additionally, contact lens wearers who do not adequately clean their eyelid margins create compounding debris accumulation over months to years. This debris layer physically traps Demodex mites in the follicle environment and provides a sustained food source independent of sebum levels alone.
Signs a contact lens wearer should watch for that may indicate Demodex blepharitis:
- Progressive contact lens intolerance not explained by lens type, cleaning solution, or fit
- Itching or burning at the eyelid margin that worsens in the morning
- Waxy debris or crusty buildup at the base of eyelashes that returns despite daily hygiene
- Recurrent styes or chalazia (blocked meibomian glands)
- Blurred vision in the afternoon or evening that improves with blinking
Contact lens wearers experiencing any of these patterns should be evaluated by a board-certified ophthalmologist or optometrist who is trained in slit-lamp eyelid margin examination, specifically asking whether Demodex assessment is included in the evaluation.
Symptoms of Eye Mites in Humans
The symptoms of eye mites in humans reflect two overlapping biological processes: the direct mechanical irritation caused by mite activity within follicles, and the inflammatory response triggered by mite waste, dead mite bodies, and Bacillus oleronius bacterial products.
Most people with low-level Demodex colonization experience no symptoms. When mite density rises above the host’s regulatory threshold, the eyelid margin becomes the primary site of inflammation, producing a characteristic symptom pattern that clinical ophthalmologists and optometrists describe as Demodex blepharitis.
The symptom that most consistently distinguishes Demodex blepharitis from other causes of eyelid irritation is cylindrical dandruff, also called collarettes. These are semi-transparent, waxy, sleeve-like deposits that encircle the base of individual eyelash shafts. They form because dead mites, mite eggs, shed exoskeletal material, and accumulated follicular debris accumulate around the hair shaft and are pushed upward along it. Collarettes are visible with magnification and represent the most specific clinical sign of Demodex folliculorum overgrowth.
Full symptom profile of eye mites in humans:
- Itching at the eyelid margin, typically worse in the morning (caused by increased overnight mite activity in the dark)
- Burning or stinging sensation along the eyelid edge
- Feeling of grittiness or a foreign body sensation in the eye
- Redness of the eyelid margin (anterior or posterior, depending on which Demodex species predominates)
- Cylindrical, waxy collarettes at the base of eyelashes (specific sign of Demodex folliculorum)
- Crusting or sticky discharge at the eyelid margin on waking
- Recurrent styes (hordeola) or chalazia from blocked meibomian glands
- Blurred or fluctuating vision (from tear film instability caused by meibomian gland compromise)
- Loss of eyelashes (madarosis) in severe or chronic untreated cases
- Eyelash misdirection (trichiasis) in advanced cases from follicular scarring
Symptoms in immunocompromised patients may be more severe, may involve a larger area of the eyelid, and may be accompanied by secondary bacterial eyelid infection because the same immune deficit that allows mite overgrowth also impairs defense against opportunistic bacteria at the inflamed eyelid margin.
Key Takeaway: The waxy collarette at the base of individual eyelashes is the single most diagnostically specific sign of Demodex folliculorum overgrowth and should prompt a slit-lamp eyelid examination by a qualified eye care professional.
Eye Mites and Meibomian Gland Dysfunction
Meibomian gland dysfunction (MGD) is one of the most clinically consequential complications of Demodex brevis infestation, and it is the primary pathway through which eye mites cause evaporative dry eye disease.
The meibomian glands are modified sebaceous glands embedded in the tarsal plate of both the upper and lower eyelids. There are approximately 25 to 40 meibomian glands in the upper eyelid and 20 to 30 in the lower eyelid. Their sole function is to secrete meibum, a complex lipid mixture that forms the outermost (oil) layer of the tear film. This lipid layer acts as a seal over the aqueous layer of tears, slowing evaporation and maintaining tear film stability between blinks.
Demodex brevis lives inside the meibomian glands. As the mite population grows within these glands, several damaging processes occur simultaneously: mites physically obstruct the gland orifices with their bodies and accumulated debris, reducing meibum flow; mite waste and Bacillus oleronius proteins trigger inflammatory cytokine release (IL-1B, TNF-alpha) that damages the meibomian gland ductal epithelium; and chronic inflammation leads to gland dropout, the permanent loss of secretory meibomian gland tissue identifiable on infrared meibography imaging.
The International Workshop on Meibomian Gland Dysfunction, whose findings were published in Investigative Ophthalmology and Visual Science, identified Demodex infestation as a clinically recognized cause of obstructive meibomian gland dysfunction. Patients with Demodex-related MGD experience a reduced lipid layer thickness, faster tear evaporation, increased tear film osmolarity, and the characteristic symptom of fluctuating blurred vision that clears briefly after blinking but returns within seconds.
Dry eye patients who do not respond to standard warm compress and artificial tear therapies should be evaluated for Demodex as an underlying contributor. Simply adding more artificial tears to an eye with unchecked Demodex-driven MGD is comparable to adding water to a leaking container without fixing the leak: it manages the symptom without addressing the mechanism.
How Do Eye Mites Spread Between People?
Eye mites spread primarily through direct skin-to-skin contact, particularly prolonged close contact that allows mites to transfer from one person’s facial skin or eyelid area to another person’s.
Demodex mites cannot jump, fly, or survive long periods away from the warmth and moisture of a living host’s skin. At normal room temperature (approximately 20 to 25 degrees Celsius), Demodex mites can survive off a human host for only 1 to 2 hours before dying from desiccation. This brief off-host survival window significantly limits indirect transmission pathways compared to organisms like lice or scabies mites.
The primary transmission routes for Demodex are:
- Direct facial contact (as occurs between parents and young children, or intimate partners)
- Sharing of eye makeup, applicators, or mascara wands
- Sharing of pillowcases or towels used on the face without washing between uses
- Using makeup testers in retail settings without individual applicators
Shared pillowcases represent a meaningful transmission vector because mites dislodged during sleep can transfer to the fabric surface while it is still warm and humid from body contact. The next person using the same pillowcase within a short period may receive a mite transfer to their own facial skin.
Household transmission within families is documented in clinical case series. A 2022 observational study in Cornea noted that when one household member received a diagnosis of symptomatic Demodex blepharitis, other adult household members had a meaningfully higher rate of Demodex colonization than would be expected based on population prevalence alone, suggesting regular household contact as a transmission mechanism.
Transmission does not mean automatic symptomatic infestation. Whether transferred mites establish a pathological-density colony in the new host depends entirely on that person’s sebum levels, immune regulation, and eyelid hygiene practices.
Can You Get Eye Mites from Pets?
The direct answer is: humans do not contract the same species of Demodex that cause disease in dogs and cats, so pet-to-human eye mite transmission in the pathological sense does not occur.
Dogs are commonly affected by Demodex canis, a species that evolved as an obligate parasite of canine pilosebaceous units and is host-specific. Cats carry Demodex cati and Demodex gatoi. These species are physiologically adapted to the specific skin biology of their host species: their morphology, reproductive strategy, and nutritional requirements are calibrated for canine or feline sebum composition and follicle architecture, not for human skin.
The two human Demodex species, Demodex folliculorum and Demodex brevis, are similarly host-specific and evolved in the context of human skin biology. Cross-species transmission resulting in clinical infestation has not been demonstrated in peer-reviewed literature.
That said, people who work extensively with animals and have reduced immune function (veterinary professionals with immune-compromising conditions, for example) may theoretically encounter a broader range of skin surface organisms through occupational exposure, but this is not a documented clinical pathway for pathological Demodex infestation from pets.
For pet owners concerned about their dog or cat showing signs of Demodex infestation (patchy hair loss, thickened or scaly skin, eyelid margin changes in cats with Demodex cati), evaluation and treatment by a licensed veterinarian is necessary. Veterinary Demodex infestation in dogs is a genuine clinical condition requiring specific antiparasitic treatment, diagnosis via skin scraping and microscopy, and assessment for underlying immune conditions (particularly in adult-onset canine demodicosis, where systemic disease must be ruled out).
Pet owners do not need to be concerned about acquiring eye mites from their cats or dogs. Their own Demodex exposure comes from other humans and from their own existing skin colonization.
Key Takeaway: You cannot get eye mites from your dog or cat because Demodex species are host-specific; human eye mites (Demodex folliculorum and brevis) are acquired only from other humans or from your own existing skin colonization reaching the eyelid area.
How Eye Mites Are Diagnosed
Eye mites are diagnosed through direct examination of the eyelid margin and microscopic analysis of plucked eyelashes, performed by a board-certified ophthalmologist or a clinical optometrist trained in anterior segment eyelid disease.
The standard diagnostic approach begins with slit-lamp biomicroscopy of the eyelid margin. Under magnification, the examiner looks for the characteristic collarettes (cylindrical dandruff) encircling the bases of eyelash shafts. The presence of collarettes is considered by the American Academy of Ophthalmology to be a pathognomonic (uniquely diagnostic) sign of Demodex folliculorum infestation when seen in the classic distribution.
To confirm the diagnosis and quantify mite burden, the clinician typically plucks 2 to 4 eyelashes from both the upper and lower eyelids using fine forceps. These lashes are placed on a glass slide, covered with a coverslip, and examined under light microscopy. The examiner counts live mites, eggs, larvae, and empty mite casings. A threshold of 1 to 2 mites per eyelash is generally accepted as clinically significant by most anterior segment specialists, though clinical correlation with symptom severity is always considered.
The diagnostic process step by step:
- The patient reports persistent eyelid itching, morning crusting, or recurrent styes, prompting an eyelid-specific evaluation
- Slit-lamp examination identifies collarettes at eyelash bases, degree of eyelid margin redness, and evidence of meibomian gland orifice plugging
- Eyelash sampling (epilated lashes) is placed on a microscopy slide and examined for Demodex count and species identification
- Meibomian gland function may be assessed using meibography (infrared imaging of gland structure) and meibum expressibility testing
- The examiner documents mite count per lash, species identified, and associated clinical findings to guide treatment selection and severity classification
People who have been managed for chronic dry eye disease for more than 6 months without adequate symptom control should specifically ask their eye care provider whether Demodex evaluation has been performed, because standard dry eye workups do not automatically include eyelash microscopy in most clinical settings.
Eye Mite Treatment and Prevention
Eye mite treatment targets the Demodex mite population directly while addressing the eyelid environmental conditions that enabled overgrowth.
The U.S. Food and Drug Administration approved lotilaner ophthalmic solution 0.25% (marketed as Xdemvy) in July 2023 as the first medication specifically approved for the treatment of Demodex blepharitis in adults. In the pivotal Phase 3 clinical trials (SATURN-1 and SATURN-2), lotilaner ophthalmic solution demonstrated statistically and clinically meaningful reductions in mite density and in the clinical signs of Demodex blepharitis compared to vehicle control over a 6-week treatment period. Lotilaner works by blocking GABA-gated chloride channels in Demodex mites, which are invertebrate-specific channels not present in human cells, causing paralysis and death of the mites without harming the patient’s ocular tissue.
Before FDA approval of lotilaner, the most commonly used acaricide approach was eyelid cleansing with tea tree oil-based formulations standardized to contain terpinen-4-ol, the specific tea tree oil component with demonstrated activity against Demodex. Research published in Cornea found that in-office weekly lid scrubs with 50% tea tree oil, followed by daily home use of 5% tea tree oil lid cleansers, significantly reduced mite density over 4 weeks. At-home use of pure or high-concentration tea tree oil on the eyelids is not recommended because concentrations above 10 to 15% can cause significant corneal and conjunctival toxicity.
Prevention and long-term management approaches:
- Daily eyelid margin hygiene using commercially formulated lid scrubs or hypochlorous acid-based eyelid cleansers (available without prescription)
- Regular replacement of eye makeup, particularly mascara, every 3 months and applicator wands at every use
- Washing pillowcases and face towels at least twice weekly in hot water (above 54 degrees Celsius kills Demodex)
- Removing all eye makeup completely before sleep nightly; oil-based makeup removers should be rinsed away thoroughly
- Regular warm compress use (5 to 10 minutes daily) to maintain meibomian gland function and reduce the lipid debris that feeds mites
- Avoiding topical corticosteroid application to the eyelid skin unless specifically directed by a physician, as chronic topical steroid use compromises local immune surveillance and can worsen Demodex colonization
Patients with underlying rosacea or seborrheic dermatitis require coordinated management of those conditions alongside Demodex-specific treatment; addressing the Demodex without treating the contributing skin condition typically results in relapse. A board-certified ophthalmologist should manage the eye-specific treatment, coordinating with a board-certified dermatologist when concurrent skin conditions require systemic or topical therapy.
Frequently Asked Questions About Eye Mites
What causes eye mites to develop in the first place?
Eye mites develop because Demodex mites, which are naturally present on most adult skin, overgrow when sebum levels are high, immune regulation is reduced, or eyelid hygiene allows follicular debris to accumulate.
The shift from harmless colonization to symptomatic infestation is driven by the combined effects of excess nutritional substrate (sebum), faster mite reproduction, and the inflammatory response to Bacillus oleronius bacterial proteins released when mites die inside follicles.
Aging, rosacea, seborrheic dermatitis, immunosuppression, and contact lens wear are the most clinically documented causes of pathological Demodex density.
Are eye mites contagious from person to person?
Yes, Demodex mites can transfer between people through direct facial contact, shared pillowcases, shared eye makeup applicators, or shared face towels.
Transmission does not guarantee symptomatic infestation; whether a transferred mite colony grows to clinically significant density depends on the recipient’s sebum levels, immune function, and eyelid hygiene.
Reducing transmission risk involves replacing pillowcases twice weekly, never sharing mascara or eye makeup applicators, and washing face towels used on the eyelid area regularly in hot water.
What does it feel like to have eye mites?
Eye mite infestation typically produces itching at the eyelid margin (often most intense in the morning), a gritty or foreign body sensation in the eye, and burning or stinging along the eyelid edge.
Many people also notice waxy debris at the base of their eyelashes that returns daily despite hygiene efforts, which is caused by mite waste and dead mite material accumulating around individual hair shafts.
In moderate to severe infestation, blurred vision that temporarily clears with blinking may indicate that Demodex has compromised meibomian gland function and destabilized the tear film.
Can you see eye mites without a microscope?
Individual Demodex mites are too small to see with the naked eye, measuring only 0.1 to 0.4 millimeters in length.
The most visible sign of eye mite infestation is the cylindrical, waxy collarette that forms around the base of affected eyelashes, which can sometimes be seen with close inspection in bright light but is most clearly identified under slit-lamp magnification.
A definitive diagnosis requires microscopic examination of plucked eyelashes by a board-certified ophthalmologist or optometrist trained in anterior segment eyelid disease.
What makes eye mites worse?
Eye mite infestation worsens with factors that increase sebum availability (oily skin, androgen excess, uncontrolled rosacea), reduce immune regulation (aging, immunosuppression, corticosteroid use), or allow follicular debris to accumulate (poor eyelid hygiene, wearing eye makeup to bed, not replacing mascara regularly).
Topical corticosteroid application to the eyelid skin, often used for eyelid eczema or dermatitis, can suppress local immune surveillance and allow Demodex populations to expand significantly, sometimes producing a rebound infestation when the steroid is stopped.
Warm, humid environmental conditions also support increased mite activity and reproductive rate.
When should I see a doctor for eye mites?
You should be evaluated by a board-certified ophthalmologist or optometrist if you have persistent eyelid itching, burning, or gritty sensation lasting more than 2 to 4 weeks that is not improving with standard eyelid hygiene.
Recurrent styes or chalazia (more than one per year), progressive contact lens intolerance, or worsening dry eye symptoms that do not respond to artificial tears are additional reasons to seek a Demodex-specific eyelid evaluation.
Immunocompromised individuals, including those on long-term corticosteroids, chemotherapy, or with HIV, should request Demodex evaluation at the first sign of chronic eyelid irritation because infestations in this group can progress more rapidly and require targeted acaricide treatment rather than watchful waiting.
Closing
Eye mites are not a fringe condition or something to feel embarrassed about. They are a biological reality of adult skin, and the question is never whether you have Demodex but whether your immune system, sebum environment, and eyelid hygiene are keeping them at a density that does not cause harm.
The most practical thing a reader can take from this article is this: chronic eyelid itching, morning crusting, waxy debris at the base of eyelashes, recurrent styes, or dry eye that is not responding to standard treatment deserves a specific Demodex evaluation, not just another round of artificial tears. Ask your eye care provider directly whether they examined your eyelid margins under the slit-lamp for collarettes and whether eyelash sampling was performed.
If you are over 60, have rosacea, use immunosuppressive medications, or have had prolonged contact lens wear, your risk of Demodex-driven eyelid disease is meaningfully higher than population average. A board-certified ophthalmologist is the right person to evaluate, confirm, and direct treatment for symptomatic Demodex blepharitis in 2026, and with FDA-approved targeted therapy now available, symptomatic relief from a properly diagnosed infestation is a realistic, achievable outcome.