Wrist Fracture Symptoms: Signs, Types, and When to Act
Wrist fracture symptoms include immediate, sharp pain at the point of injury, rapid swelling, visible bruising, and limited ability to move the wrist or grip anything, with some fractures producing visible deformity and others causing deceptively mild pain that misleads people into delaying care. The severity and specific symptom pattern depend on which bone has broken, how badly it has displaced, and whether nerves or blood vessels near the fracture site have been compressed or damaged.
Wrist fractures are among the most common fractures seen in emergency departments. The American Academy of Orthopaedic Surgeons reports that distal radius fractures alone account for approximately one in six of all fractures treated in emergency departments. The risk of missing a fracture on initial clinical assessment is real: research published in the Journal of Bone and Joint Surgery has found that scaphoid fractures go undetected on initial X-ray in up to 20 percent of cases, with potentially serious consequences if treatment is delayed.
This article covers every clinically recognized wrist fracture symptom, the anatomical and physiological reason each symptom occurs, how to distinguish fracture types by their symptom pattern, which signs indicate a neurovascular emergency, and the specific thresholds that mean you need an emergency room, not an urgent care appointment.
What Is a Wrist Fracture: Anatomy and Types
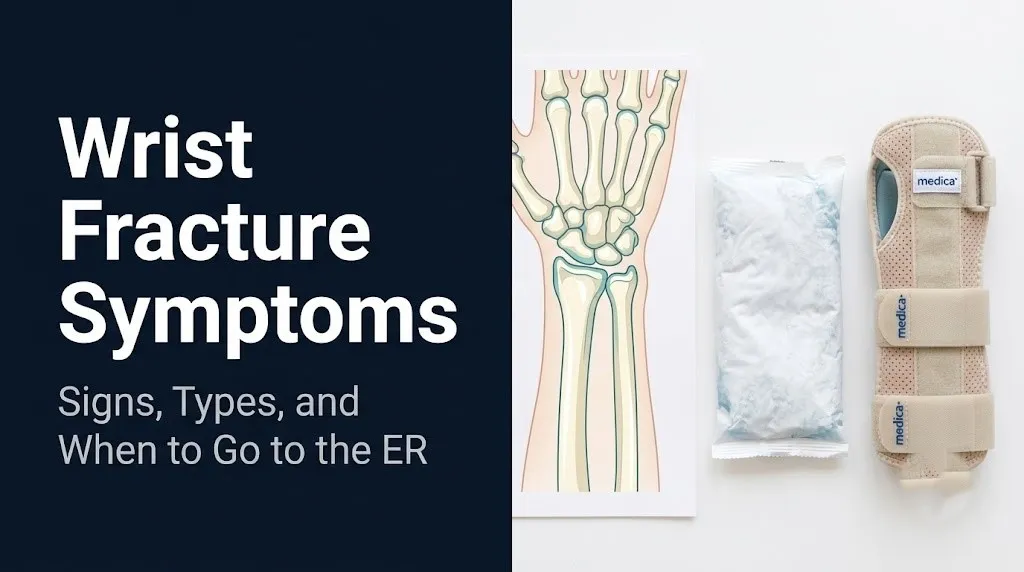
A wrist fracture is a break in one or more of the ten bones that form the wrist joint: the distal radius, distal ulna, and eight carpal bones (scaphoid, lunate, triquetrum, pisiform, trapezium, trapezoid, capitate, and hamate).
The wrist is not a single joint. It is a complex of two primary articulations, the radiocarpal joint (where the radius meets the proximal carpal row) and the midcarpal joint (where the proximal and distal carpal rows meet), surrounded by dense ligamentous support including the scapholunate ligament and the triangular fibrocartilage complex (TFCC). A fracture anywhere in this complex disrupts the precise geometry that allows smooth, pain-free wrist motion.
The most frequently fractured bone is the distal radius, which forms the primary weight-bearing surface of the wrist joint. When someone falls on an outstretched hand (a mechanism called FOOSH injury, for fall on outstretched hand), the ground reaction force travels up through the palm, through the carpal bones, and concentrates at the distal radius. If the force exceeds the bone’s tensile and compressive strength, it breaks.
The major clinical fracture types, each with a distinct symptom pattern:
- Colles fracture: distal radius fracture with dorsal (backward) displacement, the most common pattern overall
- Smith fracture: distal radius fracture with volar (forward) displacement, less frequent, often from a fall on a flexed wrist
- Barton fracture: intra-articular distal radius fracture involving the joint surface itself
- Scaphoid fracture: fracture of the scaphoid carpal bone, the most commonly missed wrist fracture
- Chauffeur fracture: isolated radial styloid fracture, often from direct impact
Each fracture type has a distinct mechanism, displacement pattern, and clinical presentation. Knowing which type is likely based on symptoms changes the urgency and type of imaging required.
Wrist Fracture Symptoms: The Complete Clinical Picture
The core wrist fracture symptoms are immediate pain at the injury site, rapid swelling within minutes to hours, bruising that develops over 24 to 48 hours, tenderness to touch directly over the broken bone, and reduced or absent ability to move the wrist through its normal range of motion.
These are the symptoms present in the overwhelming majority of wrist fractures, regardless of which specific bone has broken. The Mayo Clinic notes that immediate, localized pain following a wrist injury is the most consistent clinical feature of fracture, though it also acknowledges that some fractures, particularly hairline and scaphoid fractures, can produce pain modest enough that people dismiss them as sprains.
The complete symptom inventory by clinical significance:
- Immediate, sharp pain at the moment of injury, localizing to the dorsal or volar wrist within seconds
- Rapid swelling of the wrist and surrounding tissues within minutes, sometimes extending to the forearm or hand
- Ecchymosis (bruising) appearing within 1 to 48 hours, following hematoma tracking through soft tissue planes
- Point tenderness: sharp pain produced by pressing directly over the fracture site
- Reduced grip strength, often to near-zero in displaced fractures
- Limited or absent active wrist range of motion (flexion, extension, radial and ulnar deviation)
- A sensation of the wrist “giving way” or feeling structurally unstable
- Numbness or tingling in the fingers, particularly the thumb, index, and middle fingers (suggesting median nerve involvement)
- Visible deformity or angulation of the wrist (present in displaced fractures, absent in non-displaced and hairline fractures)
People taking anticoagulant medications such as warfarin, rivaroxaban, or apixaban will typically experience more rapid and extensive bruising and swelling due to impaired clot formation at the fracture site. This population also carries a higher risk of hematoma-driven compartment syndrome.
What Does a Broken Wrist Feel Like
A broken wrist feels like immediate, intense pain at the point of impact, followed within seconds by a deep, throbbing ache that is worsened by any attempt to move the wrist, grip an object, or bear weight through the palm.
The initial pain at the moment of fracture is sharp and acute. It is produced by activation of periosteal nerve fibers (densely packed nociceptors in the bone’s outer membrane) when the cortical bone disrupts. This is the same mechanism that makes even a minor shin-bone knock feel disproportionately painful: the periosteum is one of the most richly innervated tissues in the body.
After the first few minutes, the pain character shifts. The acute sharp pain is joined by a deeper, throbbing quality. This throb comes from intraosseous pressure elevation within the fractured bone’s medullary canal, where a hematoma is forming and expanding inside a rigid bony chamber. Think of it like a bruise trapped inside a sealed container with no room to expand outward: the pressure has nowhere to go, so it presses against every surrounding nerve ending continuously.
Most people also describe a profound sense that the wrist “doesn’t feel right,” even when they cannot see obvious deformity. That perception of structural wrongness is real. The bones of the radiocarpal joint have shifted even slightly from their precise geometric alignment, altering the mechanical feel of every attempted movement.
The first 20 to 30 minutes after a wrist fracture are often the least painful, because the adrenaline (epinephrine) response from the sympathetic nervous system partially suppresses pain perception. Pain typically intensifies significantly in the hour after injury as the adrenaline response fades and the inflammatory cascade builds.
Quick Tip:
- If the wrist was painful immediately at the moment of impact (not just afterward), that acute onset pattern is more consistent with fracture than with a mild sprain
- Pain that worsens rather than improves over the first two hours after injury warrants same-day evaluation by an emergency medicine physician or orthopedic surgeon
- For people with diabetes or peripheral neuropathy, fracture pain may be less sharp or less well-localized, potentially masking fracture severity
Wrist Fracture Pain: Why It Hurts and How Bad It Gets
Wrist fracture pain is produced by three overlapping physiological mechanisms: periosteal nociceptor activation, intraosseous pressure from hematoma formation, and local inflammatory mediator release from disrupted bone marrow and periosteal tissue.
The first mechanism is immediate. When cortical bone breaks, it tears through the periosteum, the densely innervated fibrous sheath that wraps every bone. Periosteal nociceptors are among the most sensitive pain receptors in the musculoskeletal system. Their activation is what produces the sharp, precise quality of fracture pain that patients reliably localize to within a centimeter of the fracture site.
The second mechanism builds over the first 30 to 90 minutes. The broken bone’s medullary canal fills with blood from disrupted intraosseous blood vessels. That hematoma creates intraosseous pressure that presses outward on the remaining periosteum and surrounding soft tissues. This pressure produces the throbbing, pulsatile quality that most people describe hours after a fracture.
The third mechanism involves the release of bradykinin, prostaglandin E2, histamine, and substance P from disrupted bone marrow cells, periosteal mast cells, and nociceptive C-fibers. These mediators sensitize surrounding nociceptors (a process called peripheral sensitization), making the entire area hypersensitive to even light touch or minor movement.
| Pain Feature | Mechanism | Timing |
|---|---|---|
| Sharp, precise, immediate pain | Periosteal nociceptor activation | Seconds after fracture |
| Deep, throbbing ache | Intraosseous pressure from hematoma | 30 to 90 minutes post-injury |
| Hypersensitivity to touch | Bradykinin and prostaglandin E2 sensitization | 1 to 6 hours post-injury |
| Pain with grip or weight bearing | Fracture site mechanical stress on sensitized nociceptors | Ongoing |
| Night pain | Intraosseous pressure not relieved by gravity when supine | First 1 to 3 nights |
According to the National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIAMS), bone pain intensity following fracture is influenced by the degree of displacement (displaced fractures hurt more), the bone involved (highly innervated periosteum of the distal radius produces more intense pain than the less well-innervated trabecular scaphoid), and the individual’s pain sensitization history, including prior chronic pain conditions.
Wrist Fracture Swelling and Bruising
Wrist fracture swelling begins within minutes of the injury and can double the apparent size of the wrist within one to two hours, driven by inflammatory vasodilation and increased vascular permeability in the fractured bone’s periosteal and soft tissue blood supply.
The swelling mechanism is specific. Bradykinin and histamine, released from disrupted periosteal tissue and bone marrow immediately after fracture, act on local capillary walls to increase their permeability. Plasma fluid and proteins leak from the capillary lumen into the interstitial tissue space, producing the soft, puffy edema visible within minutes of injury. This is the same vascular response that produces swelling around any acute tissue injury, but it is amplified in bone trauma because bone marrow contains a high density of mast cells and inflammatory precursors.
Bruising (ecchymosis) follows a different timeline. Blood from the fracture hematoma in the medullary canal must track through tissue planes before becoming visible at the skin surface. This typically takes 12 to 48 hours. Bruising that appears immediately at the skin surface after a wrist injury suggests a concurrent skin contusion or laceration rather than the fracture hematoma itself.
The location of bruising provides useful clinical information. Bruising appearing on the dorsal (back) wrist surface within 24 hours after a fall is consistent with a distal radius fracture. Bruising in the anatomical snuffbox region (between the extensor pollicis longus and extensor pollicis brevis tendons, just distal to the radial styloid) can indicate a scaphoid fracture, though its absence does not rule one out.
People on corticosteroid medications such as prednisone have thinner, more fragile skin and subcutaneous tissue, causing bruising to appear earlier and spread more extensively than in people not taking corticosteroids, even with lower-energy fractures.
Key Takeaway: Wrist fracture pain is not just a single sensation. It involves three sequential mechanisms (periosteal nociceptor activation, intraosseous pressure, and inflammatory mediator sensitization) that build on each other over the first one to six hours after injury, which is why many fractures feel worse two hours after the injury than they did at the moment of impact.
Wrist Fracture Deformity and Visible Signs
A broken wrist produces visible deformity when the fractured bone ends displace from their normal anatomical alignment, with the classic sign being the dinner-fork deformity of a Colles fracture, where the wrist angles backward and upward, resembling the profile of a dinner fork.
Deformity is the most immediately recognizable visible sign of a displaced wrist fracture. It indicates that the bone ends have shifted from their original positions, either dorsally (backward), volarly (forward), radially (thumb-side), or ulnarly (pinky-side), and in many cases involve a combination of angulation and shortening.
Not all wrist fractures produce visible deformity. Non-displaced fractures, hairline fractures, and many scaphoid fractures produce no change in wrist silhouette whatsoever. The absence of visible deformity does not exclude a fracture. This is one of the most dangerous misconceptions driving delayed care.
Visible signs of a wrist fracture that can be assessed without imaging:
- Dinner-fork deformity: dorsal angulation of the distal radius segment (Colles fracture pattern), producing a pronounced backward curve just above the wrist
- Volar (garden-spade) deformity: forward angulation of the distal radius segment (Smith fracture pattern), producing a reverse curve
- Radial shortening: the wrist appears lower on the thumb side than normal when the two hands are compared palm-down
- Visible bone ends through skin: an open (compound) fracture, constituting an immediate surgical emergency
- Skin tenting: skin stretched tight and pale over a displaced bone end without breaking through
- Rotational malalignment: the fingers appear to cross over each other when viewed edge-on (suggests rotational displacement)
According to the American Academy of Orthopaedic Surgeons, visible deformity in a wrist injury reliably indicates bony displacement and requires immediate evaluation by an emergency medicine physician, with orthopedic surgery consultation if the fracture is displaced by more than 2 millimeters or angulated by more than 10 degrees.
Distal Radius Fracture Symptoms
A distal radius fracture produces immediate pain just above the wrist on the thumb side of the forearm, rapid swelling across the dorsal wrist, tenderness directly over the distal radius, and in displaced fractures a backward angulation of the wrist that is visible and palpable.
The distal radius is the most commonly fractured bone in the wrist, accounting for the majority of all wrist fractures seen in emergency settings. It is also the most commonly fractured bone in adults under 75, according to epidemiological data cited by the American Academy of Orthopaedic Surgeons. The fracture typically occurs when the hand strikes the ground during a fall and the distal radius absorbs the primary compressive and bending force.
Symptoms specific to a distal radius fracture:
- Pain localized to the dorsal-radial wrist, approximately 1 to 3 centimeters proximal to the wrist crease
- Point tenderness directly over the distal radius on palpation
- Dinner-fork deformity in displaced Colles fractures (dorsal angulation visible and palpable)
- Radial shortening: the thumb side of the wrist appears lower when compared to the uninjured side
- Loss of ulnar variance: the distal radius fractures shorter, making the ulna appear longer by comparison
- Restricted and painful pronation and supination of the forearm (rotation around the longitudinal axis)
- In Barton fracture variants, instability of the wrist joint itself, producing a sensation that the hand is about to slide off the forearm
The Cleveland Clinic notes that distal radius fractures occur in two distinct population peaks: younger people (typically under 40) sustaining high-energy fractures from falls, sports, or motor vehicle accidents, and older adults (typically women over 60) sustaining low-energy fragility fractures from a simple ground-level fall. These two groups present with similar symptoms but often require very different treatment approaches.
Scaphoid Fracture Symptoms: The Most Commonly Missed Wrist Fracture
A scaphoid fracture classically produces pain and tenderness in the anatomical snuffbox (the small depression on the thumb side of the wrist between the extensor pollicis longus and brevis tendons), with swelling that may be surprisingly mild and no visible deformity, making it one of the most frequently underdiagnosed wrist injuries in clinical practice.
The scaphoid is the most commonly fractured carpal bone, accounting for approximately 60 to 70 percent of all carpal bone fractures, according to research published in the Journal of Hand Surgery. Its unique anatomy makes it both frequently injured and dangerously easy to miss. Most of the scaphoid’s blood supply enters through its distal pole and travels retrograde toward the proximal pole, which sits within the radiocarpal joint. A fracture through the scaphoid waist (its narrowest point) can disrupt this blood supply entirely, leading to avascular necrosis of the proximal fragment if treatment is delayed beyond four weeks.
Distinguishing symptoms of a scaphoid fracture:
- Anatomical snuffbox tenderness: pressing into the snuffbox with a fingertip reproduces sharp pain, even when the injury looks and feels relatively minor
- Pain with axial loading of the thumb: pressing the tip of the thumb toward the wrist along the long axis of the first metacarpal reproduces pain at the scaphoid waist
- Swelling that is often subtle, localized to the radial side of the wrist rather than the diffuse swelling of a distal radius fracture
- No visible deformity in the vast majority of cases
- Reduced grip strength, sometimes the only prominent symptom
- Pain that seems disproportionately mild given the mechanism of injury
Research published in the Journal of Bone and Joint Surgery has found that initial plain X-rays miss scaphoid fractures in up to 20 percent of cases. Anyone with anatomical snuffbox tenderness after a fall on an outstretched hand should have an MRI or CT scan arranged by an orthopedic or hand surgeon even if the initial X-ray is reported as normal.
Key Takeaway: The scaphoid fracture is the most dangerous wrist fracture to dismiss as a sprain. Its anatomical snuffbox tenderness, modest swelling, and absence of deformity make it easy to underestimate, but a delayed diagnosis can result in avascular necrosis, a complication that often requires surgery and produces permanent wrist dysfunction.
Hairline Wrist Fracture Symptoms
A hairline wrist fracture (stress fracture of the wrist) produces a dull, aching pain that worsens with activity and is relieved by rest, without swelling, bruising, or deformity, making it the most subtle and frequently missed wrist fracture presentation.
Hairline fractures of the wrist are incomplete cortical breaks that do not extend through the full thickness of the bone. They occur in two distinct clinical scenarios: as stress fractures from repetitive loading (common in gymnasts, weightlifters, and racket sport athletes), or as incomplete fractures from a single impact that did not generate enough force to displace the bone ends.
The symptom pattern is distinctly different from acute complete fractures. There is no sudden “crack” or immediate severe pain at the moment of injury. Instead, the person typically notices a gradually worsening ache over days to weeks, which is worse during and after activity and eases with rest. Point tenderness directly over the fracture site is usually present on careful palpation, but it may require firm pressure to reproduce.
Hairline wrist fracture symptoms by body location:
- Distal radius stress fracture: aching pain just above the wrist, worsened by push-ups, gymnastics floor exercises, or weight-bearing through the wrist
- Scaphoid stress fracture: dull radial-sided wrist pain in gymnasts and divers, tenderness in the anatomical snuffbox with deep palpation
- Ulnar styloid stress fracture: pinky-sided wrist pain, worsened by ulnar deviation movements
Athletes training in gymnastics, particularly female gymnasts under age 18, carry a disproportionately higher risk of distal radius stress fractures due to repetitive weight-bearing through open growth plates, according to research in the Journal of Bone and Joint Surgery. Standard plain X-rays often appear normal with hairline fractures. An MRI or bone scan is required for definitive diagnosis.
Broken Wrist vs Sprained Wrist: How to Tell the Difference
Distinguishing a broken wrist from a sprained wrist without imaging is not reliably possible in a clinical setting, but certain symptom features make fracture significantly more likely: immediate severe pain at the moment of impact, visible deformity, inability to grip, point tenderness directly over a bone (rather than over a ligament), and symptoms that worsen rather than improve over two to four hours.
A wrist sprain involves tearing of the ligaments connecting the carpal bones or attaching the radius and ulna to the carpus, without any bone disruption. The most commonly sprained structure is the scapholunate ligament. Sprains produce pain, swelling, and limited motion, which is exactly why they mimic fractures clinically. The differentiation matters because a missed fracture can lead to malunion (healing in a displaced position), avascular necrosis (for scaphoid fractures), or chronic instability (for ligament injuries requiring surgery).
| Feature | Fracture (More Likely) | Sprain (More Likely) |
|---|---|---|
| Pain onset | Immediate, severe at moment of impact | May develop over minutes to hours |
| Point tenderness location | Directly over bone (distal radius, scaphoid) | Over ligament space between bones |
| Swelling | Rapid, within minutes, often severe | Gradual, typically moderate |
| Deformity | Present in displaced fractures | Absent |
| Grip strength | Near-zero in displaced fractures | Reduced but often possible |
| Improvement over 2 hours | Pain worsens as adrenaline fades | Pain may plateau or mildly ease |
| Response to ice and rest | Little to no pain relief | Some pain relief typical |
| Crepitus (grating sensation) | May be present with movement | Absent |
No home assessment can confirm a fracture or a ligament injury. Any wrist injury with the features above that suggest fracture requires same-day evaluation by an emergency medicine physician or primary care physician with access to wrist X-rays. If imaging is unavailable or inconclusive and the mechanism was a fall on an outstretched hand with anatomical snuffbox tenderness, evaluation by a board-certified orthopedic surgeon or hand surgeon within 48 to 72 hours is appropriate for MRI or CT scan.
Wrist Fracture Numbness and Tingling: Nerve Involvement
Numbness and tingling in the fingers after a wrist fracture indicates compression or stretching of the median nerve, ulnar nerve, or radial nerve at or near the fracture site, and when accompanied by finger weakness, finger coldness, or absent sensation, represents a potential surgical emergency.
The most clinically important nerve in wrist fractures is the median nerve, which travels through the carpal tunnel beneath the flexor retinaculum on the volar wrist. A displaced distal radius fracture can push fractured bone fragments into the carpal tunnel, compressing the median nerve and producing acute carpal tunnel syndrome: numbness, tingling, and burning in the thumb, index finger, middle finger, and radial half of the ring finger. This distribution is the “median nerve territory” and its presence after a wrist fracture always warrants urgent evaluation.
The ulnar nerve runs through the Guyon canal (ulnar canal) on the medial wrist. A fracture of the hook of the hamate or distal ulna can compress the ulnar nerve, producing numbness in the small finger and ulnar half of the ring finger, with weakness in the intrinsic muscles of the hand.
The radial nerve is less commonly compressed by wrist fractures. When radial nerve branches are affected, numbness appears on the dorsal (back) surface of the thumb and radial hand rather than the palm.
Red flags in wrist fracture nerve symptoms that require emergency evaluation today:
- Complete loss of sensation in any finger territory (rather than just tingling)
- Inability to move one or more fingers (motor nerve involvement)
- Fingers that appear pale, mottled, or distinctly colder than uninjured fingers (vascular compromise alongside nerve involvement)
- Tingling that is progressively worsening over hours rather than stable
Key Takeaway: Numbness or tingling in specific finger distributions after a wrist fracture is not a minor or ignorable symptom. It identifies the specific nerve under compression and determines the urgency of surgical evaluation. Progressive numbness or cold fingers after a wrist fracture requires emergency medicine evaluation the same day.
Wrist Fracture Symptoms in Children
Wrist fractures in children produce the same core symptoms as adult fractures (pain, swelling, tenderness, and limited motion), but carry the additional concern of growth plate (physeal) injury, which can disrupt bone growth and requires pediatric orthopedic evaluation regardless of how mild the initial presentation appears.
Children’s bones are anatomically different from adult bones in one critical way. The growth plate (physis) is a zone of active cartilage at the ends of long bones where new bone tissue is produced. In the wrist, the distal radius physis is active until approximately age 17 in girls and 19 in boys. Growth plate cartilage is mechanically weaker than the surrounding cortical bone, which means force that would sprain an adult ligament instead fractures through the growth plate in a child.
The Salter-Harris classification describes growth plate fractures in five types (I through V), with Type I (through the physis only) being the most common and often producing no abnormality on plain X-rays. A child with wrist pain and tenderness over the distal radial physis after a fall, even with a normal X-ray, should be treated as a probable Salter-Harris Type I fracture and evaluated by a pediatric orthopedic surgeon.
Symptoms in children that differ from adult fracture presentations:
- Tenderness located at the physeal line (a specific point approximately 1 to 2 centimeters from the wrist crease on the radial side) rather than over the diaphysis (shaft)
- Children often minimize pain reporting, particularly boys, which can lead parents to underestimate injury severity
- Swelling in children tends to be more diffuse than in adults due to more elastic periosteum
- Buckle (torus) fractures of the distal radius, where the cortex buckles on one side without a complete break, are uniquely common in children aged 5 to 10 and produce mild symptoms easily dismissed as a sprain
According to the American Academy of Pediatrics, any wrist injury in a child with point tenderness over the distal radius or suspected growth plate involvement warrants evaluation by a pediatric orthopedic surgeon within 24 to 48 hours, not just primary care follow-up.
Wrist Fracture Symptoms in Older Adults and People With Osteoporosis
Wrist fractures in older adults, particularly postmenopausal women with osteoporosis, can occur from low-energy mechanisms such as a simple ground-level fall from standing height, produce the full symptom profile of acute fracture despite a mild mechanism, and carry a higher risk of comminution (bone shattering into multiple fragments) and subsequent malunion.
Osteoporosis reduces bone mineral density throughout the skeleton, including the distal radius. The National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIAMS) reports that distal radius fractures are one of the earliest clinical manifestations of osteoporosis, often occurring before hip or vertebral fractures. A wrist fracture after a low-energy fall in a woman over 60 should prompt discussion of a dual-energy X-ray absorptiometry (DEXA) scan to assess overall bone density and fracture risk.
The symptom pattern in osteoporotic wrist fractures:
- Pain from a mechanism that seems too minor to break a bone (stepping off a curb, reaching out to break a fall)
- More extensive comminution: rather than a clean two-part fracture, osteoporotic bone often fragments into three or more pieces, producing greater instability
- More pronounced deformity relative to the mechanism of injury
- Higher rate of intra-articular fracture (Barton and die-punch variants involving the joint surface)
- Slower resolution of swelling and bruising due to reduced tissue healing capacity in older adults
Older adults taking bisphosphonate medications (alendronate, risedronate) for osteoporosis have a paradoxical risk of atypical fractures with unusual X-ray appearances. These fractures may have a transverse rather than oblique pattern and occur in unusual locations. Any wrist fracture in a bisphosphonate user with an atypical X-ray appearance warrants discussion with a board-certified orthopedic surgeon about fracture classification and treatment implications.
Wrist Fracture Complications: Compartment Syndrome and Beyond
Compartment syndrome of the forearm is the most time-critical complication of a wrist fracture: rising intracompartmental pressure within the fascia-enclosed muscle compartments of the forearm begins irreversibly damaging muscle and nerve tissue when pressure exceeds 30 mmHg or comes within 30 mmHg of diastolic blood pressure, and progression to permanent injury occurs within 6 to 8 hours without surgical fasciotomy.
Think of the forearm muscles as balloons inflated inside a tight canvas bag. The bag is the fascial compartment: rigid, non-expandable, and fixed in volume. When swelling from a wrist fracture drives fluid into that compartment, pressure rises rapidly. Unlike subcutaneous tissue where swelling can spread outward, fascial compartments cannot expand. Pressure builds until the capillary blood flow to muscle and nerve is shut off entirely. Within hours, that leads to permanent muscle necrosis and nerve death.
The classic five warning signs of forearm compartment syndrome (the “5 P’s”) that constitute a surgical emergency:
- Pain disproportionate to the injury and unrelieved by elevation or ice
- Paresthesia (tingling or numbness in the fingers) that is worsening over minutes to hours
- Pallor (pale, mottled, or bluish finger color indicating compromised circulation)
- Paralysis (inability to move the fingers, indicating motor nerve compromise)
- Pulselessness (absent radial or ulnar pulse, confirming arterial occlusion)
Beyond compartment syndrome, other serious complications of wrist fractures include:
- Acute median nerve compression producing carpal tunnel syndrome (requires urgent decompression)
- Avascular necrosis of the scaphoid from delayed treatment (leads to progressive wrist arthritis)
- Complex regional pain syndrome (CRPS Type I), formerly called reflex sympathetic dystrophy, producing disproportionate pain, swelling, and autonomic dysfunction after fracture
- Malunion: fracture healing in a displaced position, causing chronic wrist pain and loss of motion
- Post-traumatic wrist arthritis from intra-articular fractures involving the radiocarpal joint surface
Emergency Symptoms: When to Call 911 or Go to the ER
Certain symptoms associated with a wrist fracture require immediate emergency evaluation. Do not wait to see if these resolve on their own.
Call 911 or go to the nearest emergency room immediately if you experience:
- Bone visible through the skin (open fracture), which constitutes an immediate infection and surgical emergency requiring operative debridement within hours
- Fingers that are pale, blue, mottled, or distinctly cold compared to the uninjured hand, which may indicate arterial injury or compartment syndrome with vascular occlusion
- Complete loss of sensation in any finger territory (not just tingling, but absent feeling), which indicates severe nerve compression or nerve injury requiring urgent decompression
- Inability to move the fingers (not just pain with movement, but complete inability), which indicates motor nerve compromise from compartment pressure or direct nerve injury
- Forearm pain that is worsening rapidly despite elevation and ice, which is the hallmark of developing compartment syndrome
- Forearm that is tense and hard to touch (firm as a board), which indicates pressure buildup within the fascial compartment
- Visible deformity of the wrist combined with absent radial pulse (the pulse point on the thumb side of the wrist), which indicates arterial injury alongside fracture
- Any wrist fracture in a child under age 10 with complete inability to move the wrist or fingers
These presentations can indicate forearm compartment syndrome, acute arterial injury, open fracture, or complete neurovascular compromise, and they require emergency surgical evaluation at a hospital emergency department, not an urgent care clinic, not a next-day orthopedic appointment, and not a phone consultation.
How a Broken Wrist Is Diagnosed
A broken wrist is diagnosed through a combination of clinical examination (point tenderness, range of motion assessment, and neurovascular evaluation) and imaging, with plain X-rays as the first-line study and MRI or CT scan reserved for cases where X-rays are normal but clinical suspicion remains high.
The clinical examination begins with a systematic inspection and palpation of each wrist bone. An experienced emergency medicine physician or orthopedic surgeon palpates the distal radius, ulnar styloid, anatomical snuffbox, and individual carpal bones in sequence, identifying the point of maximum tenderness. Point tenderness directly over the scaphoid in the anatomical snuffbox warrants MRI or CT scan regardless of X-ray findings.
The standard diagnostic pathway:
- Plain X-rays (posteroanterior, lateral, and oblique views): first-line imaging for all suspected wrist fractures. Identify most distal radius, ulnar, and displaced carpal fractures. Miss up to 20 percent of scaphoid fractures.
- CT scan: superior to X-ray for detecting fracture lines in carpal bones, assessing degree of comminution, and evaluating intra-articular involvement. Used when X-ray is inconclusive but clinical suspicion is high, or when surgical planning is required.
- MRI: the gold-standard investigation for suspected scaphoid fracture when X-ray is negative. Detects bone marrow edema at the fracture site within 24 hours of injury. Also evaluates ligament integrity (scapholunate ligament, TFCC) and detects avascular necrosis.
- Bone scan (technetium-99m scintigraphy): historically used for scaphoid fractures, now largely replaced by MRI because MRI also evaluates soft tissue structures. May be used when MRI is contraindicated (cardiac pacemaker, cochlear implant).
- Ultrasound: not a standard primary imaging modality for wrist fractures, but emerging research suggests it may identify cortical disruption in some superficial bone locations; not yet standard clinical practice.
People with metal implants or cardiac devices who cannot undergo MRI should inform their emergency medicine physician immediately, so that CT scan can be ordered as an alternative for scaphoid fracture evaluation.
Key Takeaway: A normal wrist X-ray does not exclude a wrist fracture. Scaphoid fractures are missed on initial X-ray in up to 20 percent of cases. If clinical examination finds anatomical snuffbox tenderness after a fall on an outstretched hand, an MRI or CT scan ordered by an orthopedic surgeon is the appropriate next step, even if you have already been told your X-ray looks fine.
When to Go to the ER for Wrist Fracture Symptoms
Go to the emergency room immediately for any wrist injury with visible deformity, open skin over the injury, absent radial pulse, pale or cold fingers, complete finger numbness, or worsening forearm pain, and seek same-day evaluation for any wrist injury that produces severe swelling, inability to grip, or point tenderness over bone even without deformity.
The most critical decision most people face after a wrist injury is not “is it broken?” (only imaging answers that) but “do I need to go right now, or can this wait until morning?” The following framework answers that question.
| Symptom Pattern | Action Required | Provider and Timing |
|---|---|---|
| Visible bone through skin | Emergency room now | Call 911 or go immediately |
| Absent radial or ulnar pulse | Emergency room now | Call 911 or go immediately |
| Pale, cold, or blue fingers | Emergency room now | Call 911 or go immediately |
| Complete finger numbness | Emergency room now | Emergency medicine physician today |
| Worsening forearm pain despite elevation | Emergency room now | Emergency medicine physician today |
| Visible deformity (dinner-fork shape) | Emergency room today | Emergency medicine physician same day |
| Severe swelling, near-zero grip, unable to bear weight | Emergency room or urgent care today | Same day X-ray minimum |
| Anatomical snuffbox tenderness, normal X-ray | Orthopedic or hand surgeon | Within 48 to 72 hours for MRI/CT |
| Mild wrist pain, minimal swelling, no bony tenderness | Primary care physician | Within 24 to 48 hours |
To describe your wrist injury effectively when you contact a medical provider:
- State the mechanism of injury: fall on an outstretched hand, direct blow, rotational force
- State the direction of force: hand dorsiflexed (bent back), palmar flexed (bent forward), or direct impact
- Describe where the pain is most intense: thumb side, pinky side, dorsal, volar, or central wrist
- Report whether you can move your fingers fully or not
- Report any numbness, tingling, or color change in the fingers
- Report any medications that affect bleeding (anticoagulants, aspirin, NSAIDs)
Frequently Asked Questions About Wrist Fracture Symptoms
How do I know if my wrist is broken or just sprained?
Without X-ray imaging, no one can reliably confirm a fracture or exclude one based on symptoms alone.
Fracture is more likely than a sprain when pain was immediate and severe at the moment of impact, when there is visible deformity, when grip strength is near-zero, or when there is point tenderness directly over a bone rather than over the soft tissue between bones.
Any wrist injury with those features warrants same-day X-ray evaluation by an emergency medicine physician or primary care physician with imaging access.
Can you move a broken wrist?
Some broken wrists allow limited movement, particularly non-displaced fractures, hairline fractures, and some scaphoid fractures.
The ability to move the wrist does not exclude a fracture. Scaphoid fractures in particular are notorious for allowing nearly full range of motion with only modest pain, which is why so many are initially dismissed as sprains.
Any wrist injury with ongoing pain, point tenderness over bone, and a fall on an outstretched hand mechanism warrants imaging regardless of whether the wrist can move.
What does a hairline wrist fracture feel like?
A hairline wrist fracture produces a dull, aching pain that worsens during activity and improves with rest, without visible swelling, bruising, or deformity.
Point tenderness directly over the fracture site is typically present on firm palpation, but the symptoms are mild enough that most people mistake the injury for a strain or overuse problem.
An MRI or bone scan is often required to confirm a hairline fracture because plain X-rays frequently appear normal.
How long does a broken wrist take to heal?
Healing time varies by fracture type, displacement, age, and treatment approach: non-displaced distal radius fractures typically heal in 6 to 8 weeks with casting, while displaced fractures treated surgically may require 10 to 16 weeks before return to full activity.
Scaphoid fractures heal more slowly due to the bone’s limited blood supply, often requiring 8 to 12 weeks in a cast for non-displaced fractures and longer for displaced fractures treated with surgery.
The American Academy of Orthopaedic Surgeons notes that return to full strength and range of motion after a wrist fracture often takes 6 to 12 months beyond the point when pain resolves.
Can a broken wrist heal on its own without a cast?
A minimally displaced, stable distal radius fracture can sometimes heal with immobilization in a well-fitted removable splint rather than a traditional plaster cast, but this decision is made by a board-certified orthopedic surgeon based on imaging, not by self-assessment at home.
No wrist fracture should be left completely without immobilization: displaced fractures that are not stabilized will heal in a malunited position, producing chronic pain, deformity, and loss of function.
A suspected wrist fracture requires imaging and a medical determination of stability before any decision about immobilization type is made.
What happens if a wrist fracture goes untreated?
An untreated wrist fracture heals in whatever displaced position the bone ends settle into, a complication called malunion, which produces permanent wrist deformity, chronic pain, reduced grip strength, and post-traumatic arthritis of the radiocarpal joint.
For scaphoid fractures specifically, an untreated fracture can disrupt the bone’s blood supply, causing avascular necrosis of the proximal fragment: a condition where the bone dies and collapses, producing progressive wrist arthritis that often requires reconstructive surgery.
Forearm compartment syndrome, if unrecognized in the acute setting, can result in permanent muscle necrosis (Volkmann contracture), producing a permanently contracted, non-functional hand.
Closing
A wrist injury that looks “just like a sprain” can be a scaphoid fracture with a 20 percent chance of initial X-ray miss. A wrist that is painful but moveable can have a displaced distal radius fracture. The symptoms alone cannot tell you which of these you are dealing with: that is what imaging is for. The practical takeaway is this: any wrist injury producing immediate point tenderness over bone, near-zero grip, or swelling that builds rapidly over the first hour warrants same-day evaluation by an emergency medicine physician or primary care physician with X-ray access.
Do not wait to see if it “gets better on its own.” For most wrist fractures, the window for optimal treatment is the first 48 to 72 hours. For compartment syndrome, it is six hours or less.
If you have already been told your X-ray is normal but you still have anatomical snuffbox tenderness or persistent pain with activity, ask your primary care physician or emergency physician for a referral to a board-certified orthopedic surgeon or hand surgeon for an MRI. That one step is what prevents a missed scaphoid fracture from becoming avascular necrosis.