Elbow Tendonitis Symptoms: Signs, Causes & When to Act
Elbow tendonitis symptoms typically include pain at the outer or inner elbow, a burning or aching sensation that extends into the forearm, reduced grip strength, and pain that worsens with specific wrist or elbow movements. The exact location, quality, and severity of the pain depend on which tendon is involved, how long the condition has been developing, and whether the underlying process is acute inflammation or chronic tendon degeneration.
According to the National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIAMS), overuse injuries of the elbow affect an estimated 1 to 3 percent of the adult population annually, with lateral epicondylitis (tennis elbow) accounting for the majority of cases. These conditions are not limited to athletes. The American Academy of Orthopaedic Surgeons reports that most patients with lateral epicondylitis have no history of playing tennis at all, with manual labor and repetitive occupational tasks being the dominant risk factor.
This article covers every clinically recognized form of elbow tendinopathy, from the most common to the least, with a precise anatomical and physiological explanation of why each symptom occurs, how the condition progresses, and which presentations require professional evaluation rather than home management.
Elbow Tendonitis Symptoms: The Complete Clinical Picture
Elbow tendonitis symptoms span four distinct clinical presentations depending on which tendon or tendon attachment site is injured, and recognizing the correct location of your pain is the first step toward understanding what your body is doing. Pain at the outer elbow points to the common extensor origin on the lateral epicondyle. Pain at the inner elbow points to the common flexor origin on the medial epicondyle. Pain in the front of the elbow at the bend points to the distal biceps tendon. Pain at the back of the elbow points to the triceps tendon at the olecranon.
The full spectrum of symptoms across all four presentations includes:
- Pain that is localized initially, then spreads into the forearm with continued loading
- Tenderness to firm palpation directly over the affected tendon attachment point
- Reduced grip strength, particularly when the elbow is extended
- Stiffness after rest (morning stiffness or post-activity stiffness lasting 15 to 30 minutes)
- A burning or aching quality to the pain, distinct from the sharp stabbing quality of a ligament injury
- Pain provoked by specific resisted movements (wrist extension for lateral elbow, wrist flexion for medial elbow, elbow flexion against resistance for distal biceps)
- A sensation of weakness disproportionate to the visible muscle size, reflecting the tendon’s failure to transmit force efficiently through a degenerated collagen matrix
Research published in the British Journal of Sports Medicine confirms that elbow tendinopathy symptoms follow a load-dependent pattern in the majority of patients: pain worsens with activity and improves with rest in early and moderate stages, but can become present at rest in advanced or neglected presentations.
Postmenopausal women should be aware that their reduced estrogen levels affect collagen fiber cross-linking density throughout the body, including in elbow tendons. This means tendinopathy symptoms in this group may develop more quickly and recur more readily than the same loading pattern would produce in younger or premenopausal women.
What Is Elbow Tendinopathy and How It Differs From Tendinitis
Elbow tendinopathy is the umbrella term for any pathological condition of the tendons around the elbow joint, covering both true inflammatory tendinitis and the far more clinically common degenerative condition known as tendinosis or angiofibroblastic tendinosis.
The distinction matters enormously for understanding your symptoms and what to expect. True tendinitis is an acute inflammatory process. Mechanical microtrauma to tendon collagen fibers triggers mast cell degranulation and macrophage activation, releasing prostaglandin E2 and interleukin-1 beta, producing the classic inflammatory triad of warmth, swelling, and pain. This phase is relatively short-lived, typically lasting days to two weeks.
Think of the tendon like a thick rope made of tightly organized parallel fibers. True tendinitis is the rope getting hot and irritated after a single hard pull. Tendinosis is the rope slowly fraying from thousands of small pulls, until the inner fibers are chaotic and disorganized, even though the outer sheath looks intact. The frayed rope doesn’t hurt because it’s inflamed. It hurts because the frayed fibers are generating pain signals from mechanically sensitized nerve endings every time any load is placed through them.
Tendinosis, or angiofibroblastic tendinosis (the term introduced by orthopedic surgeon Robert Nirschl based on histopathological findings published in the Journal of Bone and Joint Surgery), is characterized by fibroblast proliferation, disorganized type III collagen production, matrix metalloproteinase (MMP) activity degrading the remaining collagen matrix, and neovascularization (abnormal new blood vessel and nerve fiber ingrowth). Inflammatory cells are absent or scarce on biopsy, which is why anti-inflammatory treatments alone often fail to resolve chronic presentations.
People who have had elbow pain for more than 6 to 12 weeks are far more likely to have tendinosis than acute tendinitis. This distinction should be brought up with your primary care physician or sports medicine specialist, as it directly affects which treatments are appropriate for your stage of injury.
Elbow Tendon Anatomy and Why Tendons Get Injured
Understanding why elbow tendon injuries happen requires knowing the key structures and their mechanical roles at the elbow joint. The elbow is a compound joint with three articulations: the humeroulnar joint (flexion and extension), the humeroradial joint (flexion and load-bearing), and the proximal radioulnar joint (forearm rotation, pronation, and supination).
The extensor carpi radialis brevis (ECRB) tendon is the primary tendon involved in lateral epicondylitis. It originates from the common extensor origin on the lateral epicondyle of the humerus and runs distally to insert on the base of the third metacarpal. Its function is to extend and radially deviate the wrist. When the wrist is held in extension against resistance (as in gripping tools, a tennis racket, or typing), the ECRB generates high tensile loads at its proximal attachment, making this origin point the most mechanically vulnerable zone in the elbow.
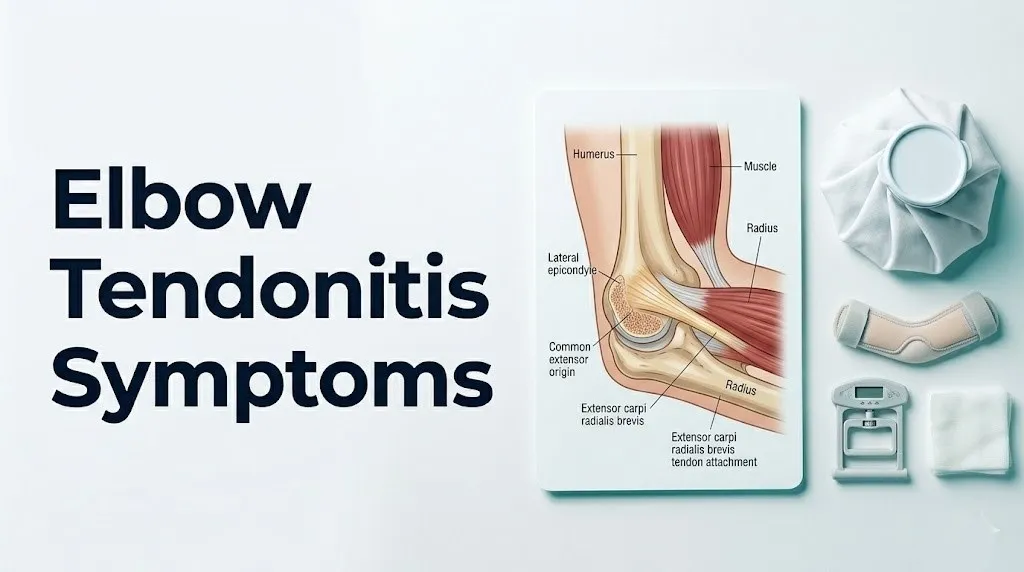
The extensor digitorum communis tendon originates at the same common extensor origin and is often involved alongside the ECRB in lateral epicondylitis. The flexor carpi radialis and pronator teres tendons originate from the common flexor origin on the medial epicondyle, and their vulnerability to repetitive loading produces medial epicondylitis.
According to the American Academy of Orthopaedic Surgeons, tendons have relatively poor intrinsic blood supply compared to muscle tissue, relying primarily on the peritendinous connective tissue (paratenon) and tenosynovial fluid for nutrient delivery. This limited vascularity is precisely why tendon injuries heal slowly and why the healing process can fail in high-demand or repeatedly loaded structures.
The radial nerve and its deep branch, the posterior interosseous nerve, pass through the radial tunnel immediately lateral and anterior to the lateral epicondyle, running beneath the extensor musculature. This proximity means that swelling or scar tissue from lateral epicondylitis can compress the posterior interosseous nerve, producing a symptom pattern that mimics or coexists with classic tennis elbow pain.
Key Takeaway: The extensor carpi radialis brevis (ECRB) tendon at the lateral epicondyle is the most commonly injured tendon in elbow tendinopathy, and chronic presentations involve collagen degeneration rather than active inflammation, which is why symptoms often persist despite anti-inflammatory treatment alone.
Lateral Epicondylitis Symptoms (Tennis Elbow)
Lateral epicondylitis produces pain on the outer side of the elbow, arising from the common extensor origin on the lateral epicondyle of the humerus, where the ECRB and extensor digitorum communis tendons attach. It is the most frequently diagnosed form of elbow tendinopathy, affecting approximately 1 to 3 percent of adults annually according to data from the American Journal of Sports Medicine.
The pain of lateral epicondylitis is typically described as burning or aching, localized to the bony prominence on the outside of the elbow, and often radiating down the forearm toward the wrist. It is provoked specifically by gripping objects, lifting with the palm facing downward (pronated grip), and extending the wrist against resistance. Turning a doorknob, lifting a coffee cup, or shaking hands can all trigger or worsen the pain in moderate-to-severe cases.
Cozen’s test (resisted wrist extension with the elbow extended) is the primary clinical provocative test used to identify lateral epicondylitis. A positive test produces pain at the lateral epicondyle with this maneuver. Mill’s test (passive wrist flexion with the elbow in full extension and forearm pronated) and the Maudsley test (resisted extension of the middle finger) are secondary confirmatory tests targeting the ECRB and extensor digitorum communis respectively.
| Symptom | Anatomical Source | Provocation |
|---|---|---|
| Outer elbow pain at bony prominence | ECRB at common extensor origin | Resisted wrist extension |
| Forearm aching radiating to wrist | Extensor digitorum communis | Gripping in pronated position |
| Weak grip with elbow extended | ECRB force transmission failure | Lifting, carrying, handshaking |
| Tenderness to palpation lateral epicondyle | Periosteum and ECRB attachment | Direct pressure on lateral epicondyle |
| Pain with resisted middle finger extension | Extensor digitorum communis | Maudsley test positive |
Lateral epicondylitis is most common in adults between 35 and 55 years of age. Men and women are affected at roughly equal rates, but the Mayo Clinic notes that women may experience slower recovery due to hormonal effects on collagen synthesis rates, particularly in the perimenopausal and postmenopausal years.
Medial Epicondylitis Symptoms (Golfer’s Elbow)
Medial epicondylitis produces pain on the inner side of the elbow at the medial epicondyle of the humerus, where the common flexor origin attaches. This site is the shared proximal attachment for the flexor carpi radialis, palmaris longus, flexor carpi ulnaris, and pronator teres tendons. The condition is named golfer’s elbow, but the majority of patients are not golfers. It affects manual workers, overhead throwers, and anyone who performs repetitive wrist flexion and forearm pronation under load.
The pain pattern in medial epicondylitis differs from lateral epicondylitis in both location and provocation. Pain is felt on the medial (inner) side of the elbow, often radiating down the inner forearm toward the wrist and ring finger. It is provoked by wrist flexion against resistance, forearm pronation, and gripping movements that require pronator teres activation (such as throwing, hammering, or swinging a golf club with a standard grip).
An important anatomical neighbor makes medial epicondylitis clinically more complex than its lateral counterpart. The ulnar nerve passes through the cubital tunnel, a fibro-osseous channel directly posterior to the medial epicondyle. In approximately 20 to 30 percent of medial epicondylitis cases, the ulnar nerve is concurrently irritated, producing numbness or tingling in the ring and little fingers alongside the inner elbow pain. This coexistence requires clinical differentiation from pure cubital tunnel syndrome.
Key symptoms of medial epicondylitis:
- Pain and tenderness directly over or just distal to the medial epicondyle
- Aching that radiates down the inner forearm with wrist flexion activities
- Grip weakness, particularly with the forearm held in a pronated (palm-down) position
- Pain with resisted wrist flexion and forearm pronation (the primary clinical tests)
- Morning stiffness of the inner elbow lasting 15 to 30 minutes after waking
Medial epicondylitis occurs less often than lateral epicondylitis. According to the AAOS, it accounts for approximately 10 to 20 percent of all elbow tendinopathy presentations. Its lower incidence reflects the fact that the flexor-pronator muscle group is generally stronger and more protected by surrounding musculature than the extensor group at the lateral elbow.
Distal Biceps and Triceps Tendinopathy Symptoms
Distal biceps tendinopathy and triceps tendinopathy are the less common but clinically distinct elbow tendon conditions that most general health content ignores entirely. Both produce pain and functional limitation at the elbow, but their symptom locations and provocative patterns are different enough to distinguish clinically from the epicondylitis presentations.
Distal biceps tendinopathy involves the distal portion of the biceps brachii tendon at its insertion on the radial tuberosity of the radius, on the front of the elbow joint (in the antecubital fossa). The pain is felt at the front of the elbow, particularly during elbow flexion and forearm supination (rotating the palm from facing down to facing up). Activities like pulling, curling weights, and turning screwdrivers produce the characteristic anterior elbow ache. The tendon is palpable and tender in the antecubital fossa in active tendinopathy.
Triceps tendinopathy involves the triceps brachii tendon at its insertion on the olecranon process of the ulna, at the back of the elbow. Pain is felt posteriorly during elbow extension, particularly resisted extension (pushing movements, overhead pressing, or the extension phase of a push-up or bench press). Direct palpation over the olecranon tip where the triceps inserts reproduces the pain.
A critical distinction for distal biceps pathology: a sudden, painful “pop” in the antecubital fossa during heavy lifting, followed by complete inability to flex the elbow against resistance and a visible bruise spreading into the forearm, indicates acute distal biceps tendon rupture, not tendinopathy. This is a surgical emergency requiring same-day evaluation by a board-certified orthopedic surgeon.
| Condition | Pain Location | Provocative Movement | Key Anatomical Structure |
|---|---|---|---|
| Distal biceps tendinopathy | Front of elbow, antecubital fossa | Resisted elbow flexion, supination | Biceps brachii tendon at radial tuberosity |
| Triceps tendinopathy | Back of elbow, over olecranon | Resisted elbow extension, push movements | Triceps brachii tendon at olecranon |
| Distal biceps rupture (emergency) | Front of elbow with ecchymosis, gap | Complete loss of flexion strength | Ruptured distal biceps tendon |
Overhead athletes (weightlifters, gymnasts, baseball players, volleyball players) are disproportionately affected by both distal biceps and triceps tendinopathy. A board-certified sports medicine physician or orthopedic surgeon should evaluate anterior or posterior elbow pain that does not respond to activity modification within 4 to 6 weeks.
Key Takeaway: Pain at the front of the elbow provoked by pulling or curling movements suggests distal biceps tendinopathy. A sudden pop with complete loss of elbow flexion strength is a surgical emergency requiring same-day orthopedic evaluation.
Elbow Pain When Gripping or Lifting
Pain during gripping and lifting is the most functionally disabling elbow tendonitis symptom, affecting both work capacity and daily activities, and it occurs because the elbow tendons are the primary force transmitters between the forearm muscles and the bones they move. When the tendon matrix is disrupted by tendinosis, force transmission through the tendon becomes mechanically inefficient and painful.
The mechanics work like this. When you grip an object, the extensor carpi radialis brevis contracts to stabilize the wrist in extension, allowing the finger flexors to generate grip force. In lateral epicondylitis, this ECRB contraction loads the degenerated tendon origin at the lateral epicondyle, stimulating the substance P-releasing nerve endings embedded in the angiofibroblastic tissue, producing immediate lateral elbow pain. The more extended the elbow position during gripping, the greater the mechanical disadvantage of the ECRB, and the more intense the pain.
This is why elbow tendonitis patients typically report that grip strength is worst when the elbow is fully extended (arm straight) and somewhat better when the elbow is bent to 90 degrees. A carpenter holding a hammer with an outstretched arm, or a person lifting a laptop from a desk with a straight elbow and palm-down grip, experiences far more tendon loading than someone performing the same grip with the elbow bent.
To describe gripping and lifting pain to your doctor accurately:
- Note the exact elbow position that triggers pain (straight arm, bent arm, or both).
- Note whether the grip is palm-up (supinated), palm-down (pronated), or neutral.
- Note the weight at which pain begins (a coffee cup? A grocery bag? A specific tool weight?).
- Note whether pain begins during the activity or after the activity has ended.
- Record whether grip weakness causes you to drop objects, as this is a red flag for significant tendon compromise.
People with rheumatoid arthritis affecting the elbow joint can experience grip weakness and elbow pain that mimics tendinopathy but arises from joint synovitis or tendon involvement within the joint itself rather than an overuse mechanism. A board-certified rheumatologist should evaluate elbow pain with grip weakness in any person with a known or suspected inflammatory arthritis diagnosis.
Forearm Pain and Weakness From Elbow Tendonitis
Forearm pain radiating from the elbow is one of the most misunderstood elbow tendonitis symptoms, because patients often localize the pain to the forearm and assume the forearm muscle is strained rather than recognizing that the source is the tendon at the elbow. This misattribution delays appropriate evaluation and management.
The physiological reason for forearm pain radiation is twofold. First, the extensor and flexor tendons of the elbow are the proximal attachment points of muscles that run the full length of the forearm. When the tendon attachment is inflamed or degenerating, the tensile stress is distributed along the entire muscle-tendon unit, producing aching throughout the forearm musculature. Second, in cases where the posterior interosseous nerve (the deep branch of the radial nerve, passing through the radial tunnel beneath the extensor musculature) is compressed or irritated by adjacent tendinopathic tissue, pain referral follows the nerve’s distribution into the lateral forearm and wrist.
Forearm weakness in elbow tendinopathy has a specific character: it is not paralytic weakness (the muscle simply will not activate) but rather load-dependent weakness, where the muscle can generate force at low loads but fails quickly under higher demands. This reflects the tendon’s reduced capacity to transmit the force the muscle is producing, not an intrinsic muscle problem.
Research published in the British Journal of Sports Medicine found that patients with chronic lateral epicondylitis show measurable reductions in grip strength dynamometry of approximately 40 percent compared to the unaffected limb, and that forearm pain scores correlate more strongly with tendon Doppler signal (indicating neovascularization) than with MRI signal intensity changes.
Musicians who play plucked string instruments (guitarists, harpists) or keyboard instruments with high finger repetition rates frequently develop elbow tendinopathy with prominent forearm pain and fatigue as the primary complaint rather than focal elbow pain. A board-certified sports medicine physician or physiatrist with experience in performing arts medicine should evaluate these presentations, as standard occupational guidance does not adequately address the specific biomechanical demands of instrument-specific technique.
Elbow Stiffness and Swelling Symptoms
Elbow stiffness and swelling are secondary symptoms of tendinopathy that develop alongside pain in moderate-to-advanced presentations and are frequently underreported by patients who focus exclusively on the pain quality. Recognizing them matters because their pattern of onset, timing, and characteristics provide important clinical information about the stage and type of tendon injury.
Stiffness in elbow tendonitis presents as a sensation of limited range of motion or resistance to movement, typically most pronounced in the first 15 to 30 minutes after waking or after prolonged rest. This pattern is called post-rest stiffness or gelling (a term from rheumatology describing the tendency of inflamed or tendinopathic tissue to stiffen during periods of inactivity). In lateral or medial epicondylitis, stiffness appears as resistance to full elbow extension or wrist flexion and extension, not a complete loss of joint movement as seen in joint arthritis.
Swelling in elbow tendinopathy is usually subtle and localized to the area directly over the affected tendon attachment. At the lateral epicondyle, slight soft tissue fullness may be palpable compared to the unaffected elbow. Frank visible swelling (the elbow appearing obviously enlarged) is more characteristic of olecranon bursitis (fluid accumulation in the olecranon bursa, a distinct fluid-filled sac at the tip of the elbow) than of tendinopathy itself, and this distinction is diagnostically important.
According to the Mayo Clinic, significant visible elbow swelling after a traumatic injury warrants X-ray imaging to rule out fracture of the radial head, olecranon, or lateral condyle before attributing the presentation to tendinopathy alone. Swelling with warmth, redness, and systemic fever raises concern for septic olecranon bursitis and requires urgent medical evaluation.
Older adults over 65 tend to experience greater post-rest stiffness from elbow tendinopathy than younger adults, partly because age-related changes in tendon viscoelastic properties reduce the tendon’s ability to rapidly redistribute load after rest, and partly because concurrent degenerative changes in the elbow joint cartilage (elbow osteoarthritis) compound the stiffness picture. A board-certified orthopedic surgeon or rheumatologist should evaluate elbow stiffness in older adults before initiating any physical therapy program, to ensure the stiffness source is accurately identified.
Key Takeaway: Post-rest stiffness lasting 15 to 30 minutes at the elbow is characteristic of tendinopathy at any stage. Visible joint swelling with warmth, redness, or fever suggests a different diagnosis (bursitis, fracture, or infection) requiring prompt medical evaluation, not self-management.
Acute vs. Chronic Elbow Tendonitis Symptoms
The symptom experience of elbow tendinopathy changes substantially depending on whether the condition is in its acute phase or has progressed to a chronic presentation, and understanding this distinction shapes both patient expectations and clinical decision-making in ways that no generic symptom list captures.
Acute elbow tendinopathy (first days to six weeks) presents with:
- Pain that is sharp and immediate during provocative activity
- Localized warmth and mild swelling at the tendon origin on palpation
- Rest providing substantial pain relief within minutes of stopping the provocative activity
- Night pain that is minimal or absent
- Tenderness that is highly localized to the specific tendon attachment point
- Grip strength that is reduced with the elbow loaded but recovers quickly with rest
Chronic elbow tendinopathy (beyond 12 weeks, often months to years in untreated presentations) presents with:
- A dull, constant aching quality replacing the sharp acute pain
- Pain that is now present at rest and may wake the patient from sleep
- Stiffness that does not fully resolve with warm-up activity
- Diffuse tenderness extending beyond the original attachment point
- Grip weakness that persists even after adequate rest periods
- Reduced response to anti-inflammatory treatments (reflecting the shift from tendinitis to tendinosis)
- Possible visible tendon thickening palpable at the affected attachment site
| Feature | Acute (Less Than 6 Weeks) | Chronic (More Than 12 Weeks) |
|---|---|---|
| Pain quality | Sharp, activity-provoked | Dull, persistent, may be present at rest |
| Rest response | Rapid improvement | Partial improvement at best |
| Swelling | May be present, warm | Usually absent or subtle |
| Grip weakness | Activity-dependent | Persistent, may drop objects |
| Night pain | Typically absent | Can be present |
| Response to NSAIDs | Partial to good | Poor (tendinosis mechanism) |
| Biopsy histology | Inflammatory cells present | Angiofibroblastic changes, no inflammatory cells |
People taking systemic corticosteroids (prednisone, methylprednisolone) for other medical conditions have an altered presentation profile: their inflammatory symptoms are pharmacologically suppressed, which can mask the acute phase and allow tendinopathy to progress to advanced tendinosis before pain becomes prominent enough to seek evaluation. A board-certified sports medicine physician should be made aware of any systemic corticosteroid use when assessing elbow pain.
Elbow Tendonitis Symptoms in Athletes and Manual Workers
Athletes in racquet sports, throwing sports, overhead sports, and manual workers performing repetitive upper limb tasks represent the highest-risk populations for elbow tendinopathy, and their symptom presentations carry specific clinical features tied to their loading patterns.
In racquet sport athletes (tennis, squash, badminton), lateral epicondylitis symptoms typically develop in the dominant arm and are provoked by the backhand stroke, which requires simultaneous wrist extension and elbow extension under load. The pain is worst during ball impact and in the follow-through phase. In overhead throwing athletes (baseball pitchers, javelin throwers), medial epicondylitis symptoms are more common due to the valgus stress and wrist flexion forces generated during the acceleration phase of throwing. The pain is felt at the medial elbow at ball release and may be accompanied by inner elbow ligament stress.
Manual workers (carpenters, painters, plumbers, electricians, assembly line workers) tend to develop elbow tendinopathy insidiously, without a single clear onset event. The pain develops gradually over weeks to months, often becoming noticeable only when it interferes with work productivity. This delayed recognition frequently allows the condition to progress from acute tendinitis to chronic tendinosis before clinical evaluation occurs.
According to a systematic review published in the American Journal of Sports Medicine, workers who perform repetitive wrist extension or gripping movements for more than 2 hours per day have approximately 6 times the risk of developing lateral epicondylitis compared to the general working population.
Quick Tip:
- Athletes should document the specific motion or stroke that first triggered elbow pain, as this information directly guides the physical examination and treatment plan.
- Manual workers should report elbow symptoms to an occupational health physician early, before the condition becomes chronic, as ergonomic workstation modification is most effective when implemented in the acute phase.
- Left-handed athletes and workers should note that their dominant-arm tendons are exposed to the same loading patterns, and non-dominant arm tendinopathy may be missed if clinicians default to examining only the dominant side.
Elbow Tendonitis Symptoms in Older Adults and People With Diabetes
Two populations experience elbow tendinopathy with clinically distinct symptom patterns and higher complication risks: older adults over 50 and people living with type 2 diabetes mellitus. Both groups have biological reasons for more severe, more persistent, and more treatment-resistant tendinopathy.
In older adults, progressive age-related changes in tendon tissue biology alter the injury presentation. Aging tendons show decreased cellularity (fewer fibroblasts available to attempt repair), reduced production of proteoglycans that maintain tendon water content and resilience, and higher baseline levels of disorganized collagen from accumulated microtrauma. These changes mean that older adults develop tendinopathy at lower repetitive loading thresholds than younger adults, their symptoms progress from acute to chronic more rapidly, and their healing timelines are substantially longer.
The NIAMS notes that the peak incidence of lateral epicondylitis in the general population occurs between ages 40 and 60, with the condition tending to be more persistent and functionally limiting in adults over 55 compared to younger patients with equivalent loading histories.
In people with type 2 diabetes, the mechanism involves advanced glycation end-products (AGEs), formed when excess blood glucose non-enzymatically binds to collagen fibers in tendons. This glycation stiffens and weakens the collagen matrix, reduces the tendon’s ability to respond to mechanical loading adaptively, and impairs the healing cascade. Research published in the Journal of Bone and Joint Surgery found that people with diabetes are up to three times more likely to develop tendinopathy than age-matched individuals without diabetes, and their tendon pathology is more extensive on imaging at equivalent symptom severity.
| Population | Biological Mechanism | Clinical Implication |
|---|---|---|
| Adults over 55 | Reduced fibroblast cellularity, lower proteoglycan content | Slower healing, higher recurrence rate |
| People with type 2 diabetes | AGE-mediated collagen glycation, impaired healing cascade | More extensive tendon changes, worse treatment response |
| Postmenopausal women | Reduced estrogen, lower collagen synthesis and cross-linking | Faster progression, higher recurrence |
| Fluoroquinolone antibiotic users | MMP upregulation by drug mechanism, collagen degradation | Increased tendon rupture risk, requires urgent evaluation |
People with diabetes who develop elbow tendon symptoms should inform their primary care physician and be evaluated by a board-certified sports medicine physician or orthopedic surgeon, as standard rehabilitation timelines significantly underestimate the healing duration for this population and may need to be adjusted accordingly.
Key Takeaway: People with type 2 diabetes develop elbow tendinopathy at higher rates, with more extensive tendon changes, and slower healing responses due to AGE-mediated collagen glycation. Standard healing timelines should not be applied to this population without clinical assessment.
Elbow Tendonitis Warning Signs and Red Flags
Most elbow tendinopathy follows a predictable, gradual course, but specific symptom patterns signal that the condition has progressed beyond straightforward overuse tendinopathy and may involve a complication, a concurrent diagnosis, or a condition requiring urgent evaluation.
Warning signs that require prompt professional evaluation:
- Neurological symptoms in the hand or fingers: numbness, tingling, or weakness in specific finger distributions (ring and little finger suggesting ulnar nerve involvement at the cubital tunnel; thumb, index, and middle finger suggesting radial or median nerve involvement) indicate nerve compression that must be evaluated separately from the tendon condition
- Complete sudden loss of elbow flexion strength with a palpable gap in the antecubital fossa and immediate bruising spreading into the forearm indicates distal biceps tendon rupture, a surgical emergency
- Elbow locking or catching: the sensation of the elbow joint catching, locking, or giving way suggests an intra-articular loose body, osteochondral lesion, or joint pathology distinct from tendinopathy
- Pain at rest that does not respond to any position change: persistent unrelenting rest pain raises concern for infection, tumor, or inflammatory arthropathy rather than mechanical tendinopathy
- Rapid visible elbow swelling after trauma: suggests fracture (radial head, lateral condyle, olecranon) requiring immediate imaging
- Swelling with warmth, redness, and fever: the triad of a red, warm, swollen elbow with systemic fever is the clinical pattern of septic olecranon bursitis or elbow joint septic arthritis, requiring emergency medical evaluation and potential joint aspiration
- Elbow pain in a child or adolescent: tendinopathy at growth plate attachment sites (apophysitis) follows a different mechanism in skeletally immature individuals and requires pediatric orthopedic evaluation rather than standard adult tendinopathy management
People taking fluoroquinolone antibiotics (ciprofloxacin, levofloxacin, moxifloxacin) should be aware that this antibiotic class is associated with tendon pathology and rupture through MMP upregulation, as confirmed by a U.S. Food and Drug Administration (FDA) black box warning. Any new elbow pain or tendon discomfort during or shortly after a fluoroquinolone course requires immediate medical evaluation.
When to See a Doctor for Elbow Tendonitis Symptoms
Specific clinical thresholds determine when elbow tendinopathy symptoms move beyond the self-monitoring phase and require professional evaluation. Waiting too long to seek care allows acute tendinitis to progress to chronic tendinosis, narrows treatment options, and extends the overall recovery timeline.
See a primary care physician or board-certified sports medicine physician if:
- Elbow pain has persisted for more than 4 to 6 weeks despite activity modification and rest
- The pain is interfering with work, sleep, or daily activities
- Grip strength has measurably declined (you are dropping objects or unable to perform tasks requiring grip)
- You have had a previous elbow tendinopathy in the same arm that has recurred
See a board-certified orthopedic surgeon same-day or within 24 hours if:
- You felt or heard a pop in the elbow during a loading activity, followed by immediate weakness
- The elbow cannot be fully extended or flexed compared to the other arm after an acute event
- You notice a visible deformity or a palpable gap in the tendon
Go to the emergency room immediately if:
- The elbow is swollen, red, warm, and you have a fever (septic joint or bursitis)
- You have completely lost the ability to flex your elbow against gravity after a loading injury
- You sustained an elbow injury with a direct impact and have severe swelling and tenderness at the radial head (radial head fracture presentation)
To prepare for your first appointment:
- Write down when the pain started, the specific activity that triggered it, and which movements make it worse.
- Bring a list of all medications, including fluoroquinolone antibiotics taken in the past 6 months.
- Note whether you have been given any corticosteroid injections to this elbow previously, and when.
- Describe the pain quality (burning, sharp, aching, constant, activity-only) and a pain score on a 0-to-10 scale.
- Note whether you have any numbness or tingling in the hand or fingers alongside the elbow pain.
People with bleeding disorders or those on anticoagulant therapy should disclose this to their physician before any evaluation, as it affects the safety of diagnostic joint aspiration and certain injection procedures.
How Elbow Tendonitis Is Diagnosed
Elbow tendinopathy diagnosis is primarily clinical, meaning a physician’s history and physical examination are the most important diagnostic tools. Imaging plays a confirmatory and exclusionary role rather than a primary diagnostic role in most presentations.
The standard diagnostic process for elbow tendinopathy unfolds as follows:
- History: The clinician asks about onset, duration, mechanism, specific provocative activities, prior treatments, occupation, sport involvement, and medications including fluoroquinolone use or corticosteroid history.
- Inspection: The elbow is examined for visible swelling, muscle atrophy (suggesting chronic neurological involvement), or deformity.
- Palpation: The clinician palpates the lateral epicondyle, medial epicondyle, antecubital fossa, and olecranon systematically, noting the exact location and character of tenderness. A point of maximum tenderness directly at the common extensor origin is highly characteristic of lateral epicondylitis.
- Provocative testing: Cozen’s test, Mill’s test, and the Maudsley test for lateral epicondylitis. Resisted wrist flexion and pronation for medial epicondylitis. Resisted elbow flexion in supination for distal biceps tendinopathy. These tests have documented sensitivity and specificity values in the clinical literature.
- Grip strength dynamometry: Measuring grip strength bilaterally with a hand dynamometer quantifies the functional deficit and provides an objective baseline for monitoring treatment progress.
- Musculoskeletal ultrasound: Diagnostic ultrasound is the preferred initial imaging modality for elbow tendinopathy. It can identify tendon thickening, hypoechoic areas indicating collagen disorganization, and neovascularization on Doppler imaging (a hallmark of tendinosis). It is dynamic, inexpensive, and available in most sports medicine offices.
- Magnetic resonance imaging (MRI): Reserved for cases where the diagnosis is uncertain, where surgical planning is needed, or where concurrent ligamentous or intra-articular pathology must be ruled out. MRI shows tendon signal changes in the ECRB and can identify partial or complete tendon tears.
- Plain film radiography (X-ray): Used to rule out fracture, calcific tendinopathy deposits, or elbow osteoarthritis rather than to confirm tendinopathy directly.
The AAOS recommends that clinical examination by an experienced physician or physical therapist has adequate diagnostic accuracy for typical elbow tendinopathy presentations, and that imaging is not required before initiating a structured rehabilitation program in straightforward cases.
Elbow Tendonitis vs. Other Elbow Conditions
Elbow tendinopathy shares symptom features with several other elbow conditions, and accurately distinguishing between them requires clinical examination rather than self-assessment based on symptom description alone. Several conditions are particularly important to differentiate.
Radial tunnel syndrome is compression of the posterior interosseous nerve as it passes through the radial tunnel, producing pain in the outer elbow and proximal forearm that closely mimics lateral epicondylitis. The distinction: radial tunnel syndrome pain is typically more distal (2 to 3 centimeters below the lateral epicondyle, over the radial tunnel), the provocative tests differ (resisted supination and resisted middle finger extension with the elbow flexed), and grip strength is often preserved while forearm fatigue with repetitive activities is more prominent.
Cubital tunnel syndrome compresses the ulnar nerve at the medial elbow, producing inner elbow aching alongside numbness and tingling in the ring and little fingers. This pattern overlaps with medial epicondylitis. The presence of neurological symptoms (numbness, tingling, clumsy fine motor control) strongly favors cubital tunnel syndrome, while focal tenderness directly at the medial epicondyle with neurological symptoms favors coexisting pathology.
Olecranon bursitis produces swelling at the tip of the elbow (the olecranon), which can be mistaken for elbow joint swelling. The swelling in bursitis is posterior and freely mobile under the skin. Tendinopathy does not produce this pattern of freely mobile soft tissue swelling at the elbow tip.
| Condition | Key Differentiating Feature | Provider for Evaluation |
|---|---|---|
| Lateral epicondylitis | Tenderness at lateral epicondyle, positive Cozen’s test | Primary care or sports medicine |
| Radial tunnel syndrome | Pain below lateral epicondyle, neurological forearm symptoms | Board-certified orthopedic surgeon or neurologist |
| Cubital tunnel syndrome | Numbness ring/little finger, positive Tinel’s at cubital tunnel | Board-certified orthopedic surgeon or neurologist |
| Olecranon bursitis | Freely mobile posterior elbow swelling | Primary care, possible aspiration |
| Elbow osteoarthritis | Pain throughout movement arc, crepitus, limited range | Board-certified orthopedic surgeon |
| Medial collateral ligament injury | Medial instability, valgus stress pain, throwing athletes | Board-certified orthopedic surgeon |
A nerve conduction velocity (NCV) study and electromyography (EMG) are the definitive diagnostic tests for nerve compression syndromes at the elbow. These studies, ordered by a board-certified neurologist or physiatrist, distinguish peripheral nerve compression from referred pain caused by tendinopathy and from cervical radiculopathy (nerve root compression in the neck producing arm and elbow pain).
Key Takeaway: Elbow pain with numbness or tingling in any finger requires urgent differentiation from tendinopathy alone. Nerve compression syndromes (radial tunnel syndrome, cubital tunnel syndrome) coexist with or mimic tendinopathy and require NCV and EMG testing for confirmation.
Urgent Situations: When Elbow Symptoms Require Immediate Care
Certain elbow symptoms associated with tendinopathy presentations require evaluation the same day or immediately. Do not wait to see if these resolve on their own.
Go to the emergency room or call a board-certified orthopedic surgeon immediately if you experience:
- A sudden, painful pop in the front of the elbow during a lifting activity, followed by complete inability to flex the elbow against resistance and bruising spreading into the forearm. This is the clinical presentation of acute distal biceps tendon rupture, a surgical emergency. The window for optimal surgical repair is narrow. Do not apply ice and monitor at home.
- Elbow swelling with redness, warmth, and a fever above 38.5 degrees Celsius (101.3 degrees Fahrenheit). This triad indicates possible septic olecranon bursitis or septic elbow joint arthritis, both of which require emergency evaluation and joint aspiration or drainage.
- Sudden complete loss of elbow extension strength after a direct posterior elbow impact. This may indicate triceps tendon avulsion at the olecranon, a rare but surgically time-sensitive injury.
- Elbow pain after high-energy trauma (motor vehicle accident, fall from height, sports collision) with visible deformity, inability to move the joint, or rapid swelling. These presentations require immediate imaging to rule out fracture-dislocation of the elbow.
- Progressive hand weakness, inability to make a fist, or loss of finger extension developing alongside lateral elbow pain. This pattern suggests posterior interosseous nerve palsy, which requires urgent neurological and orthopedic evaluation.
These presentations can indicate distal biceps tendon rupture, triceps avulsion, septic arthritis, elbow fracture-dislocation, or posterior interosseous nerve palsy. These require emergency or same-day surgical or medical assessment, not an urgent care visit or a wait-and-see approach.
Frequently Asked Questions About Elbow Tendonitis Symptoms
What does elbow tendonitis feel like?
Elbow tendonitis typically feels like a burning or aching pain localized to the outer or inner elbow that worsens with gripping, wrist movement, or lifting.
The pain often radiates down the forearm, and grip strength decreases during activity because the tendon’s degenerated collagen matrix cannot efficiently transmit the force the forearm muscles are generating.
In chronic presentations, the pain can shift from activity-only to a persistent dull ache that is present at rest, reflecting the transition from acute tendinitis to tendinosis.
How do I know if I have tendonitis in my elbow or something else?
Elbow tendonitis produces pain localized to the epicondyle area, provoked by specific resisted wrist or elbow movements, without neurological symptoms (numbness or tingling) in most cases.
If you have numbness or tingling in your fingers alongside elbow pain, this suggests nerve involvement (radial tunnel syndrome or cubital tunnel syndrome) that requires clinical differentiation from tendinopathy alone.
A primary care physician or sports medicine physician can distinguish elbow tendinopathy from competing diagnoses using provocative clinical tests (Cozen’s test, Mill’s test, Tinel’s sign at the cubital tunnel) and imaging when needed.
Can elbow tendonitis cause numbness or tingling in my fingers?
Standard elbow tendinopathy does not itself cause numbness or tingling in the fingers, as tendon tissue does not directly compress nerve pathways.
However, approximately 20 to 30 percent of medial epicondylitis cases involve concurrent ulnar nerve irritation in the cubital tunnel, producing numbness and tingling in the ring and little fingers alongside inner elbow pain.
Lateral elbow pain with any neurological finger symptoms should be evaluated by a board-certified orthopedic surgeon or neurologist to rule out posterior interosseous nerve entrapment or cervical radiculopathy.
Does elbow tendonitis hurt all the time or only with movement?
In the early and moderate stages, elbow tendinopathy pain is typically activity-dependent, appearing with provocative movements and improving with rest within minutes.
In advanced or long-standing cases, particularly when the condition has progressed to tendinosis, pain can become persistent and present at rest, including during sleep, reflecting ongoing nociceptor sensitization from substance P and glutamate in the degenerating tendon.
Elbow pain that is constant, present at rest, and unresponsive to any position change warrants evaluation by a primary care physician to rule out causes other than tendinopathy, including inflammatory arthropathy, infection, or referred pain from the cervical spine.
How long does elbow tendonitis take to heal?
Acute elbow tendinitis resolves in most patients within 6 to 12 weeks with appropriate activity modification and a structured rehabilitation program supervised by a licensed physical therapist.
Chronic elbow tendinosis, the degenerative form involving angiofibroblastic changes in the tendon matrix, typically requires 6 to 18 months for meaningful functional recovery, and in some patients symptoms persist for 2 years or more without appropriate management.
People with type 2 diabetes, older adults over 55, and those who have received multiple corticosteroid injections in the same tendon should expect longer healing timelines and should discuss realistic prognosis with a board-certified sports medicine physician or orthopedic surgeon.
When is elbow tendonitis a medical emergency?
Elbow tendinopathy itself is not a medical emergency, but specific presentations associated with elbow tendon pathology require immediate care.
A sudden painful pop in the front of the elbow during lifting with immediate loss of elbow flexion strength, bruising, and a palpable gap indicates distal biceps tendon rupture, which is a surgical emergency requiring same-day evaluation by a board-certified orthopedic surgeon.
Go to the emergency room immediately for any elbow presentation with red, warm, swollen joint and fever (septic joint), visible elbow deformity after trauma, or progressive hand weakness developing alongside elbow pain.
Closing
Elbow tendonitis symptoms are more specific, more mechanistically distinct, and more clinically differentiated than any generic symptom list suggests. The location of your pain (lateral, medial, anterior, or posterior elbow) tells you which tendon is involved. The quality of the pain (sharp and activity-only versus dull and persistent) tells you whether the process is acute or chronic. The presence or absence of neurological symptoms tells you whether the picture involves tendon alone or nerve compression alongside it.
The most actionable thing to take from this: if your elbow pain has lasted more than 4 to 6 weeks, or if you have grip weakness, rest pain, or any finger numbness, schedule an appointment with your primary care physician or a board-certified sports medicine physician. Bring the date the pain started, the specific movements that aggravate it, and a list of any medications you are taking. A clinical examination takes 15 minutes and answers questions that months of self-management cannot.
Your elbow pain has a specific anatomical source. Knowing which structure is involved is the first step toward addressing it correctly.