Blood Clot in Foot Symptoms: Signs You Should Not Ignore
Blood clot in foot symptoms include persistent localized pain, swelling, skin warmth, and visible color changes ranging from redness to a bluish or dusky tone. These symptoms arise when a thrombus forms in the deep venous system of the foot, partially or fully obstructing blood flow and triggering an inflammatory response in the surrounding tissue.
According to the Centers for Disease Control and Prevention, venous thromboembolism affects between 300,000 and 600,000 Americans each year, and deep vein thrombosis of the lower extremity, including the foot and calf, accounts for a substantial portion of those cases. Isolated pedal DVT (a clot confined to the veins of the foot itself) is frequently underrecognized because its symptoms can mimic common non-vascular foot problems like plantar fasciitis, gout, or a minor soft tissue injury.
This article explains the full clinical picture: what a foot blood clot actually feels like from the inside, how symptoms differ depending on which vein is involved and where in the foot the clot sits, which populations face higher risk, how clinicians diagnose it, and exactly when you need emergency evaluation rather than a scheduled appointment.
Blood Clot in Foot Symptoms: What You Need to Know First
Blood clot in foot symptoms reflect a blockage in the deep venous system of the foot, which disrupts normal blood return to the heart and activates a local inflammatory cascade that produces pain, swelling, warmth, and skin discoloration.
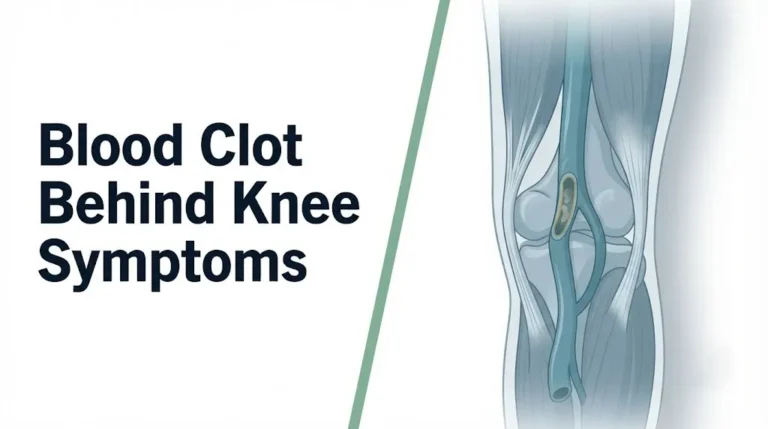
The foot contains two main venous networks. The plantar venous arch drains the sole and connects to the posterior tibial and fibular veins. The dorsal venous network drains the top of the foot and flows into the great and small saphenous veins and ultimately the popliteal vein behind the knee. A clot can form in either network. The location within these networks determines where symptoms appear and how severe they feel.
Not every foot clot produces dramatic or obvious symptoms. A 2018 analysis published in the journal Thrombosis and Haemostasis found that approximately 25 to 30 percent of confirmed distal DVT cases present with mild or non-specific symptoms that patients initially attribute to muscle strain or overuse. This matters because a clot that goes unrecognized can extend proximally toward the popliteal and femoral veins, substantially increasing the risk of pulmonary embolism.
The cardinal symptoms to know:
- Aching, throbbing, or cramping pain in the foot that worsens with standing or walking
- Visible swelling that may be confined to one area of the foot or spread to the ankle
- Skin warmth over the affected area, sometimes detectable by comparison with the other foot
- Skin color change ranging from pink-red to a darker livid or bluish tone
- A sensation of heaviness or tightness in the foot that does not improve with elevation in the first few minutes
- Tender, cord-like firmness along the path of an affected vein, detectable with gentle palpation
People taking anticoagulants for an unrelated condition may experience attenuated symptoms even with an active clot, since anticoagulation limits clot growth but does not always prevent it entirely.
What Does a Blood Clot in the Foot Feel Like?
A blood clot in the foot most often feels like a deep, aching, or throbbing pain that is localized rather than diffuse, does not improve with rest alone, and is accompanied by at least one other physical sign such as swelling, warmth, or skin color change.
The pain pattern differs from the sharp, stabbing quality of plantar fasciitis, which is typically worst at the heel on the first steps of the morning. A clot-related pain tends to be constant or near-constant, seated deeper in the foot than the surface of the skin, and worsens with dependent positioning (letting the foot hang down) rather than improving with it. Elevating the foot above heart level may reduce swelling temporarily, but the underlying ache often persists.
Think of it this way: a blocked vein in the foot is like a clogged drain in a sink. Fluid backs up. Pressure builds. The surrounding tissue becomes engorged and tense. That pressure is transmitted through the tissue, which is why the pain feels diffuse and heavy rather than sharp and point-specific like a stone bruise or stress fracture.
Many patients describe the sensation as:
- A dull, persistent cramping that feels like a muscle is perpetually contracting without releasing
- Tightness or fullness across the arch or dorsum of the foot
- A burning quality along the inner ankle if the posterior tibial vein is involved
- Pain that radiates upward toward the calf if the clot extends proximally into the tibial veins
- A sense that the foot is “too full” inside, as if the skin is stretched from within
People with peripheral neuropathy (nerve damage from diabetes or other conditions) may experience diminished pain sensation even with an active DVT, making skin color change and swelling the more reliable early indicators in that population.
Symptoms of Blood Clot on Top of Foot
Symptoms of a blood clot on top of the foot originate from the dorsal venous network, and they typically produce visible swelling, redness, and tenderness across the dorsum (upper surface) of the foot, often following the path of a specific vein.
When a clot forms in the dorsal venous network, the affected vein may become visibly prominent, firm, and tender along its course. The skin overlying the vein often turns red or pink, and the surrounding tissue swells with fluid that has leaked from capillaries under elevated venous hydrostatic pressure. The inflammatory mediators released by activated platelets and damaged endothelial cells, including prostaglandins and interleukin-6, produce the local warmth and redness that accompany the swelling.
/

A clot confined to a superficial vein on the top of the foot is technically superficial thrombophlebitis rather than deep vein thrombosis. This is an important clinical distinction because superficial thrombophlebitis carries a lower immediate risk of pulmonary embolism than DVT. However, according to the American College of Chest Physicians, superficial thrombophlebitis extending within 3 centimeters of a deep vein junction warrants the same clinical urgency as DVT.
| Feature | DVT of Dorsal Veins | Superficial Thrombophlebitis on Top of Foot |
|---|---|---|
| Vein depth | Deep venous system | Superficial venous system |
| Visible cord or vein | Sometimes | Often visible and palpable |
| Skin redness | Present, diffuse | Present, follows vein path |
| Swelling | Present, may extend to ankle | Localized to vein area |
| PE risk | Moderate to high | Low unless near deep vein junction |
| Urgency | Same-day medical evaluation | Prompt evaluation, especially if near deep junction |
Women on estrogen-containing oral contraceptives face a higher risk of both superficial and deep venous thrombosis in the foot, a consequence of estrogen’s upregulation of procoagulant clotting factors including Factor VII, Factor X, and fibrinogen.
Blood Clot in Foot Swelling and Skin Color Changes
Swelling and skin color changes are two of the most reliable physical indicators of a blood clot in the foot, and understanding why they occur helps explain why they should not be dismissed as simple injury or inflammation.
Swelling (edema) occurs because a blocked vein raises hydrostatic pressure inside the capillary beds downstream from the obstruction. That elevated pressure drives fluid through the capillary walls into the interstitial space faster than the lymphatic system can reabsorb it. The result is visible, often asymmetric swelling that is typically worse in the affected foot than the unaffected one. Pressing a finger into the swollen area for a few seconds and then releasing it may leave a temporary indentation (pitting edema), though non-pitting patterns occur as well.
Skin color changes in foot DVT follow a spectrum tied to how severely venous outflow is obstructed:
- Pink or red skin in the early phase reflects local inflammatory vasodilation driven by prostaglandins and histamine released from activated mast cells and endothelium
- Cyanotic or bluish-purple discoloration occurs when venous obstruction is severe enough to trap deoxygenated hemoglobin in the capillary network
- Pale or mottled skin can occur when both venous outflow and arterial inflow are compromised, a condition called phlegmasia cerulea dolens, which is a vascular emergency
According to the National Heart, Lung, and Blood Institute, persistent or worsening skin discoloration in an extremity, especially when accompanied by pain and swelling, is a clinical sign that warrants prompt evaluation rather than watchful waiting.
People with darker skin tones may find that the redness of DVT is less visually obvious. In this population, changes in skin texture (warmth, firmness, or tightness), asymmetric swelling, and pain localization are more reliable indicators than skin color alone.
Key Takeaway: Blood clot in foot symptoms, including localized pain, swelling, skin warmth, and color changes, reflect a blocked deep vein raising pressure in surrounding tissue and activating an inflammatory response. In darker skin tones, warmth and asymmetric swelling are more reliable indicators than redness alone.
Blood Clot in Foot Causes and Virchow’s Triad
A blood clot forms in the foot when three physiological conditions described by Virchow’s triad converge: venous stasis, endothelial injury, and hypercoagulability.
Venous stasis refers to slowed or pooled blood flow within the venous system. The deep veins of the foot and calf depend heavily on the pumping action of calf muscle contraction to return blood upward against gravity. When a person remains seated or immobile for extended periods (during a long flight, hospitalization, or bed rest), calf muscle contractions cease and venous blood stagnates in the foot and calf. This stagnation allows coagulation factors to accumulate and interact near the venous endothelium.
Endothelial injury refers to damage to the tunica intima, the innermost lining of a blood vessel. Surgical trauma, physical injury, inflammation from infection or autoimmune disease, or chemical damage from intravenous medications can disrupt the smooth endothelial surface that normally presents an anticoagulant face to circulating blood. Exposed subendothelial collagen activates the extrinsic coagulation pathway via tissue factor, triggering the conversion of prothrombin to thrombin, which then polymerizes fibrinogen into the fibrin mesh of a thrombus.
Hypercoagulability refers to any condition that shifts the balance of the coagulation system toward clot formation. This includes both inherited conditions (such as Factor V Leiden mutation, present in roughly 5 percent of people of European ancestry, and prothrombin gene mutation G20210A) and acquired states (pregnancy, malignancy, antiphospholipid antibody syndrome, oral contraceptive use).
Named causes of blood clot in the foot by mechanism:
- Prolonged immobility: reduced calf muscle pump, venous stasis in plantar arch and tibial veins
- Recent surgery (especially orthopedic procedures on the lower extremity or major abdominal surgery): combined endothelial injury and postoperative inflammatory hypercoagulability
- Active malignancy: tumor cells express tissue factor and shed procoagulant microparticles into the bloodstream
- Oral contraceptives containing ethinyl estradiol: estrogen upregulates hepatic production of Factors VII, X, and fibrinogen while downregulating Protein S
- Inherited thrombophilia (Factor V Leiden, prothrombin mutation, Protein C or Protein S deficiency): impaired natural anticoagulant mechanisms
- Dehydration: reduces plasma volume and increases blood viscosity, exacerbating venous stasis
- Trauma or fracture of the foot: direct endothelial injury
Blood Clot in Foot Risk Factors
Specific, named risk factors raise the probability that foot pain and swelling reflect a blood clot rather than a musculoskeletal or inflammatory cause.
The Wells DVT Score, a validated clinical probability tool used by emergency medicine and primary care physicians, assigns points to named risk factors including active cancer, recent paralysis or immobility, recent major surgery or hospitalization, localized vein tenderness, swollen leg, pitting edema, dilated collateral superficial veins, and previous DVT. A higher Wells score increases the pre-test probability that symptoms reflect a true DVT, which in turn determines the diagnostic pathway.
Key risk factors for blood clot in the foot:
- Recent major surgery, especially hip replacement, knee replacement, or abdominal surgery within the past 3 months
- Active cancer, particularly pancreatic, brain, lung, ovarian, or hematologic malignancy
- Inherited thrombophilia: Factor V Leiden mutation, prothrombin G20210A, Protein C deficiency, Protein S deficiency, antithrombin III deficiency
- Pregnancy or the first 12 weeks postpartum (a period of maximal hypercoagulability)
- Use of combined estrogen-progestin oral contraceptives
- Prolonged immobility from long-haul travel (flights over 4 hours), paralysis, or bed rest
- Prior history of DVT or pulmonary embolism
- Obesity (BMI greater than 30)
- Older age (risk increases progressively after age 40)
- Antiphospholipid antibody syndrome
- Inflammatory conditions including inflammatory bowel disease, lupus, and rheumatoid arthritis
- Central venous catheter placement in a limb
Men and women share most of these risk factors, but women face an additional category of hormonally driven risk tied to reproductive status that is discussed in a dedicated section below.
Blood Clot in Foot vs. Plantar Fasciitis and Other Conditions
Distinguishing a blood clot in the foot from plantar fasciitis and other common foot conditions matters clinically because the management approaches and urgency levels are completely different.
Plantar fasciitis involves microtears and chronic inflammation of the plantar fascia, the thick band of connective tissue that runs from the calcaneus (heel bone) to the base of the toes. Its defining feature is pain that is worst at the heel with the first few steps in the morning and improves within a few minutes of walking. A foot DVT does not typically produce heel-specific pain that resolves with activity. DVT pain is constant, located in the deeper tissues of the arch or ankle, and often worsens with weight-bearing.
Gout in the foot, which most commonly involves the first metatarsophalangeal joint (the base of the big toe), produces sudden, severe, exquisitely point-tender joint pain with overlying skin that is shiny, warm, and red. The pain intensity in gout often peaks within 24 hours of onset and is frequently nocturnal. While DVT can produce warmth and redness, it does not concentrate in a single small joint and does not produce the characteristic monoarticular joint inflammation of gout. A serum uric acid test and joint aspiration can distinguish them definitively.
Cellulitis is a bacterial skin infection that produces spreading redness, warmth, and swelling. It can closely mimic DVT. Cellulitis typically presents with a poorly defined spreading red border, skin that is warm and tight, and sometimes fever and systemic signs of infection. DVT does not produce fever in most cases unless deep vein infection (septic thrombophlebitis) is present.
| Condition | Pain Quality | Location | Swelling Pattern | Key Differentiator |
|---|---|---|---|---|
| Foot DVT | Deep, constant aching | Arch, ankle, or dorsum along vein | Asymmetric, may pit | Follows venous anatomy, skin color change |
| Plantar fasciitis | Sharp, heel-focused | Heel/sole | Minimal | Worst first steps of morning, improves with walking |
| Gout | Sudden, severe, joint-specific | MTP joint (big toe most common) | Localized, shiny skin | Elevated uric acid, nocturnal onset |
| Cellulitis | Burning, spreading | Skin surface | Spreading redness | Fever, defined red border, systemic signs |
| Peripheral edema | Pressure, heaviness | Bilateral, ankles | Bilateral, symmetrical | Both feet affected equally |
Key Takeaway: A blood clot in the foot produces constant deep aching along a venous distribution with asymmetric swelling and skin changes. Plantar fasciitis hurts at the heel on first steps. Gout attacks a single small joint suddenly. None of these can be definitively separated from DVT without clinical examination and imaging.
Isolated Distal DVT vs. Proximal DVT Symptoms
Isolated distal DVT, confined to the pedal or calf veins, produces milder symptoms than proximal DVT extending to the popliteal or femoral vein, but this should not be interpreted as meaning it is without clinical consequence.
Isolated distal DVT (sometimes called isolated calf DVT or pedal DVT) involves thrombosis within veins below the popliteal vein, including the posterior tibial vein, fibular vein, muscular calf veins, and the veins of the foot itself. The American Society of Hematology’s 2023 clinical guidelines state that isolated distal DVT carries a lower immediate risk of pulmonary embolism than proximal DVT, but it can extend proximally in 15 to 25 percent of cases within 3 months if untreated, particularly in the presence of active thrombophilia or malignancy.
Symptom comparison:
| Feature | Isolated Distal DVT (Foot/Calf) | Proximal DVT (Popliteal/Femoral) |
|---|---|---|
| Pain location | Foot, arch, inner ankle | Entire lower leg, behind knee, thigh |
| Swelling extent | Foot and ankle | Entire lower leg, sometimes thigh |
| Skin color change | Focal | May extend up the leg |
| Systemic symptoms | Usually absent | Low-grade fever possible |
| PE risk (untreated) | Approximately 1 to 5% | Approximately 10 to 30% |
| Diagnostic urgency | Same-day evaluation | Same-day or emergency evaluation |
Proximal DVT typically produces swelling that extends above the ankle into the calf or even the thigh, significant pain behind the knee (popliteal fossa), and a firmer, more obviously swollen limb. The foot may have milder symptoms in proximal DVT because the clot burden is upstream rather than in the foot itself.
Older adults with impaired calf muscle pump function (reduced mobility, muscle atrophy) and patients in the first weeks after lower extremity surgery face the highest risk that an isolated distal DVT will extend proximally without prompt evaluation.
Blood Clot in Foot During Pregnancy and Hormonal Risk
Pregnancy is one of the strongest acquired risk factors for deep vein thrombosis in the foot and lower extremity, driven by three distinct physiological changes that each satisfy a component of Virchow’s triad.
The procoagulant shift of pregnancy begins in the first trimester. Estrogen produced by the placenta upregulates hepatic synthesis of procoagulant clotting factors including fibrinogen, Factor VII, Factor VIII, Factor X, and von Willebrand factor, while simultaneously downregulating the natural anticoagulants Protein S and antithrombin. This biochemical shift reaches its peak in the third trimester. Research published in Obstetrics and Gynecology has documented a 4 to 5-fold higher DVT risk in pregnant women compared to age-matched non-pregnant women.
The growing uterus contributes a mechanical component: as it expands through the second and third trimesters, it compresses the inferior vena cava and the left iliac vein, reducing venous return from both lower extremities and creating the venous stasis component of Virchow’s triad. The left leg is more frequently affected by pregnancy-related DVT than the right for this anatomical reason.
The third contributor is reduced mobility, particularly in late pregnancy when physical activity declines. Reduced calf muscle pumping exacerbates venous pooling in the foot and calf.
The postpartum period, particularly the first 6 weeks after delivery, carries the highest absolute DVT risk in the reproductive period. Vascular injury from delivery, along with a persistence of pregnancy-induced hypercoagulability, creates conditions for thrombosis even after the mechanical compression is relieved.
Pregnant or recently postpartum women who notice unilateral foot or ankle swelling, localized warmth, or pain that differs from typical pregnancy-related bilateral lower extremity swelling should seek evaluation by their obstetrician or a primary care physician the same day. The evaluation approach differs slightly from non-pregnant adults because D-dimer levels are physiologically elevated in pregnancy, making that test less useful for ruling out DVT in this group.
Blood Clot in Foot in Older Adults and After Surgery
Older adults and people who have recently undergone surgery face a substantially elevated risk of pedal DVT, and the symptom presentation in both groups can be less obvious than in younger, otherwise healthy individuals.
In older adults, several physiological changes converge to raise DVT risk. Venous valve function declines with age, impairing the one-way flow that normally prevents blood from pooling in the lower extremities. Calf muscle mass decreases with age-related sarcopenia, reducing the muscle-pump action that propels venous blood upward. Reduced mobility from chronic musculoskeletal conditions, heart failure, or neurological disease further limits this pump. According to the National Heart, Lung, and Blood Institute, the incidence of DVT increases markedly in adults over 60 years of age, with the highest rates observed in adults over 80.
Pain perception in older adults can also be diminished by neuropathy, chronic pain conditions, or cognitive impairment, meaning that swelling and skin color change may be the presenting signs rather than pain. Caregivers and family members of older adults who are largely immobile should watch for asymmetric foot or ankle swelling as a potential DVT indicator.
Postoperative DVT risk peaks in the first 2 to 4 weeks after major surgery. Orthopedic procedures including total hip replacement and total knee replacement carry the highest procedural DVT risk. The mechanism is threefold: surgical trauma to vessel walls (endothelial injury), perioperative immobility (venous stasis), and the inflammatory procoagulant state triggered by surgical tissue damage (hypercoagulability). Most hospitals initiate DVT prophylaxis protocols (low molecular weight heparin, compression devices, or early ambulation) for this reason.
Patients who have recently had foot or ankle surgery and notice new or worsening pain, swelling, or warmth beyond what is expected for normal surgical healing should contact their orthopedic surgeon or a primary care physician the same day rather than attributing the changes to postoperative inflammation.
Key Takeaway: Older adults and recent surgical patients may present with swelling and skin changes as the primary DVT indicators rather than pain. Any asymmetric foot swelling in an immobile or recently operated patient warrants same-day medical evaluation.
Blood Clot in Foot Diagnosis and the Wells Score
The diagnosis of a blood clot in the foot begins with a structured clinical assessment, not with imaging alone. The Wells DVT Score is the internationally validated clinical probability tool that helps clinicians determine the likelihood of DVT before ordering a confirmatory test.
The Wells DVT Score assigns numerical values to specific clinical findings:
| Clinical Feature | Points |
|---|---|
| Active cancer (treatment within 6 months or palliative) | +1 |
| Paralysis, paresis, or recent plaster cast of lower extremity | +1 |
| Recently bedridden more than 3 days or major surgery within 12 weeks | +1 |
| Localized tenderness along deep venous system | +1 |
| Entire leg swollen | +1 |
| Calf swelling more than 3 cm vs. other leg | +1 |
| Pitting edema confined to symptomatic leg | +1 |
| Collateral superficial veins (non-varicose) | +1 |
| Previous DVT | +1 |
| Alternative diagnosis as likely or more likely than DVT | -2 |
A score of 2 or higher indicates moderate to high probability of DVT. A score below 2 indicates low probability. The Wells Score determines whether the next step is a D-dimer blood test, direct ultrasound imaging, or both.
Clinicians perform a physical examination that includes palpating the calf and foot for tenderness along venous paths, measuring the circumference of both calves and ankles to quantify asymmetric swelling, assessing skin color and temperature by comparison with the unaffected limb, and checking for the Homans’ sign (calf pain with passive dorsiflexion of the foot). However, the American College of Chest Physicians has noted that Homans’ sign is not reliable enough to confirm or exclude DVT on its own and should not be used as a standalone diagnostic criterion.
People with a prior history of DVT, known thrombophilia, or current anticoagulant use should disclose this information at the start of the evaluation. These factors directly affect both the pre-test probability calculation and the choice of diagnostic approach.
D-Dimer Test and Doppler Ultrasound for Foot DVT
The two primary diagnostic tools for confirming or excluding a blood clot in the foot are the D-dimer blood test and compression duplex Doppler ultrasonography.
D-dimer is a fibrin degradation product released when the fibrinolytic system breaks down a clot. An elevated D-dimer level indicates active thrombosis somewhere in the body. However, D-dimer is not specific to DVT: it rises in pregnancy, cancer, post-surgery, infection, and numerous other conditions. Its primary clinical value is in a negative result. According to a 2020 meta-analysis referenced in the Annals of Internal Medicine, a normal D-dimer level in a patient with a low Wells Score effectively rules out DVT without the need for ultrasound imaging, with a false-negative rate of less than 1 percent. D-dimer is a screening test, not a confirmatory one.
Compression duplex Doppler ultrasonography is the standard confirmatory test for lower extremity DVT. The ultrasound probe is used to compress the vein at multiple points along its course. A normal vein compresses easily under pressure. A vein containing a thrombus does not compress. The Doppler component assesses blood flow velocity and direction, and a clot-occluded vein shows absent or abnormal flow. This test is safe, radiation-free, and can be performed in a radiology department, hospital, or outpatient vascular lab.
Isolated pedal vein thrombosis can be harder to visualize on standard ultrasound protocols because many DVT imaging protocols focus on the femoral and popliteal veins rather than the foot itself. If pedal DVT is suspected clinically, the clinician should specifically request a complete lower extremity DVT study that includes assessment of the posterior tibial, fibular, and pedal veins.
Patients on anticoagulants who develop new symptoms should not assume that their existing medication prevents clot formation. Breakthrough thrombosis on anticoagulation does occur and warrants urgent re-evaluation by the prescribing physician or an emergency medicine physician the same day.
Post-Thrombotic Syndrome and Chronic Symptoms in the Foot
Post-thrombotic syndrome is a long-term complication of deep vein thrombosis in which permanent damage to venous valves and vein walls from the initial clot produces chronic, ongoing symptoms in the affected foot and leg.
When a thrombus forms in a deep vein, the inflammatory process that contributes to clot resolution also scars the venous valve leaflets, preventing them from closing fully. Incompetent venous valves allow blood to flow backward (reflux) under gravity whenever the patient stands, creating persistent venous hypertension in the foot and lower leg. This elevated chronic venous pressure drives the same edema, skin discoloration, and heaviness that characterized the acute DVT, but now as a permanent or recurrent condition rather than an acute event.
According to research published in the New England Journal of Medicine, post-thrombotic syndrome develops in approximately 20 to 50 percent of patients who have had a proximal DVT, with symptoms persisting for years after the initial event. Pedal and distal DVT carry a lower absolute risk of severe post-thrombotic syndrome but can still produce meaningful chronic symptoms.
Signs of post-thrombotic syndrome in the foot:
- Persistent daily foot and ankle swelling that worsens throughout the day and improves overnight
- A sensation of heaviness or fatigue in the foot and leg that begins shortly after standing
- Skin changes over the inner ankle: brown or reddish-brown pigmentation from chronic hemosiderin deposition (a process where red blood cell breakdown products stain the skin)
- Lipodermatosclerosis: hardening and fibrous thickening of the skin and subcutaneous tissue above the inner ankle
- Varicose veins or prominent collateral veins that develop as the venous system reroutes blood around the damaged area
- In severe cases, venous ulceration near the medial malleolus (inner ankle)
People with a previous DVT who notice returning or worsening foot swelling and skin changes should be evaluated by a vascular medicine specialist, since these symptoms may indicate post-thrombotic syndrome, recurrent DVT, or both.
Key Takeaway: Post-thrombotic syndrome produces chronic foot swelling, heaviness, and skin pigmentation changes months to years after a DVT due to permanent venous valve damage. Brown skin discoloration near the inner ankle in someone with a DVT history is a specific clinical sign of this condition.
Pulmonary Embolism Symptoms from a Foot Blood Clot
A blood clot that begins in the foot can travel through the venous system to the lungs, becoming a pulmonary embolism (PE), which is a life-threatening emergency requiring immediate evaluation.
The pathway from foot to lung follows the venous anatomy upward: from the pedal veins through the posterior tibial and fibular veins, into the popliteal vein, then the femoral vein, the iliac vein, the inferior vena cava, the right side of the heart, and finally into the pulmonary arterial tree. When a fragment of thrombus breaks free (embolizes) and lodges in the pulmonary artery or one of its branches, it obstructs blood flow to a portion of the lung. The affected lung tissue cannot participate in gas exchange, producing hypoxemia (low blood oxygen) and, in severe cases, right heart strain.
The National Heart, Lung, and Blood Institute states that PE causes approximately 60,000 to 100,000 deaths per year in the United States, making it one of the most lethal cardiovascular emergencies. The risk of embolization is highest in the first weeks after clot formation, before it has become fully organized and adherent to the vessel wall.
Pulmonary embolism symptoms to recognize:
- Sudden onset of shortness of breath that occurs at rest or with minimal exertion
- Sharp chest pain that worsens with deep breathing (pleuritic chest pain), caused by lung infarction or pleural irritation
- Coughing up blood-streaked sputum (hemoptysis), indicating pulmonary infarction
- Rapid heart rate (tachycardia) without an obvious cause
- Lightheadedness, dizziness, or a feeling of impending fainting
- Sudden anxiety or sense of doom, which reflects the body’s sympathetic nervous system response to hypoxemia and hemodynamic stress
- Loss of consciousness in severe cases (massive PE)
Pleuritic chest pain and shortness of breath occurring simultaneously in a person with a known or suspected foot DVT represent a PE until proven otherwise. This is not a situation for a telehealth visit or a call to a nurse hotline.
Emergency Symptoms: When to Call 911 or Go to the ER
Certain symptoms associated with a blood clot in the foot require immediate emergency evaluation. Do not wait to see if these resolve on their own.
Call 911 or go to the nearest emergency room immediately if you experience:
- Sudden shortness of breath that is new, rapid in onset, and not explained by exertion or a known respiratory condition
- Sharp chest pain that worsens when you breathe deeply or cough
- Coughing up blood or blood-tinged sputum
- A rapid or irregular heartbeat that is new and accompanied by lightheadedness or chest pressure
- Fainting, near-fainting, or sudden severe dizziness in the context of known or suspected foot DVT
- A foot or leg that becomes completely pale, cold, and insensible to touch (this may indicate arterial compromise in addition to venous occlusion, a condition requiring emergency vascular surgery evaluation)
- Bluish-purple skin discoloration of the entire leg that is spreading rapidly upward (possible phlegmasia cerulea dolens)
These presentations can indicate massive or submassive pulmonary embolism, severe proximal DVT with hemodynamic compromise, or vascular emergency, and they require emergency medical assessment. An urgent care clinic is not equipped to manage any of these presentations.
Frequently Asked Questions About Blood Clot in Foot Symptoms
What does a blood clot in the foot feel like compared to regular foot pain?
A blood clot in the foot produces a deep, constant aching or throbbing sensation that does not resolve with rest and is accompanied by swelling, skin warmth, or discoloration.
Regular foot pain from overuse, plantar fasciitis, or minor injury typically improves with rest, ice, and elevation within 24 to 48 hours and is not accompanied by asymmetric swelling or skin color change.
If your foot pain is persistent, worsening, and accompanied by any visible physical changes, seek evaluation by a primary care physician or emergency medicine physician the same day.
Can you have a blood clot in your foot without any swelling?
Yes, a blood clot in the foot can occur without obvious swelling, particularly in the early stages of thrombosis before venous pressure has risen enough to push significant fluid into the interstitial space.
Approximately 25 to 30 percent of confirmed distal DVT cases present with minimal or non-specific symptoms, according to data published in Thrombosis and Haemostasis.
If you have known risk factors for DVT and are experiencing persistent, unexplained foot pain or warmth without visible swelling, still seek clinical evaluation rather than waiting for swelling to appear.
What does a blood clot on top of the foot look like?
A blood clot on top of the foot typically produces visible redness or pink discoloration, local swelling, and sometimes a firm, tender cord-like vein that is visible just beneath the skin surface.
The redness follows the path of the affected vein rather than spreading diffusely like cellulitis, and the skin feels warm to the touch compared with the same area on the unaffected foot.
People with darker skin tones may not see obvious redness; instead, the vein may feel firmer or warmer than normal, with visible swelling over the dorsum (upper surface) of the foot.
How quickly can a blood clot in the foot turn into a pulmonary embolism?
Pulmonary embolism from a lower extremity DVT can occur within hours to days of clot formation, most commonly in the first 1 to 2 weeks when the thrombus is freshly formed and most vulnerable to fragmentation.
The risk is higher with proximal DVT (popliteal vein and above) than with isolated pedal or calf DVT, though distal clots that extend proximally carry the same elevated PE risk as primary proximal DVT.
Any sudden onset of shortness of breath or chest pain in a person with suspected or confirmed foot DVT requires immediate 911 activation, not a wait-and-see approach.
How is a blood clot in the foot diagnosed?
A foot DVT is diagnosed through a combination of clinical probability assessment using the Wells DVT Score, a D-dimer blood test, and confirmatory compression duplex Doppler ultrasonography.
A normal D-dimer result in a low-probability patient effectively excludes DVT without ultrasound, while an elevated D-dimer or a higher Wells Score leads directly to ultrasound imaging.
Specific evaluation of pedal veins (the dorsal and plantar veins of the foot) requires a complete lower extremity DVT protocol; standard ultrasound studies that focus only on the femoral and popliteal veins can miss isolated pedal thrombosis.
Can a blood clot in the foot go away on its own?
Small, isolated distal DVTs confined to the foot veins do sometimes resolve spontaneously through the body’s natural fibrinolytic system, but this process is unpredictable and cannot be relied upon for clinical management.
According to the 2023 American Society of Hematology guidelines, even isolated distal DVT in a symptomatic patient warrants anticoagulation therapy or close serial ultrasound monitoring to detect proximal extension, depending on individual risk factors.
No one with symptoms of foot DVT should attempt to manage the condition at home without a confirmed clinical assessment; the risk of proximal extension and pulmonary embolism makes professional evaluation mandatory.
Blood clot in foot symptoms rarely arrive with a blinking warning light. The ache in the arch, the warmth along a vein, the swelling that seems heavier than expected for a minor injury: these are the signals the venous system sends when something has gone wrong inside it. Knowing what those signals mean gives you the information to act rather than wait.
If you have experienced persistent, unexplained foot pain with swelling or skin changes, contact a primary care physician or go directly to an emergency department for same-day evaluation. Bring a note of when symptoms began, whether both feet are affected or only one, any recent surgeries or travel, and any medications you are taking including oral contraceptives or blood thinners.
A DVT caught early, before proximal extension or embolism, is a manageable condition. A missed one is not.